New Study Reopens Cefepime Mortality Safety Question
post on 19 Sept 2026

post on 19 Sept 2026
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/news/cefepime-mortality-bayesian-meta-analysis
New Study Reopens Cefepime Mortality Safety Question
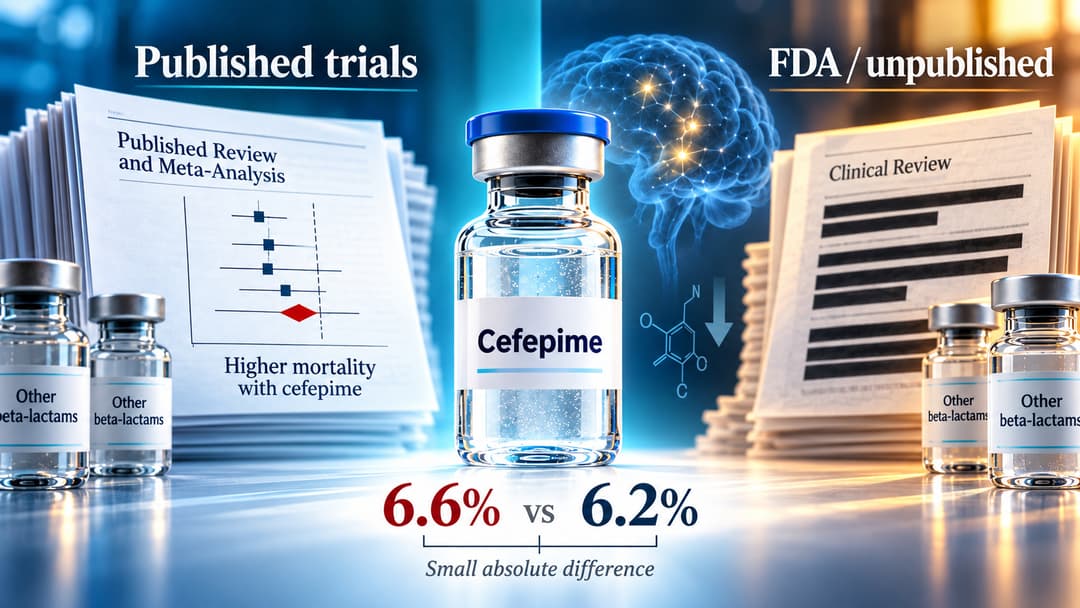
A Bayesian meta-analysis of 110 randomized trials found a high probability of higher mortality with cefepime than other beta-lactams—but the absolute difference was small and unpublished studies pointed in the opposite direction.
A large new analysis has reopened a safety question that has followed the broad-spectrum antibiotic cefepime for nearly two decades.
Researchers analyzing 110 randomized clinical trials involving 22,608 patients found that patients assigned to cefepime had slightly more deaths than those receiving other beta-lactam antibiotics. Their Bayesian model estimated a 94.4% posterior probability that the pooled odds ratio for mortality was greater than 1. [1]
That number requires careful interpretation.
It does not mean cefepime increased mortality by 94.4%.
Across all included trials, the estimated odds ratio was 1.10, with a 95% credible interval of 0.98 to 1.24. Death occurred in 778 of 11,726 patients receiving cefepime and 674 of 10,882 patients receiving comparator beta-lactams. [1]
In absolute terms, mortality was 6.6% versus 6.2%.
The study therefore raises a clinically important safety signal—but it does not establish that cefepime itself directly caused the excess deaths.
The systematic review and Bayesian meta-analysis, published September 10 in JAMA Network Open, pooled randomized trials comparing cefepime with other beta-lactam antibiotics across multiple clinical indications. [1]
The primary analysis included:
110 randomized trials
22,608 patients
11,726 assigned to cefepime
10,882 assigned to comparator beta-lactams
The overall result was:
OR 1.10; 95% credible interval 0.98–1.24; 94.4% posterior probability that OR >1. [1]
The Bayesian probability describes how strongly the model favored an odds ratio above 1 given the included data and statistical assumptions.
It should not be read as a 94.4% increase in risk or as proof that cefepime causes mortality.
When researchers restricted the analysis to 73 peer-reviewed published randomized trials involving 15,411 patients, the association became stronger.
The pooled mortality odds ratio was:
OR 1.17; 95% credible interval 1.02–1.34
with a 98.6% posterior probability that mortality odds were higher with cefepime. [1]
This difference between the full dataset and the published literature became one of the most important uncertainties in the study.
The full evidence base also included 12 other abstract or unpublished reports and 25 trials provided through the FDA.
Those unpublished data shifted the pooled estimate toward less apparent harm.
The investigators found a greater than 98% probability that the unpublished studies came from a different distribution than the published literature. At the same time, formal funnel-plot and Egger-style analyses did not demonstrate statistically significant publication bias. [1]
The authors therefore could not determine whether the discrepancy reflects selective publication or genuine differences in patient populations, illness severity, cefepime dosing, comparator antibiotics, concomitant treatment or other trial characteristics.
The Bayesian probabilities sound large, but the absolute difference between groups was much smaller.
Across all 110 trials:
Outcome | Cefepime | Other beta-lactams |
|---|---|---|
Deaths | 778 / 11,726 | 674 / 10,882 |
Mortality | 6.6% | 6.2% |
Using crude event rates, the researchers estimated an absolute risk difference of approximately 0.4 percentage points and an approximate number needed to harm of 227. [1]
Among the published peer-reviewed trials alone, the absolute difference was approximately 0.9 percentage points, corresponding to an estimated NNH of 111.
These NNH calculations were based on crude pooled event rates. They should not be interpreted as a precise individualized risk estimate for a particular patient or clinical indication.
The association differed by age.
Among 57 adult trials, the pooled mortality odds ratio was 1.18 with a 95% credible interval of 1.03 to 1.35 and a 98.9% posterior probability of higher mortality with cefepime. [1]
Among 16 pediatric trials, the pooled odds ratio was 1.00, with a 95% credible interval of 0.66 to 1.54 and a posterior probability of harm of approximately 50.9%.
The pediatric analysis therefore showed little evidence of a mortality difference, although the lower overall death rate and wide credible interval limit how strongly that subgroup can be interpreted.
The published trials also suggested that the mortality signal varied by clinical indication.
For febrile neutropenia, the pooled OR was 1.19, with a 96.1% posterior probability that mortality odds were higher with cefepime.
For severe bacterial infections, the pooled OR was also 1.19, with a 92.2% posterior probability of higher mortality. [1]
The strongest comparator-specific result involved ceftazidime.
Across 33 trials comparing the two antibiotics, cefepime had an OR for mortality of 1.30 with a 95% credible interval of 1.06 to 1.62, corresponding to a 99.3% posterior probability of higher mortality. [1]
These subgroup findings are useful for generating hypotheses, but they should not be treated as proof that cefepime produces the same relative effect across every patient population or infection.
The study does not establish a specific mechanism.
One possibility is cefepime-associated neurotoxicity.
Higher drug exposures have been associated with encephalopathy, altered mental status, myoclonus and seizures, particularly in older adults, critically ill patients and those with impaired kidney function. [1]
But even here, causality is difficult to untangle.
Kidney dysfunction can increase cefepime exposure while independently marking a patient as more severely ill. Neurotoxicity could therefore contribute directly to poor outcomes, act as a marker of excessive exposure, or coexist with other mortality risks.
A second possibility runs in the opposite direction: inadequate antibiotic exposure.
Some Gram-negative infections may require greater cefepime exposure when the bacterial minimum inhibitory concentration is higher. Increasing or extending dosing may improve antibacterial target attainment, but may simultaneously narrow the margin before concentration-related neurotoxicity becomes more likely.
The authors therefore describe a difficult pharmacologic balance between too little exposure for efficacy and too much exposure for toxicity. [1]
MedicalToxic discusses the broader role of dose, safety signals and postmarketing evidence in The Role of Medical Toxicology in Drug Safety.
An invited commentary accompanying the study argues that the findings should not be simplified into a conclusion that cefepime is inherently dangerous.
Uslan and Smith describe cefepime as an important antibiotic whose safety question may be closely tied to dosing and pharmacologic exposure rather than a simple drug-versus-no-drug effect. [2]
They emphasize the need for greater transparency around the FDA-provided unpublished trials and for prospective research focused on optimized dosing.
That interpretation remains a hypothesis—not a proven explanation for the mortality signal.
The contrast between study sources is difficult to ignore.
Published peer-reviewed trials produced a stronger mortality signal, while the unpublished and FDA-provided evidence shifted estimates in the opposite direction.
The authors rated the overall certainty of evidence as moderate, downgrading for heterogeneity and possible publication bias. [1]
Importantly, they did not conclude that publication bias had been proven.
Limited methodological information was available for the FDA-provided trials, making it difficult to determine whether their different results reflected bias, different patient populations or legitimate differences in study design.
That unresolved discrepancy is one reason the new analysis should be interpreted as a safety signal, not a definitive causal verdict.
The researchers explicitly say no.
Cefepime remains an important broad-spectrum beta-lactam antibiotic, including for serious Gram-negative infections, Pseudomonas aeruginosa, febrile neutropenia and infections involving organisms at risk for clinically important AmpC beta-lactamase production. [1]
The study does not demonstrate that patients currently receiving appropriate cefepime therapy should routinely be switched to another antibiotic.
Instead, the authors argue that the mortality signal should inform future guidance and prompt better prospective investigation of exposure, dosing and toxicity.
The accompanying commentary takes a similar position: cefepime remains useful, but clinicians need better evidence about how to achieve effective exposure without increasing toxicity. [2]
Concern about cefepime mortality is not new.
A 2007 meta-analysis previously raised a mortality signal, while a later FDA analysis incorporating unpublished industry data did not find a statistically significant increase.
The new study revisits that unresolved question using a much larger assembled evidence base and a Bayesian framework.
Its most important contribution is not simply the number 94.4%.
It is the simultaneous finding that:
the overall randomized evidence favors a mortality OR above 1;
the signal becomes stronger when restricted to peer-reviewed published trials;
adults show a clearer signal than children;
the absolute mortality difference remains relatively small; and
unpublished FDA-provided trials point in a different direction. [1]
That combination makes the result clinically important but still uncertain.
Several limitations prevent a simple causal interpretation.
The analysis used aggregate trial-level rather than individual-patient data.
Many included trials were older and open label, and the clinical indications, cefepime doses and comparators varied substantially.
Detailed methodological information was unavailable for the 25 FDA-provided trials.
All-cause mortality is also an imperfect safety outcome because patients treated for severe infections or cancer may die from their underlying disease rather than from antibiotic toxicity. [1]
The researchers therefore describe the mortality result as a global safety signal, not evidence of one specific toxic mechanism.
A new systematic review and Bayesian meta-analysis has revived a long-running question about cefepime safety.
Across 110 randomized trials involving 22,608 patients, mortality was 6.6% with cefepime and 6.2% with other beta-lactams, with a 94.4% posterior probability that the pooled mortality odds ratio exceeded 1. [1]
The signal was stronger in published trials and adults, but the absolute difference was modest and unpublished studies pointed in the opposite direction.
The study therefore does not establish that cefepime itself directly causes excess mortality, nor does it support abandoning a widely used antibiotic.
It does strengthen the case for resolving an old uncertainty: whether cefepime's mortality signal reflects intrinsic toxicity, dosing and exposure, differences between trial populations—or some combination of these factors.
Sohani, Z. N., Zhong, Y. J., Afshar, A., et al. (2026). Cefepime and Mortality: A Systematic Review and Bayesian Meta-Analysis. JAMA Network Open, 9(9), e2633017. https://doi.org/10.1001/jamanetworkopen.2026.33017
Uslan, D. Z., & Smith, E. A. (2026). Cefepime and Mortality—A Dosing Problem, Not a Drug Problem. JAMA Network Open, 9(9), e2632904. https://doi.org/10.1001/jamanetworkopen.2026.32904
Keep reading
Latest Research and Studies
05 Aug 2026

Latest Research and Studies
27 Jul 2026

Latest Research and Studies
27 Jul 2026
Latest Research and Studies
06 Jul 2026
