Kratom and 7-Hydroxymitragynine Poisoning
Published on 09 Oct 2026 · Updated 11 Oct 2026

Published on 09 Oct 2026 · Updated 11 Oct 2026
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/guidelines/kratom-7-hydroxymitragynine-poisoning
Poison center and emergency management guideline
Updated: October 11, 2026
Scope
Acute poisoning, poison-center triage, emergency management, observation, disposition, delayed hepatotoxicity, dependence, and withdrawal involving botanical kratom, kratom extracts, 7-hydroxymitragynine (7-OH), mitragynine pseudoindoxyl (MP), MGM-15, MGM-16, and other modified or unidentified kratom-derived products.
Clinical Bottom Line
Botanical kratom and concentrated 7-OH products are not clinically interchangeable.
Conventional botanical kratom is predominantly mitragynine-containing. Concentrated 7-OH and related semisynthetic products can produce a more conventional opioid phenotype, including respiratory depression, coma, tolerance, dependence, withdrawal, and recurrent toxicity after naloxone.
No validated human toxic-dose threshold exists for kratom or 7-OH. Product labeling and claimed serving size should not substitute for assessment of product class, symptoms, opioid tolerance, co-exposures, intent, age, and time since exposure. [1–4]
Clinical warning
Kratom products are not clinically interchangeable. Concentrated 7-hydroxymitragynine (7-OH), concentrated kratom extracts, mitragynine pseudoindoxyl, MGM compounds, and unidentified or enhanced products may produce opioid-type respiratory depression, coma, recurrent toxicity, dependence, and withdrawal. Ventilation takes priority over naloxone; use naloxone for clinically significant opioid-type respiratory depression or apnea and titrate to adequate spontaneous ventilation. Any Step 1 criterion warrants immediate ED evaluation; Step 1 is the complete ED-referral list. No validated toxic-dose threshold, pediatric threshold, home-triage rule, or observation interval exists for 7-OH. Product labels may be used to identify a product and its declared contents, but not as toxicity thresholds or as proof of actual content.
Figure 1. Poison-center triage
Any Step 1 criterion sends the patient straight to the ED. Otherwise, the product class, then the patient's age, the size of the exposure, the product's identity, and tolerance decide home versus ED.
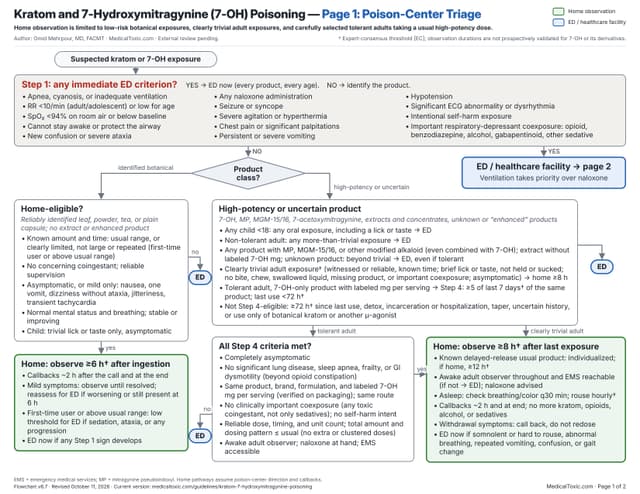
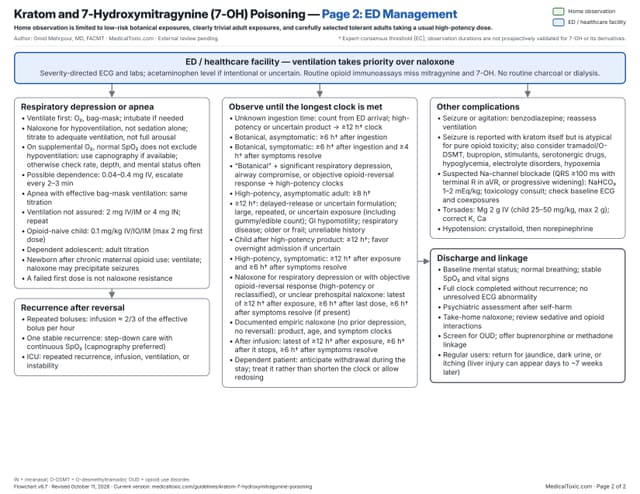
Figure 2. ED management
Every ED patient stays until the longest applicable observation clock has run.
Recommend ED evaluation now for any of the following:
Apnea, cyanosis, or visibly inadequate ventilation
Respiratory rate <10/min in an adolescent or adult, or otherwise abnormally low for age
Oxygen saturation <94% on room air in a patient without known chronic hypoxemia, or a clinically meaningful decrease below the patient's documented baseline
Inability to remain awake or protect the airway
New confusion or severe ataxia
Any naloxone administration
Seizure
Syncope
Severe agitation or hyperthermia
Chest pain
Significant palpitations
Persistent or severe vomiting
Hypotension
Significant ECG abnormality or dysrhythmia
Intentional self-harm exposure
Clinically important opioid, benzodiazepine, alcohol, gabapentinoid, sedative-hypnotic, or other respiratory-depressant coexposure
[EC]
If YES → ED. If NO → Step 2.
Includes:
7-OH
Mitragynine pseudoindoxyl
MGM-15
MGM-16
7-acetoxymitragynine
Concentrated kratom extracts
Other chemically modified kratom alkaloids
Any unidentified or "enhanced" kratom product
If product identity or concentration cannot be established, manage it as a high-potency/uncertain product. [EC]
Commercial 7-OH products vary widely in dose per serving; see Product Classification below.
→ Proceed to Step 3.
Product composition cannot be confirmed from telephone history. Classify an exposure as conventional botanical kratom only when all of the following are true:
Leaf, powder, tea, or conventional capsule
Packaging is available or the product is otherwise reliably identified
Not labeled or marketed as an extract, concentrate, liquid shot, resin, or "enhanced," "fortified," or "extra-strength" product
No 7-OH, 7-HMG, mitragynine pseudoindoxyl, MGM compound, or other modified alkaloid listed
If any criterion is not met → manage as high-potency/uncertain → Step 3. [EC]
→ Otherwise, proceed to Step 5.
After a product identified as conventional botanical kratom, manage the exposure as high-potency/uncertain and apply the high-potency observation clocks in Step 6 when any of the following occurs:
Clinically significant opioid-type respiratory depression (bradypnea, apnea, or hypoventilation-related hypoxemia)
Inability to protect the airway
CNS or respiratory depression with an objective opioid-reversal response to naloxone
[EC]
This is a disposition rule, not a determination of product identity. Adulteration and label-content discrepancies are documented in commercial kratom products. [2–4,34; P]
Empiric naloxone given without preceding respiratory depression and without an objective opioid-reversal response does not by itself trigger reclassification. When the indication for prehospital naloxone or the response cannot be reliably established, see Step 6, After Naloxone.
Child <18 years:
Any oral exposure to a high-potency or uncertain product identified in Step 2, including a lick or taste:
→ ED regardless of current symptoms. [EC]
In children <12 years, poison-center data show higher odds of serious respiratory and neurologic effects after 7-OH or MP than after mitragynine. [5; H2] Extension of this rule to adolescents 12–17 years is expert consensus. [EC]
An adult exposure is clearly trivial only when all of the following are true:
Witnessed or reliably reported brief lick or taste only, at a known time; product not held, sucked, or dissolved in the mouth
No bite, chew, or swallowed portion of a tablet, capsule, gummy, or edible
No swallowed liquid
No product unaccounted for
Completely asymptomatic
No clinically important coexposure
No self-harm intent
An adult meeting all criteria may be considered for individualized poison-center-directed home observation for ≥8 hours after exposure, using the Step 4 Home Monitoring requirements. [EC]
Emergency services must be readily accessible. Having naloxone available is advised but not required for this pathway. [EC]
If any criterion is not met or cannot be established, the exposure is not trivial. Apply the tolerance-based criteria below.
Adult without current high-potency opioid tolerance:
Any more-than-trivial ingestion of a high-potency or uncertain product identified in Step 2, including 7-OH, mitragynine pseudoindoxyl, MGM compounds, concentrated kratom extracts, or unidentified enhanced products:
→ ED even if currently asymptomatic. [EC]
Adult with current high-potency opioid tolerance:
Product explicitly identified as 7-OH, with a numerical 7-OH content declared per serving and no other modified kratom alkaloid listed → Step 4.
Any product containing mitragynine pseudoindoxyl, MGM-15, MGM-16, 7-acetoxymitragynine, or another chemically modified kratom alkaloid, alone or combined with 7-OH; an extract or concentrate labeled only by mitragynine or total alkaloid content; or a product with uncertain composition or labeling: any more-than-trivial exposure → ED, even when tolerant. [EC]
When a product meets both descriptions, the ED rule takes precedence. Explicit 7-OH labeling does not establish actual chemical composition, dose accuracy, or safety; measured content can differ from the label. [3,4,34; P] All Step 4 criteria remain mandatory.
Important: If product identity, amount ingested, or recent opioid tolerance cannot be reliably established, use the more conservative applicable pathway. [EC]
For this algorithm, an adult is currently tolerant only when all of the following are true:
Reliable history of use of the same high-potency product and formulation on approximately ≥5 of the preceding 7 days
Last use of that product <72 hours ago
None of the following loss-of-tolerance factors:
Recent detoxification
Incarceration or hospitalization interrupting use
Significant deliberate taper or dose reduction
Treatment that substantially reduced opioid exposure
Uncertain recent use history [EC]
Tolerance to another μ-opioid agonist, or regular botanical kratom use, does not qualify a patient for the Step 4 home pathway. [EC]
A person returning to a previously tolerated dose after ≥72 hours without that product does not qualify. [EC]
These criteria define eligibility for the Step 4 pathway only. They do not establish biological tolerance to respiratory depression, and meeting them does not make home observation safe. [EC]
Home observation may be considered only when all of the following are true:
Meets the Operational Definition of Current Opioid Tolerance
Product explicitly identified as 7-OH, with a numerical 7-OH content per serving stated on the packaging and no other modified kratom alkaloid listed
Completely asymptomatic
No significant underlying respiratory disease (including obstructive sleep apnea) or frailty, and no diagnosed gastroparesis or other clinically significant gastrointestinal dysmotility; ordinary opioid-induced constipation does not exclude
Same product and formulation as the tolerated product, verified from the packaging, with no change in brand, formulation, labeled concentration, or route of administration (for example, swallowed versus sublingual, or crushed or otherwise manipulated)
Total amount and dosing pattern during this exposure episode no more than the patient's established usual regimen; no additional or clustered doses
No clinically important coexposure
No self-harm intent
Reliable dose, time, and unit count (for gummies or edibles)
Responsible adult observer present
Naloxone immediately available
Emergency services readily accessible
[EC]
Same product does not guarantee same dose, because commercial products vary in measured content. [2–4,34; P] This pathway accepts that residual risk only because established tolerance, a responsible observer, and immediate naloxone availability are all present.
If any criterion is not met → ED.
Observe ≥8 hours after the last dose. [EC]
When the usual, previously tolerated product is a known delayed-release formulation, home observation is an individualized poison-center decision; if chosen, observe ≥12 hours after the last dose. Tolerance does not eliminate delayed absorption. [EC]
An uncertain formulation, a large or repeated exposure beyond the usual pattern, an uncertain amount or time, or a gummy or edible with an uncertain number of pieces or unknown concentration does not meet Step 4 → ED. [EC]
The responsible observer should remain awake and continuously available during the observation period.
The patient may sleep, but if sleeping:
assess respiratory effort and color at least every 30 minutes;
confirm that the patient can be readily awakened and responds normally at least hourly.
[EC]
If this degree of observation cannot be provided → ED.
No further kratom, 7-OH, opioids, alcohol, benzodiazepines, sleep medications, or other sedatives should be used during observation.
In a dependent patient, opioid withdrawal may emerge during the observation period. Advise a poison-center callback rather than redosing; manage withdrawal as in Dependence, Withdrawal, and MOUD Linkage.
Callback approximately 2 hours after the initial assessment
Final callback when the applicable 8- or 12-hour observation period is complete
Immediate callback or ED referral for somnolence, difficulty rousing, abnormal breathing, repeated vomiting, confusion, gait abnormality, or other progression
Home observation is reasonable when all of the following are true:
Reliable, isolated exposure without self-harm intent
The amount and time of ingestion are known
The amount is either within the person's usual range, or, for a first-time user or a regular user above their usual range, clearly limited, not large, and not repeated
No concerning coingestant
Reliable supervision is available
[EC]
An unusually large ingestion, an escalating binge, or an uncertain amount:
→ ED. [EC]
Recreational or therapeutic intentional use alone is not an ED criterion. Intentional self-harm is.
Observe for ≥6 hours after the last ingestion. [EC]
Home observation may remain appropriate, including for a first-time user, when symptoms are limited to:
Mild nausea
One isolated episode of vomiting
Mild dizziness without gait impairment
Mild jitteriness or anxiety
Mild transient tachycardia without chest pain, syncope, or significant palpitations
and all of the following remain true:
Normal mental status
Normal spontaneous breathing
No increasing somnolence
No ataxia
No repeated vomiting
No severe agitation
No concerning coingestant
No self-harm intent
Symptoms are stable or improving
Exposure is not unusually large or uncertain
Reliable observation is available
[EC]
For a first-time user or a regular user above their usual range, use a lower threshold for ED referral if sedation, gait abnormality, repeated vomiting, substantial tachycardia, or symptom progression develops.
Observe for ≥6 hours after the last ingestion and until mild symptoms have resolved. Worsening symptoms, or symptoms still present at the end of the observation period, warrant reassessment for ED referral. [EC]
Suggested callback:
Approximately 2 hours after the initial symptomatic assessment
At completion of the 6-hour period
Immediately if symptoms progress
A clearly trivial lick or taste of identified conventional botanical material in an asymptomatic child may be observed at home for ≥6 hours after exposure. [EC]
If more than a trivial amount was swallowed, the amount is uncertain, symptoms develop, or product concentration is uncertain:
→ ED
Observation duration should be determined by the longest applicable clock.
When the time of ingestion cannot be reliably established, start the applicable clock at the latest possible ingestion time: usually ED arrival, or the time the patient was found if continuously observed since. For a high-potency or uncertain product, an unknown ingestion time is an unreliable exposure history: apply the ≥12-hour clock from that reference time. Extend observation when the clinical course or a suspected delayed-release formulation warrants. [EC]
≥6 hours after the last ingestion. [EC]
For a botanical exposure with clinically meaningful symptoms evaluated in an ED or other healthcare facility, observe until the later of:
≥6 hours after the last ingestion; or
≥4 hours after complete resolution of clinically meaningful symptoms.
[EC]
Longer observation may be required when a coingestant or clinical complication dictates.
These botanical clocks do not apply after clinically significant opioid-type respiratory depression, inability to protect the airway, or CNS or respiratory depression with an objective opioid-reversal response to naloxone. Manage as high-potency/uncertain (Step 2, Clinical Reclassification) and apply the high-potency clocks below. [EC]
≥8 hours after the last ingestion. [EC]
Use ≥12 hours for delayed-release or uncertain formulation, large, repeated, or otherwise uncertain exposure, or other factors likely to delay absorption.
A gummy or edible with an uncertain number of pieces or unknown concentration should be treated as an uncertain exposure. [EC]
Also use ≥12 hours when any of the following is present:
Gastrointestinal hypomotility
Significant underlying respiratory disease
Older or frail patient
Unreliable product composition
Unreliable exposure history
[EC]
≥12 hours after the last ingestion. [EC]
Favor overnight monitored admission when:
Amount or timing is uncertain
A whole tablet, gummy, or potentially substantial amount was swallowed
Any clinically meaningful symptom occurred
Important coexposure is present
Safe post-discharge observation cannot be ensured
For high-potency exposure with CNS depression, ataxia, respiratory abnormality, repeated vomiting, clinically important cardiovascular effects, or other significant toxicity, even when naloxone was not required, observe until the later of:
≥12 hours after the last exposure; or
≥6 hours after complete resolution of clinically meaningful symptoms.
[EC]
Longer observation may be required when the coingestant or clinical complication dictates.
Naloxone never shortens observation.
Naloxone given for opioid-type respiratory depression, or followed by an objective opioid-reversal response, after a high-potency/uncertain exposure or a botanical exposure managed as high-potency under Step 2: observe until the latest of:
≥12 hours after the last exposure
≥6 hours after the last naloxone dose
≥6 hours after complete resolution of clinically meaningful symptoms, when such symptoms occurred
[EC]
Empiric naloxone administered without preceding opioid-type respiratory depression and without an objective opioid-reversal response does not independently trigger reclassification or establish a naloxone-specific observation interval. Apply the applicable product-, age-, symptom-, and coexposure-based clocks. Any naloxone administration remains an ED-referral criterion under Step 1. [EC]
If the indication for prehospital naloxone or the clinical response cannot be reliably established, apply the high-potency/uncertain observation pathway, including the after-naloxone clock, as a conservative disposition rule. This does not establish naloxone responsiveness or confirm high-potency product identity. [EC]
Examples:
Adult, liquid 7-OH. One naloxone dose at hour 1; symptoms resolve by hour 3. Observe until at least hour 12.
Adult, 7-OH tablet. Recurrent hypoventilation at hour 9; repeat naloxone with immediate complete response. Observe until at least hour 15, in a monitored setting (see Recurrent Respiratory Depression).
Child, 7-OH gummy. Naloxone at hour 2; sedation resolves at hour 10. Observe until at least hour 16.
Prehospital naloxone, indication and response undocumented, asymptomatic on arrival. Naloxone at hour 1. Observe until at least hour 12; no symptom-resolution clock applies.
Product labeled as botanical powder, naloxone-responsive hypoventilation. Manage as high-potency/uncertain; apply the clocks above, not the 6-hour botanical clock.
Botanical powder, empiric prehospital naloxone without respiratory depression or response. Botanical clocks apply; no naloxone-specific clock.
Any clinically important recurrence requiring additional naloxone or assisted ventilation warrants monitored admission. [EC]
A single recurrence that responds promptly and remains stable may be managed in a step-down or equivalent monitored setting only when all of the following are available:
Continuous pulse oximetry
Preferably continuous capnography
Frequent bedside nursing assessment
Immediate naloxone availability
Immediate airway support
Use ICU-level care for:
Repeated respiratory recurrence
Naloxone infusion
Assisted ventilation
Escalating naloxone requirements
Persistent substantial sedation
Hemodynamic instability
Significant pulmonary complication
Lack of an appropriate high-acuity monitored unit
Observe until the latest of:
≥12 hours after the last exposure
≥6 hours after infusion discontinuation
≥6 hours after complete resolution of significant symptoms
[EC]
Dependent patients, including adolescents, may develop opioid withdrawal during prolonged observation. Anticipate and treat it rather than shortening the observation clock or allowing redosing. [EC]
This is a rapid evidence-informed poison-center guideline rather than a formal systematic review or GRADE guideline.
Targeted literature and regulatory review completed October 5, 2026; focused PubMed/MEDLINE and Federal Register updates were performed October 8 and October 11, 2026.
The targeted literature and regulatory review used PubMed/MEDLINE and authoritative primary sources including ACMT, CDC/MMWR, FDA, DEA, HHS, and the Federal Register.
Search concepts included kratom, Mitragyna speciosa, mitragynine, 7-hydroxymitragynine, 7-OH, 7-HMG, mitragynine pseudoindoxyl, MGM-15, MGM-16, poisoning, overdose, respiratory depression, naloxone, pharmacokinetics, cardiac, pulmonary, seizure, interaction, liver injury, pregnancy, neonatal withdrawal, psychosis, withdrawal, and buprenorphine.
[H1] Controlled/prospective human experimental evidence.
[H2] Observational human evidence. Prospective cohorts, poison-center studies, surveillance datasets, and pharmacokinetic derivation studies without controlled clinical outcome testing.
[H3] Human case-level evidence.
[H3-SR] Systematic review of case-level evidence. Systematic synthesis does not elevate the underlying case reports to controlled evidence.
[M] Mechanistic evidence. Animal, receptor, or in-vitro evidence.
[P] Product/market-analysis evidence. Analytical chemistry, label-content studies, stability testing, contaminant testing, or systematic product-market characterization.
[EC] Expert consensus/extrapolation.
Professional or regulatory authority is identified separately, for example [ACMT guidance], [FDA], or [DEA], rather than treated as an evidence grade.
No validated toxic-dose threshold, pediatric threshold, prospective poison-center triage rule, or validated observation interval currently exists for 7-OH.
Leaf, powder, tea, or conventional capsules without evidence of alkaloid concentration or enhancement.
Classify as A only when the Step 2 identification criteria are met.
Liquid shots, concentrated extracts, resins, or products advertising enhanced alkaloid content.
Extracts and concentrates are managed as high-potency/uncertain because measured alkaloid content frequently differs from labeling and cannot be established at the time of the call, not because 7-OH content has been demonstrated in a defined proportion of these products. [2–4; P] [EC]
Products labeled as "kratom extract" and declaring 7-OH content have been found to contain synthetic-level 7-OH (22–75 mg/g), 5–28% above label claims, with chromatographic profiles inconsistent with kratom leaf. The "extract" label does not establish botanical origin, and a declared 7-OH amount does not establish actual content. [34; P]
Extracts or concentrates labeled only by mitragynine or total alkaloid content do not qualify for the Step 4 home pathway, even in tolerant adults (Step 3). [EC]
Any formulation marketed as containing 7-hydroxymitragynine, 7-OH, or 7-HMG.
Includes products marketed as containing:
Mitragynine pseudoindoxyl
MGM-15
MGM-16
7-acetoxymitragynine
Other chemically modified kratom alkaloids
Human toxicity and relative potency cannot be assumed to be equivalent among these compounds.
Tolerance does not qualify users of these products for the Step 4 home pathway, including when they are combined with 7-OH; any more-than-trivial exposure warrants ED evaluation. [EC]
If the composition or concentration cannot be confidently established, manage it as a high-potency/uncertain product. [EC]
This approach is supported by extreme variability in the commercial 7-OH market. DEA reports that the concentration of commercial 7-OH products varied significantly, ranging from 1 mg to 700 mg in a single dose or serving. [6; P/DEA]
Commercial analytical studies have also identified substantial discrepancies between labeled and measured alkaloid composition. A 2026 analysis of commercial tablets, films, and liquid shots found frequent label inconsistencies, including unlisted alkaloids and listed alkaloids that were absent. [2–4; P]
Tolerance does not qualify users of these products for the Step 4 home pathway; any more-than-trivial exposure warrants ED evaluation. [EC]
Mitragynine is the predominant alkaloid in conventional botanical kratom. Experimental studies describe relatively low-efficacy or partial μ-opioid receptor agonism together with activity at adrenergic and serotonergic systems. [7,8; M]
7-OH has substantially greater μ-opioid activity than mitragynine.
Mitragynine undergoes CYP3A-mediated metabolism to 7-OH. A controlled human itraconazole study demonstrated reduced 7-OH formation and increased mitragynine exposure, supporting an important CYP3A contribution. [9; H1]
7-OH can convert in human plasma in vitro to mitragynine pseudoindoxyl, a potent μ-opioid agonist. The clinical contribution of this conversion following commercial 7-OH exposure remains uncertain. [10; M]
After oral botanical kratom, mitragynine and 7-OH generally reach peak plasma concentrations within approximately 1–2 hours. Mitragynine has a substantially longer terminal elimination phase than the period of peak clinical effect, so terminal half-life should not independently determine disposition. [11; H1]
After a concentrated kratom extract standardized to 39.5% mitragynine, mitragynine and 7-OH peaked at a median of about 1.3–2.3 hours after single and repeated daily doses. Repeated dosing produced higher 7-OH-to-mitragynine ratios, and the extract gave greater mitragynine exposure than leaf powder or tea at comparable doses. [35; H1]
Experimental findings suggesting that mitragynine may produce less respiratory depression than conventional full μ-opioid agonists should not be extrapolated to concentrated 7-OH.
7-OH causes substantial respiratory depression in animal models, with naloxone reversal demonstrated experimentally, and severe naloxone-responsive human toxicity has now been reported. [12,13; H3 + M]
Possible acute findings include:
Nausea or vomiting
Dizziness
Drowsiness
Miosis
Ataxia
Tremor
Anxiety
Agitation
Diaphoresis
Tachycardia
Hypertension
Severe toxicity may include:
Profound CNS depression
Bradypnea or apnea
Hypoxemia
Coma
Aspiration
Seizure
Hypotension
QTc prolongation
QRS widening
Ventricular dysrhythmia
Brugada-pattern ECG abnormality
Hyperthermia
Rhabdomyolysis
Acute kidney injury
Respiratory failure [12,14–18; H2/H3]
In national poison-center surveillance from 2015–2025, multiple substances were involved in 184 of 233 reported kratom-associated deaths. The dataset does not reliably distinguish botanical kratom from concentrated 7-OH or semisynthetic products, so it cannot establish formulation-specific mortality. [14; H2]
Psychosis and delirium have been reported after prolonged heavy 7-OH use and cessation, but this currently remains case-level evidence rather than an established common overdose phenotype. [19; H3]
In a retrospective NPDS analysis of 169 single-substance kratom ingestions in children <12 years (median age 2 years; 97% unintentional), 7-OH or MP exposures had higher odds of serious respiratory effects (OR 2.5; 95% CI 1.1–5.4) and serious neurologic effects (OR 2.6; 95% CI 1.2–5.4) than mitragynine exposures, and naloxone was used approximately twice as often. [5; H2]
These data support conservative pediatric disposition but do not establish a toxic dose, a lick/taste threshold, or an observation interval.
Central opioid-type respiratory depression is the most clinically important acute pulmonary effect.
A 2026 systematic review of case reports and forensic series proposed additional pulmonary phenotypes including:
ARDS/diffuse acute lung injury
Diffuse alveolar hemorrhage
Eosinophilic or hypersensitivity pneumonitis
Pulmonary edema/congestion
Central respiratory depression
These remain case-level associations rather than established kratom-specific pulmonary syndromes. [17; H3-SR]
Persistent hypoxemia after restoration of adequate ventilation should prompt evaluation for aspiration, pulmonary edema, ARDS, alveolar hemorrhage, infection, pulmonary embolism, and other causes of acute lung injury.
The authoritative ED-referral criteria for this guideline are contained in Step 1 (Figure 1).
This section deliberately does not reproduce a second list.
If any Step 1 criterion is present → Recommend ED evaluation.
Steps 2–5 define disposition when no immediate ED criterion is present.
The ED management flowchart (Figure 2) summarizes this section.
For clinically important exposures:
Continuous pulse oximetry
Frequent respiratory assessment
Cardiac monitoring when appropriate
Serial mental-status examination
Consider continuous capnography with significant sedation
Temperature monitoring with agitation, seizure, or hyperthermia
With supplemental oxygen, a normal SpO₂ does not exclude hypoventilation. Use capnography when available; otherwise assess respiratory rate, depth, and mental status frequently.
Obtain an ECG for:
Moderate or severe poisoning
Seizure
Syncope
Chest pain
Significant palpitations
Symptomatic high-potency exposure
Important cardiotoxic coingestant
Relevant electrolyte abnormality
Repeat when abnormal or when clinical status changes.
Testing should be severity-directed. Consider:
Point-of-care glucose
Electrolytes
Magnesium
Creatinine
Blood gas for significant hypoventilation
Lactate in severe poisoning
CK after seizure, hyperthermia, severe agitation, or prolonged immobilization
AST, ALT, alkaline phosphatase, bilirubin, and INR when hepatic injury is suspected
Acetaminophen concentration after intentional or uncertain overdose
Salicylate concentration when clinically appropriate
Pregnancy testing when relevant
Routine opioid immunoassays generally do not detect mitragynine or 7-OH.
A negative routine opioid screen does not exclude kratom-derived opioid toxicity.
Ventilation takes priority over antidote administration.
Provide:
Airway positioning
Suction
Supplemental oxygen
Bag-mask ventilation when spontaneous ventilation is inadequate
Endotracheal intubation when ventilation or airway protection cannot otherwise be maintained
Do not delay ventilation while waiting for naloxone.
Use naloxone for clinically significant opioid-type respiratory depression or apnea. Isolated sedation with adequate ventilation is not, by itself, an indication for naloxone.
The endpoint is adequate spontaneous ventilation, not necessarily complete wakefulness. Abrupt full reversal in an opioid-dependent patient can precipitate severe withdrawal, vomiting with aspiration risk, and agitation.
Naloxone 0.04–0.4 mg IV initially. Use the lower end when opioid dependence is possible.
Escalate every 2–3 minutes according to respiratory response.
When effective bag-mask ventilation is established and maintained:
Ventilate first.
Titrated naloxone remains appropriate: 0.04–0.4 mg IV, escalating every 2–3 minutes, particularly when opioid dependence is possible.
Use larger initial doses when oxygenation cannot be maintained despite assisted ventilation.
When effective ventilation cannot be assured (prehospital, layperson response, or failed bag-mask ventilation):
Naloxone 2 mg IV/IM, or standard intranasal naloxone, typically 4 mg/device.
Repeat every 2–3 minutes as needed, and continue rescue breathing or assisted ventilation.
Failure of a single dose does not demonstrate naloxone resistance.
Opioid-naive child:
Naloxone 0.1 mg/kg IV/IO/IM, generally maximum 2 mg for the initial dose. Repeat according to respiratory response.
Adolescent or child with possible opioid dependence (including regular 7-OH or other high-potency opioid use):
When ventilation is supported, use the adult titrated approach (0.04–0.4 mg IV, escalating every 2–3 minutes) rather than weight-based full-reversal dosing. [EC]
When effective ventilation cannot be assured, use the weight-based dose above.
Newborn of a mother with chronic kratom, 7-OH, or other opioid use:
Prioritize ventilation. Naloxone may precipitate acute neonatal withdrawal, including seizures. [EC]
When repeated boluses are necessary, a reasonable starting infusion is approximately two-thirds of the total effective reversal bolus per hour.
This dosing approach derives from naloxone pharmacokinetic modeling and established opioid-toxicology practice rather than kratom-specific trials. [20; H2/extrapolated]
ACMT reports that naloxone has been effective in 7-OH respiratory depression based on animal evidence and human case reports. [1,12,13; H3 + M, ACMT guidance]
Treat seizures with benzodiazepines according to standard toxicologic seizure management.
Because concurrent opioid-type respiratory depression may be present:
continuously reassess ventilation;
use pulse oximetry;
prefer capnography with substantial sedation;
maintain immediate readiness for assisted ventilation.
Seizures are reported after kratom exposure itself (see Clinical Manifestations) but are atypical for an uncomplicated pure opioid toxidrome.
Evaluate for:
Tramadol/O-desmethyltramadol
Bupropion
Stimulants
Serotonergic drugs
Adulterants
Hypoglycemia
Electrolyte abnormalities
Hypoxemia
Benzodiazepines may also be used for clinically significant agitation, with the same respiratory precautions.
Isotonic crystalloid initially
Norepinephrine for persistent clinically significant hypotension after appropriate volume assessment [EC]
Correct potassium, magnesium, and calcium abnormalities
Avoid additional QT-prolonging drugs when feasible
Continue cardiac monitoring
Adults: magnesium sulfate 2 g IV
Children: magnesium sulfate 25–50 mg/kg IV, maximum 2 g
Defibrillate unstable or pulseless patients.
For recurrent acquired pause-dependent torsades despite correction and magnesium, consider overdrive pacing or isoproterenol with cardiology/medical-toxicology input. [EC]
No kratom-specific trial supports sodium bicarbonate.
For progressive QRS widening from baseline, or QRS ≥100 ms with a terminal R wave in aVR or another ECG feature consistent with sodium-channel blockade, or ventricular dysrhythmia suggesting sodium-channel blockade:
Sodium bicarbonate 1–2 mEq/kg IV is reasonable while obtaining medical-toxicology consultation. The mechanism of QRS widening after kratom or 7-OH exposure is not established. [EC]
Compare with any available baseline ECG and evaluate for coexposure, since a QRS of 100–120 ms may reflect pre-existing conduction disease rather than acute sodium-channel blockade.
Repeat according to ECG response while monitoring potassium and systemic pH.
Do not administer bicarbonate solely for QTc prolongation or an isolated Brugada-pattern ECG without evidence of conduction delay. [18; H3]
Activated charcoal is generally not indicated for isolated kratom or 7-OH ingestion. [EC]
Potential benefit is uncertain, while evolving opioid-type sedation creates an aspiration risk.
Consider charcoal primarily when a separate dangerous coingestant independently warrants gastrointestinal decontamination and the airway is reliably protected.
If used: activated charcoal approximately 1 g/kg, maximum 50 g.
Do not induce vomiting.
There is no routine role for gastric lavage, whole-bowel irrigation, or multidose activated charcoal.
There is no established role for hemodialysis, hemoperfusion, or urinary manipulation solely to increase elimination of mitragynine, 7-OH, or related compounds.
Use extracorporeal therapy only for another established indication.
Observation intervals are expert-consensus operational recommendations rather than validated prediction rules.
Use Step 6 (summarized in Figure 2) as the single source of truth for observation clocks.
After recurrent respiratory depression, monitored step-down care is acceptable only when continuous respiratory monitoring and immediate airway intervention are available.
Use ICU-level care for repeated recurrence, naloxone infusion, assisted ventilation, escalating antidote requirements, hemodynamic instability, major pulmonary complications, or lack of an appropriate high-acuity monitored unit.
Pharmacodynamic interactions with other respiratory depressants are the immediate clinical concern.
Alcohol, conventional opioids, benzodiazepines, sedative-hypnotics, and other CNS depressants can increase respiratory risk.
A controlled human crossover study using 2 g of kratom tea increased midazolam AUC by approximately 39% and Cmax by approximately 50%, supporting intestinal CYP3A inhibition at that exposure. [21; H1]
In the same study, kratom did not meaningfully alter dextromethorphan/dextrorphan pharmacokinetics despite strong in-vitro CYP2D6 inhibition signals. [21; H1]
Therefore:
Human evidence supports a CYP3A interaction signal.
Clinically meaningful CYP2D6 inhibition was not demonstrated at the studied human dose.
Different effects after larger doses, chronic exposure, or concentrated extracts cannot be excluded.
Unexpected toxicity should prompt consideration of adulteration or contamination.
The marketed preparation Krypton contained O-desmethyltramadol and was associated with fatal intoxications. [22; H3/forensic]
A 2017–2018 multistate outbreak linked contaminated kratom to 199 Salmonella infections across 41 states. [23; H2/public-health surveillance]
FDA testing of 30 kratom products identified concerning concentrations of lead and nickel in multiple samples. [24; P/FDA]
Consider another substance or contaminant when the presentation includes:
Seizure
Serotonergic toxicity
Unexpectedly prolonged opioid toxicity
Fever and diarrhea suggesting infectious disease
Subacute neurologic or hematologic findings
Findings inconsistent with the labeled product
Whenever possible, document:
product name;
manufacturer;
lot number;
photograph of the packaging;
labeled alkaloid concentrations;
whether remaining product is available.
Kratom-associated drug-induced liver injury is among the better-characterized non-opioid complications of repeated kratom use.
In the prospective U.S. Drug-Induced Liver Injury Network, 11 adjudicated cases were attributed to kratom. Median latency to symptoms was 14 days (range 5–28 days). Six had mixed injury, two cholestatic injury, and three hepatocellular injury. All developed jaundice, most required hospitalization, and all ultimately recovered. [25; H2]
A broader review of the earlier literature found a median symptom latency of approximately 20.6 days, with reported cases ranging from 2 to 49 days after exposure. [26; H3-SR]
Accordingly, a compatible history may extend from a few days to approximately 7 weeks after starting kratom, although presentation around the second to fourth week is more typical.
A 2026 systematic review identified 32 patients across 31 published studies. The accumulated case literature was predominantly cholestatic, and four reported patients progressed to liver transplantation. [27; H3-SR]
Evaluate for kratom-associated liver injury when patients develop:
Jaundice
Dark urine
Pruritus
Persistent nausea
Right-upper-quadrant discomfort
Unexplained fatigue
Evidence of impaired hepatic synthetic function
Management includes:
Discontinue the suspected product
Evaluate competing causes of liver injury
Trend AST/ALT, alkaline phosphatase, bilirubin, and INR as appropriate
Obtain hepatology consultation for significant synthetic dysfunction, severe jaundice, encephalopathy, or progressive injury
Routine serial liver testing is not required after a small isolated asymptomatic acute exposure. [EC]
Regular kratom use, and particularly concentrated 7-OH use, can produce tolerance, craving, physical dependence, opioid-like withdrawal, and substance use disorder.
Withdrawal may include:
Restlessness
Anxiety
Myalgias
Diaphoresis
Rhinorrhea
Abdominal cramping
Nausea or vomiting
Diarrhea
Insomnia
Tachycardia
Hypertension
[28–30; H3]
Buprenorphine has been used successfully in published 7-OH cases and small series. [28–30; H3]
For standard induction, wait for objective opioid withdrawal.
A COWS score around 8–12 or greater may support initiation, but there is no validated kratom- or 7-OH-specific threshold. [EC]
Low-dose buprenorphine initiation may be considered when there is concern for precipitated withdrawal, including:
Heavy high-potency 7-OH use
Uncertain duration of opioid effect
Concurrent fentanyl or methadone exposure
Previous precipitated withdrawal
Inability to tolerate abstinence
[29; H3]
ACMT notes successful treatment of kratom/7-OH dependence using medications for opioid use disorder including buprenorphine and methadone. [1; ACMT guidance]
Methadone treatment for OUD should follow the applicable regulated treatment pathway.
Symptom-directed options may include:
clonidine when hemodynamically appropriate;
ondansetron;
loperamide;
NSAIDs;
acetaminophen.
Patients with dependence, escalating use, recurrent overdose, or OUD should be offered:
Buprenorphine when appropriate
Methadone-treatment referral when appropriate
Addiction-medicine follow-up
Take-home naloxone
Harm-reduction counseling
Do not simply advise a heavily dependent patient to abruptly stop high-dose 7-OH without addressing withdrawal and access to treatment.
Maternal stabilization takes priority.
Do not withhold naloxone from a pregnant patient with clinically important opioid-type respiratory depression.
Published prenatal-exposure literature supports a neonatal opioid-withdrawal signal after chronic maternal kratom use. Available evidence remains limited to case-level literature and does not establish incidence. [31; H3-SR]
Newborns with substantial chronic prenatal kratom or 7-OH exposure should be monitored according to local neonatal withdrawal protocols.
Human lactation pharmacokinetic and safety data remain inadequate.
Kratom and concentrated kratom-derived opioid products should generally be avoided while breastfeeding. [EC]
Before ED discharge confirm:
Baseline mental status
Normal spontaneous ventilation
Stable room-air oxygenation or established baseline
Stable vital signs
Completion of the applicable observation period
No recurrent toxicity
No clinically significant unresolved ECG abnormality
Safe ambulation
Adequate oral intake when appropriate
Psychiatric assessment after self-harm exposure
After clinically significant opioid-type toxicity:
Provide take-home naloxone
Review respiratory-depressant interactions
Screen for dependence or OUD
Offer MOUD linkage when appropriate
For regular kratom or 7-OH users, advise return for jaundice, dark urine, pruritus, or persistent nausea; kratom-associated liver injury can present days to about 7 weeks after starting use (see Hepatotoxicity).
For significant, unusual, or emerging toxicity:
Record exact product/formulation
Photograph packaging
Record labeled alkaloid concentrations
Record manufacturer and lot
Record dose and timing
Record current tolerance and any recent interruption in use
Record coexposures
Report through the regional poison center
Consider FDA MedWatch for serious product-related adverse events
Product-level documentation is important because surveillance datasets frequently cannot distinguish conventional botanical kratom from concentrated or semisynthetic products.
Major limitations include:
No validated toxic dose for botanical kratom or 7-OH
No validated pediatric toxic-dose threshold, lick/taste threshold, or observation interval. Comparative pediatric evidence for 7-OH/MP is limited to retrospective poison-center data in children under 12 years, without prospective disposition-rule validation. [5; H2]
No validated home-triage rule
No prospective disposition rule
No validated observation duration
No controlled clinical naloxone trial specific to kratom/7-OH
Limited human pharmacokinetic data for purified 7-OH and concentrated extracts [35]
No reliable way to confirm actual product composition at the time of a call; labels may be inaccurate [3,4,34]
Major commercial-product variability
Frequent polysubstance exposure
Limited evidence for newer modified alkaloids
Cardiac and pulmonary complications supported predominantly by mechanistic or case-level evidence
Pregnancy evidence limited to case reports
MOUD literature for 7-OH limited primarily to case reports and small retrospective series
The [EC] recommendations in this guideline are explicit operational decisions made where poison-center practice requires a disposition despite incomplete direct evidence.
This section is informational and does not define toxic doses or clinical disposition thresholds.
DEA temporarily placed these three substances into federal Schedule I effective August 26, 2026 through August 26, 2028, unless the order is extended or superseded. [32]
DEA published a July 6, 2026 notice of intent concerning temporary Schedule I placement of 7-OH above a specified threshold.
The proposed threshold includes:
Botanical Mitragyna speciosa material containing >0.050% 7-OH on a dry-weight basis
Synthetic or processed alternative articles containing >0.050% 7-OH by the applicable concentration measure or >1.00 mg of 7-OH per article
[6]
The same notice also documents wide per-serving variability in commercial 7-OH products.
HHS extended the threshold-related comment period through September 10, 2026. [33]
A Federal Register check on October 11, 2026, of DEA rules published from August 1 through October 9, 2026, identified no temporary scheduling order for 7-OH itself. This was a check of the Federal Register only.
Regulatory thresholds are not toxicity thresholds and should not be used to determine home versus ED disposition.
Keep reading