Rivastigmine for Antimuscarinic Delirium
Published on 23 May 2025 · Updated 14 Nov 2026

Published on 23 May 2025 · Updated 14 Nov 2026
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/guidelines/clinical-guideline-rivastigmine-as-a-substitute-for-physost
Evidence-Informed Clinical Practice Advisory
Evidence reviewed: November 14, 2026
Author: Omid Mehrpour, MD, FACMT
Hospital-based management of clinically significant central antimuscarinic delirium. This advisory is intended for emergency physicians, medical toxicologists, poison-center professionals, pharmacists, and critical-care clinicians. It is not a standing medication order set.
Overall certainty of evidence for antidotal efficacy: LOW.
Rivastigmine may be considered under medical-toxicology guidance for selected patients with antimuscarinic delirium in two distinct clinical circumstances:
A. Initial substitute: When physostigmine is unavailable or cannot be administered after a patient-specific risk assessment.
B. Adjunct or maintenance therapy: To help sustain control of persistent or recurrent delirium after initial physostigmine reversal.
These indications have different evidence bases and must not be combined when interpreting efficacy. Both depend mainly on uncontrolled reports and retrospective cohorts. Most patients in the largest published cohort had already received physostigmine before rivastigmine.
All rivastigmine regimens for acute poisoning are off-label. The available evidence does not establish a universally safe dose, route, or repeat-dose regimen.
A contraindication to physostigmine does not automatically make rivastigmine safe. Appropriate treatment requires ECG screening, assessment for cardiotoxic co-ingestants and seizures, careful dosing, continuous or close monitoring, and access to resuscitation equipment.
A randomized trial in patients with multifactorial ICU delirium was stopped after a possible mortality signal. Although it did not study antidotal treatment of antimuscarinic poisoning, it remains an important safety limitation.
This guidance integrates specialist antidote protocols, regulatory product information, observational poisoning studies, and randomized evidence from a different delirium population. It does not represent a formal GRADE guideline or an independently validated treatment protocol. [1], [2], [3], [4], [5], [6], [7], [8]
Clinical warning
Rivastigmine for antimuscarinic delirium is off-label and must not be used for isolated peripheral antimuscarinic signs, unexplained coma, or nonspecific ICU delirium. Obtain an ECG and assess QRS/PR intervals, bradycardia, seizure risk, co-ingestants, airway and hemodynamics before a cholinesterase inhibitor. Physostigmine is preferred when suitable and available. A physostigmine contraindication does not make rivastigmine safe. Oral and patch regimens are specialist examples, not standing orders. Do not automatically escalate patches, apply multiple patches, or combine oral and patch dose numbers. Monitor for seizures, bradycardia, bronchospasm and cholinergic toxicity; keep atropine and resuscitation equipment available. Observe at least 12 hours after the last oral dose or patch removal under Canadian expert guidance, longer if clinically indicated.
This advisory uses three editorial recommendation labels:
Safety requirement: Precautions supported by pharmacology, prescribing information, or established resuscitation practice.
Conditional suggestion: A potentially useful approach supported by low-certainty antidotal evidence.
Insufficient evidence: An intervention for which routine protocolization cannot be justified.
These labels are not a formal GRADE assessment.
Safety requirement
Confirm a convincing central antimuscarinic syndrome characterized by delirium, disorientation, hallucinations, incoherent speech, dangerous agitation, or marked inattention, usually accompanied by compatible peripheral manifestations.
Do not use rivastigmine to treat isolated tachycardia, mydriasis, dry mouth, or other peripheral findings without clinically important central delirium. [1], [2], [9]
Safety requirement
Obtain a 12-lead ECG before considering a cholinesterase inhibitor. Assess for sodium-channel blockade, conduction abnormalities, bradycardia, hemodynamic instability, seizures, relevant co-ingestants, and airway compromise.
High-dose diphenhydramine can independently cause QRS widening and seizures. Neither physostigmine nor rivastigmine reverses this cardiotoxic mechanism. [1], [2], [3], [4], [10]
Conditional suggestion
For an appropriately selected patient requiring rapid antidotal reversal, use available IV physostigmine preferentially.
When physostigmine is unavailable or cannot be administered, consider oral rivastigmine only after a patient-specific safety review and poison-center or medical-toxicology consultation.
The patient must be able to receive enteral medication safely. A slow transdermal approach must not substitute for immediate stabilization. [1], [2], [5], [6], [7], [11]
Conditional suggestion
After successful physostigmine reversal, selected patients with recurrent or anticipated prolonged antimuscarinic delirium may be considered for rivastigmine to sustain control.
This indication must be assessed separately from use as an initial substitute.
The available evidence does not establish that rivastigmine independently prevents recurrence. [5], [12], [13]
Safety requirement
Do not:
Start a 13.3 mg/24-hour patch automatically because a patient weighs more than 100 kg.
Escalate patch strength simply because agitation persists.
Apply multiple patches as routine treatment.
Combine oral dose amounts and transdermal delivery rates into an invented cumulative maximum.
Treat published poisoning doses as validated, FDA-approved antidote regimens.
Safety requirement
Use continuous or closely supervised cardiac and respiratory monitoring during active treatment.
Ensure that airway equipment, resuscitation resources, and atropine are immediately accessible.
Identify and manage the causative toxicant and any co-ingestants rather than treating delirium alone. [1], [4], [15], [16]
Conditional suggestion
The Canadian Antidote Guide recommends observation for at least 12 hours after the final oral rivastigmine dose or patch removal.
Extend monitoring for persistent delirium, prolonged or uncertain toxicant exposure, co-ingestants, abnormal ECG findings, unusual dosing, relevant comorbidities, or incomplete recovery.
This is a specialist-guidance minimum, not a validated discharge threshold. [1]
Insufficient evidence
Pediatric regimens, oral–patch combinations, high-dose or multiple-patch therapy, and nonstandard administration routes lack adequate comparative evidence for routine use.
The Ontario Poison Centre provides a specific oral–patch regimen and ceiling, but these do not establish universal safety or pharmacologic equivalence between routes. [1], [4], [14], [17], [18]
Safety boundary
Do not extrapolate rivastigmine use to nonspecific ICU delirium, unexplained coma, or CNS depression without establishing an antimuscarinic mechanism.
A randomized ICU-delirium trial was terminated after a possible mortality signal. [8]
Antimuscarinic toxicity results from blockade of central and peripheral muscarinic acetylcholine receptors.
Central findings may include:
Delirium
Hallucinations
Severe inattention
Agitation or unsafe behavior
Disorientation
Incoherent speech
Altered cognition
Peripheral manifestations may include:
Tachycardia
Mydriasis
Dry skin and mucous membranes
Flushing
Urinary retention
Reduced bowel motility
Severe or mixed poisoning may additionally cause hyperthermia, seizures, rhabdomyolysis, aspiration, and cardiotoxicity.
The precise toxicant and co-ingestants should be established whenever possible.
For broader syndrome recognition and differential diagnosis, see Anticholinergic Toxidrome: Symptoms, ECG Clues, Physostigmine, Rivastigmine, and Emergency Treatment.
Physostigmine is a centrally acting, reversible acetylcholinesterase inhibitor capable of reversing antimuscarinic delirium within minutes of IV administration.
Rivastigmine inhibits both acetylcholinesterase and butyrylcholinesterase and enters the central nervous system.
Its onset is slower, while its clinical activity can be longer.
Plasma elimination half-life must not be equated with the duration of cholinesterase inhibition or clinical effect.
Neither drug reverses concurrent sodium-channel blockade or other non-antimuscarinic toxic effects. [1], [2], [3], [4]
Characteristic | Physostigmine | Rivastigmine |
|---|---|---|
Primary clinical role | Rapid reversal in selected patients | Possible substitute or maintenance adjunct |
Mechanism | Reversible acetylcholinesterase inhibition | Carbamate-mediated inhibition of acetylcholinesterase and butyrylcholinesterase |
CNS activity | Yes | Yes |
Routes used in poisoning | IV | Oral, transdermal; limited NG reports |
Onset | Usually minutes | Slower; varies by route |
Clinical evidence | More established antidotal experience | Mainly uncontrolled reports and retrospective cohorts |
Main precautions | Bradycardia, seizures, conduction abnormalities, mixed cardiotoxic poisoning | Similar screening concerns plus delayed and prolonged cholinergic effects |
Consider only for persistent moderate or severe central antimuscarinic delirium when:
Physostigmine is unavailable or cannot be administered.
An antidotal intervention offers meaningful benefit.
Immediate reversal is not required.
ECG and clinical screening identify no prohibitive findings.
The intended route is appropriate.
Medical-toxicology guidance is available.
Direct evidence for rivastigmine given without previous physostigmine remains very limited. [1], [6], [7], [11]
Consider selectively after initial effective physostigmine reversal when:
Delirium has recurred or is likely to persist.
The causative toxicant has a prolonged course.
Clinical reassessment remains consistent with central antimuscarinic toxicity.
The patient can be monitored appropriately.
In the 50-patient Chiew cohort, 43 patients (86%) had received physostigmine before rivastigmine. This is predominantly evidence involving sequential treatment, not independent initial-substitute treatment.
Reports involving diphenhydramine and depot olanzapine suggest possible maintenance benefit, but cannot establish whether improvement resulted from rivastigmine, earlier physostigmine, other treatment, or natural recovery. [5], [12], [13]
A patient who is unsafe for physostigmine because of seizures, QRS widening, shock, or important conduction disease is not automatically safe for rivastigmine.
Before considering rivastigmine:
Document the suspected drug, formulation, exposure time, estimated amount, and co-ingestants.
Evaluate alternative causes of delirium.
Record serial vital signs, glucose, temperature, mental status, and airway protection.
Obtain a 12-lead ECG and review rhythm, PR interval, QRS duration, QTc, and sodium-channel-blockade findings.
Screen for seizures, bradycardia, AV block, hypotension, severe asthma or bronchospasm, urinary or gastrointestinal obstruction, and interacting medicines.
Obtain poison-center or medical-toxicology consultation.
IV physostigmine remains the more rapidly acting option for a suitable patient.
One contemporary Canadian protocol describes the following:
Population | Initial IV dose | Repeat treatment |
|---|---|---|
Adults | 0.5 mg slowly IV | Reassess and repeat every 20–30 minutes if indicated; maximum 2 mg in first hour |
Children | 0.01–0.02 mg/kg IV, maximum 0.5 mg/dose | Reassess and repeat every 20–30 minutes if indicated; maximum 2 mg in first hour |
Selected prolonged cases have been managed with specialist-directed physostigmine infusions.
The Canadian guide describes experience with:
Adults: up to 2 mg/hour
Children: up to 0.03 mg/kg/hour, maximum 2 mg/hour
These are specialist-protocol examples, not default infusion orders.
Follow local approved procedures and maintain atropine and resuscitation equipment at the bedside. [2]
Important concerns include:
Suspected sodium-channel blockade, such as QRS >100 ms not explained by baseline conduction disease
Significant PR prolongation or heart block
Bradycardia
Hemodynamic instability
Active seizures or important seizure risk
Severe bronchospasm
Confirmed salicylate hypersensitivity when using physostigmine salicylate
Do not assume a positive tricyclic antidepressant urine immunoassay establishes tricyclic poisoning; assess the ECG, exposure history, and clinical findings together.
Similarly, a normal ECG does not exclude every dangerous co-ingestant.
Diphenhydramine itself may cause sodium-channel blockade and wide QRS complexes.
For the specific ECG mechanism, see Why Does Diphenhydramine Overdose Widen the QRS?.
All dosing approaches below are off-label for acute poisoning.
The FDA-approved dementia regimens start at substantially lower doses and require gradual titration:
Oral rivastigmine: initially 1.5 mg twice daily
Transdermal rivastigmine: initially 4.6 mg/24 hours
Acute-poisoning reports and specialist antidote protocols must not be presented as FDA-approved initiation schedules. [3], [4]
Evidence source | Reported dosing | Interpretation |
|---|---|---|
Canadian Antidote Guide | 6 mg PO once; reassess after 60–90 minutes. If tolerated but delirium persists, consider 3 mg PO every 1–2 hours for up to two additional doses. Protocol maximum 12 mg PO in 24 hours | Local expert protocol, not a validated dose-response rule |
Utah poison-center series, 30 patients | Most common initial dose 3 mg; reported initial range 1.5–4.5 mg. Thirteen patients received repeat doses | Demonstrates practice variability |
Karousatos and Murphy | 4.5 mg PO initially, with repeat treatment | Individual case report |
Van Kernebeek et al. | 1.5 mg PO in severe procyclidine intoxication | Individual case, not a general starting dose |
Implementation requirements
Choose and document an individualized specialist-directed dose according to:
Severity of the toxidrome
Patient size and age
Comorbidities
Other medications
Enteral tolerance
Prior antidotal treatment
Before each subsequent dose, reassess mental status, ECG, hemodynamics, ventilation, and cholinergic adverse effects.
Do not give 3 mg every hour automatically.
The Canadian 12 mg/24-hour limit applies to its specified oral regimen. It cannot be combined arithmetically with patch delivery rates.
University of Utah teaching material describes hourly repeat dosing. This advisory favors clinical reassessment before each additional dose; that difference is a precautionary interpretation and does not prove that the Utah approach is unsafe. [1], [20]
Transdermal rivastigmine may be considered when the oral route is unsafe or impractical and immediate antidotal reversal is not required.
Published reports and specialist protocols commonly describe a 9.5 mg/24-hour patch.
Some specialist protocols permit consideration of 13.3 mg/24 hours in selected adults weighing more than 100 kg when the oral route is unavailable.
Weight above 100 kg does not automatically mandate the higher patch strength.
A patch has a slower and less predictable immediate clinical response than oral administration. A reported estimate of approximately eight hours to clinical effect is not a validated response time for individual patients. [1], [4], [9], [18], [20], [21]
Patch safety checklist
Apply to intact skin at a site permitted by current product labeling, commonly the upper back.
Document patch strength, application time, site, and planned removal time.
Inspect the patient for an existing rivastigmine patch and remove any previous patch before application.
Never cut a patch.
Do not apply multiple patches routinely.
Do not escalate strength simply because agitation remains present at an early reassessment.
Avoid prolonged external heating over the patch because heat may alter exposure.
The 2026 Watson case report described two 13.3 mg/24-hour patches, giving a combined labeled delivery rate of 26.6 mg/24 hours, following physostigmine treatment.
This single report does not justify routine multiple-patch treatment. [14]
Combination therapy has appeared in published reports and specialist protocols.
The Ontario Poison Centre's May 2026 document presents two alternative adult ceilings:
Up to 12 mg oral rivastigmine in 24 hours, or
6 mg orally plus one 9.5 mg/24-hour patch
In the Ontario sequence, if a patch is added after the initial 6 mg oral dose, no further oral rivastigmine is administered during the following 24 hours.
This is a local expert protocol, not a universally validated exposure-equivalence rule or general maximum. [18]
The patch strength expresses a delivery rate in mg/24 hours. It must not be added to an oral dose as though both values were equivalent amounts delivered over the same period.
For example, 6 mg PO + 9.5 mg/24 hours does not equal a validated “15.5 mg total dose.”
Choose one internally consistent specialist protocol and record each administered route separately.
Pediatric evidence is insufficient to establish a universal acute-poisoning regimen.
The Canadian Antidote Guide discusses, for selected children weighing less than 35 kg:
Initial 3 mg PO
If needed, up to two additional 1.5 mg oral doses
Alternatively, a 4.6 mg/24-hour patch in selected circumstances
It directs patients above 35 kg toward adult recommendations.
These are expert-protocol examples, not automatic weight-based orders. [1]
In a pediatric case report, a 7-year-old child weighing 37 kg received 0.75 mg orally approximately 26 hours after exposure. The child had previously experienced seizures and had received sedatives and diphenhydramine.
Delirium improved during subsequent hours, but natural recovery and co-treatment cannot be excluded.
This case does not validate a 0.75 mg starting dose or another pediatric regimen. [17]
Formulation caution
Commercial capsules are available in 1.5, 3, 4.5, and 6 mg strengths.
A dose below these strengths must not be prepared by improvised capsule splitting or opening.
When a nonstandard dose is contemplated, pharmacy should verify the availability and appropriate use of a 2 mg/mL oral solution, the exact calculation, and safe administration.
Pediatric rivastigmine requires pediatric toxicology and pharmacy involvement.
Oral capsules are inappropriate when swallowing or airway protection is unreliable.
Limited nasogastric (NG) experience exists.
Fratta and colleagues described an adult with antimuscarinic findings and depressed consciousness who received two 3 mg rivastigmine doses through an NG tube, followed by transdermal treatment and clinical improvement. [22]
This is an uncontrolled case and does not validate an NG dosing or escalation protocol.
When an enteral tube is present:
Confirm airway protection.
Select a pharmacy-approved formulation.
Verify tube compatibility.
Avoid assuming capsules can be opened or crushed.
Monitor closely for adverse effects.
A registered Alexandria University study also describes enteral administration, but registration does not establish efficacy or dosing safety. [23]
Intranasal rivastigmine and microemulsion formulations remain experimental drug-delivery research, not established clinical poisoning treatments. [24]
When feasible, use continuous ECG and pulse oximetry during active treatment with frequent reassessment of:
Blood pressure
Heart rate and rhythm
Mental status
Attention and orientation
Hallucinations
Agitation and unsafe behavior
Ventilation and airway protection
Need for additional sedatives
Monitor specifically for cholinergic toxicity:
Nausea, vomiting, diarrhea
Diaphoresis
Excess salivation
Bronchorrhea or bronchospasm
Bradycardia
Hypotension
Syncope
Seizures
Record patch application and removal times.
A delayed response does not independently justify increasing the patch dose.
The Canadian Antidote Guide recommends observing for at least 12 hours after the last oral dose or after patch removal. [1]
Extend observation for:
Persistent or recurrent delirium
Long-acting or uncertain causative drug
Mixed overdose
Residual cardiotoxicity
Unstable ECG
Cholinergic adverse effects
Important comorbidity
Unusual or off-protocol rivastigmine dosing
This recommendation is a specialist-guide minimum, not a validated clearance interval.
There is no validated time threshold defining rivastigmine treatment failure.
When clinically meaningful improvement is absent or the patient worsens, reassess:
Airway and ventilation
ECG findings
Glucose and temperature
Correct toxin identification
Co-ingestants
Seizures
Alternative diagnoses
Drug delivery and formulation
Treatment-related cholinergic effects
Seek specialist reassessment rather than automatically increasing a patch.
Oral improvement may occur over hours; transdermal treatment is generally slower.
In Greene's 22-patient retrospective report, all patients received a transdermal patch.
Fifteen patients also received oral rivastigmine.
Median reported symptom-resolution times were:
2 hours: oral plus patch
5 hours: patch alone
These were not randomized groups, and the study did not compare oral monotherapy with patch monotherapy. The observed difference cannot establish causal superiority. [9]
Continue standard toxicologic supportive care:
Secure airway and ventilation when indicated.
Establish IV access.
Correct fluid and electrolyte abnormalities.
Provide external cooling for significant hyperthermia.
Treat seizures promptly.
Assess urinary retention and need for bladder decompression.
For significant QRS widening suggesting sodium-channel blockade, use appropriate toxicology protocols. Rivastigmine is not a substitute for sodium bicarbonate when the clinical indication is present.
Benzodiazepines may be appropriate for seizures and immediately dangerous agitation, but large repeated doses can cause respiratory depression and complicate delirium assessment.
Avoid choosing strongly antimuscarinic antipsychotics solely to control antimuscarinic delirium without considering their potential to prolong the syndrome or contribute sedation and cardiotoxicity.
Dexmedetomidine may be considered as a sedative adjunct in selected monitored ICU patients with refractory agitation. It is not an antidote and may cause bradycardia and hypotension.
At the first signs of clinically important cholinergic toxicity:
Withhold additional rivastigmine.
Remove transdermal patches.
Assess airway, ventilation, circulation, and ECG.
Suction secretions and support ventilation if necessary.
Seek urgent poison-center, medical-toxicology, and resuscitation assistance.
Have atropine immediately available.
For adult symptomatic bradycardia with poor perfusion, the 2025 AHA ACLS algorithm recommends:
Atropine 1 mg IV
Repeat every 3–5 minutes
Maximum total 3 mg under that bradycardia algorithm
If ineffective, consider pacing or vasoactive infusions as directed by the relevant resuscitation algorithm. [15]
Important: The ACLS bradycardia dose ceiling is not a universal atropine ceiling for severe cholinergic poisoning with bronchorrhea.
For pediatric bradycardia with cardiopulmonary compromise from increased vagal tone or primary AV block, PALS guidance supports atropine 0.02 mg/kg IV/IO, with age-appropriate limits and local resuscitation procedures.
Correct inadequate oxygenation and ventilation first. [16]
Severe cholinergic bronchorrhea may require a different atropine-titration strategy under specialist direction.
Routine prophylactic atropine is not indicated.
Rivastigmine can prolong the action of succinylcholine-type neuromuscular blocking agents.
When intubation is anticipated, notify anesthesia and consider an appropriate nondepolarizing alternative, such as rocuronium, within the complete airway-management plan.
Do not assign a specific multi-day interaction duration without patient-specific evidence. [4]
Publication | Design / population | Main finding | Main limitation |
|---|---|---|---|
Greene, 2023 [9] | Retrospective letter, 22 patients; all received patches | Median resolution 2 h with oral + patch versus 5 h with patch alone | Nonrandomized; no oral-only group |
Chiew et al., 2024 [5] | Retrospective cohort, 50 patients | 43/50 received physostigmine first; additional parenteral intervention in 16/22 patch versus 9/28 oral | Prior physostigmine and indication confounding |
Lambson et al., 2025 [6] | Poison-center series, 30 patients | 20/30 reported improvement; most common starting dose 3 mg | Uncontrolled outcome attribution |
Berg et al., 2025 [7] | Retrospective series, 12 patients | No reported rivastigmine-attributed adverse events; 9 had co-ingestants | Very small, heterogeneous cohort |
Karousatos and Murphy, 2024 [11] | Adult case report | Initial oral dose 4.5 mg, additional therapy needed | Single patient |
Whitledge et al., 2023 [12] | Diphenhydramine case | Physostigmine followed by 9.5 mg/24 h patch | Cannot separate treatment effects |
Fratta et al., 2023 [22] | Adult case | Two 3 mg NG doses followed by patch | Uncontrolled; NG protocol not validated |
Fotheringham et al., 2025 [13] | Two depot-olanzapine cases | Physostigmine reversal followed by rivastigmine | Two cases, specific syndrome |
Yakey et al., 2023 [17] | Pediatric case | 0.75 mg given late in a complicated course | Significant confounding |
Gilbert et al., 2025 [21] | Diphenhydramine case and review | Improvement after 9.5 mg/24 h patch | Single case |
Watson et al., 2026 [14] | Adult case report | Two patches totaling 26.6 mg/24 h after physostigmine | Does not justify routine high-dose treatment |
The Chiew cohort must not be presented as 50 independent initial-substitute treatments.
Of the 50 patients, 43 (86%) had already received physostigmine.
No bradycardia or gastrointestinal symptoms were reported after rivastigmine.
However, one patient with known epilepsy experienced a seizure seven hours after patch application and 1.5 hours after physostigmine.
Causality is uncertain, but the event must be disclosed in safety discussions. [5]
Additional reports involving 1.5 mg oral treatment for procyclidine poisoning and a 12 mg total course for diphenhydramine demonstrate heterogeneity rather than establishing a validated effective dose range.
Reviews by Godwin et al. and Mehrpour et al. provide clinical interpretation and rationale, but they must not be counted as additional independent clinical cohorts. [10], [19], [24], [25]
A critical safety signal
Van Eijk and colleagues studied rivastigmine added to usual haloperidol-based treatment for multifactorial ICU delirium.
The multicenter randomized trial planned to include 440 patients but stopped after enrollment of 104 following a data-monitoring-board recommendation.
Outcome | Rivastigmine | Placebo |
|---|---|---|
Patients | 54 | 50 |
Deaths | 12 (22%) | 4 (8%) |
Median delirium duration | 5.0 days | 3.0 days |
The mortality comparison had P=0.07, and the delirium-duration comparison P=0.06.
Neither met the conventional P<0.05 threshold, but the mortality imbalance was sufficiently concerning to contribute to early trial termination.
The investigators advised against rivastigmine for delirium in critically ill patients. [8]
Applicability limitation
This was not a trial of acute antimuscarinic overdose.
It involved a different delirium population, repeated treatment over days, and concomitant haloperidol.
The findings are not proof that a carefully selected short antidotal course causes increased mortality. They do, however, argue strongly against indiscriminate use for delirium of uncertain mechanism.
Overall certainty: LOW
Improvement following rivastigmine in uncontrolled poisoning studies cannot establish causation.
Major confounders include:
Previous physostigmine
Concurrent sedatives
Spontaneous toxicant elimination
Variation in overdose severity
Different rivastigmine routes and doses
Variable observation and outcome recording
Evidence for initial-substitute use consists mainly of uncontrolled reports and mixed-practice cohorts.
Evidence for maintenance after physostigmine is also uncontrolled and frequently confounded by prior therapy.
No completed randomized trial specifically demonstrating efficacy for acute antimuscarinic poisoning was identified in the literature reviewed through November 12, 2026.
This statement does not disregard the 2010 randomized trial; that trial studied a different ICU-delirium indication.
Evidence consists mainly of case reports and specialist protocols.
No universal pediatric poisoning dose can be recommended.
Use individualized pediatric medical-toxicology and pharmacy oversight.
Human antidotal-use evidence is insufficient.
Consider the risk of uncontrolled maternal poisoning versus the uncertain fetal or infant exposure.
Involve obstetric and medical-toxicology specialists.
Frailty, reduced physiologic reserve, and altered tolerability may increase treatment risk.
FDA labeling identifies additional adverse-effect concerns for patients weighing less than 50 kg.
Do not automatically apply the full adult poisoning protocol to smaller or frail patients.
Renal impairment may affect tolerability or pharmacokinetic handling in some patients.
Use individualized assessment; do not assume the absence of proven adjustment requirements establishes universal safety.
The Canadian Antidote Guide suggests dose reduction for mild-to-moderate impairment and treats severe hepatic impairment as an exclusion from its antidotal protocol.
U.S. product information instead describes limited or absent study data for severe impairment in relevant formulations.
A specialist-protocol exclusion is not automatically equivalent to a universal FDA-labeled contraindication.
Consider conservative treatment selection and specialist advice.
Important relative clinical exclusions include:
Bradycardia
Conduction disease
Significant hypotension
Seizure disorder
Severe asthma or COPD
Unexplained syncope
Assess each patient individually rather than applying a purely symptom-based antidote rule.
The expected course differs among diphenhydramine, doxylamine, benztropine, scopolamine, plant antimuscarinics, sustained-release formulations, and depot olanzapine.
Observation and maintenance treatment must follow the actual toxicant and clinical course.
Do not prescribe one universal patch duration.
When feasible, discuss off-label use, expected benefit, uncertainty, alternatives, and potential adverse effects with the capable patient or legally authorized surrogate.
In emergencies, follow applicable emergency-consent standards.
Document:
Treatment rationale
Toxicology consultation
Product and formulation
Dose and route
Patch location and removal plan
Clinical response
Adverse effects
Other treatments
Monitoring and disposition
The following text pathway is suitable for bedside reading and for use as the written companion to a future visual algorithm.
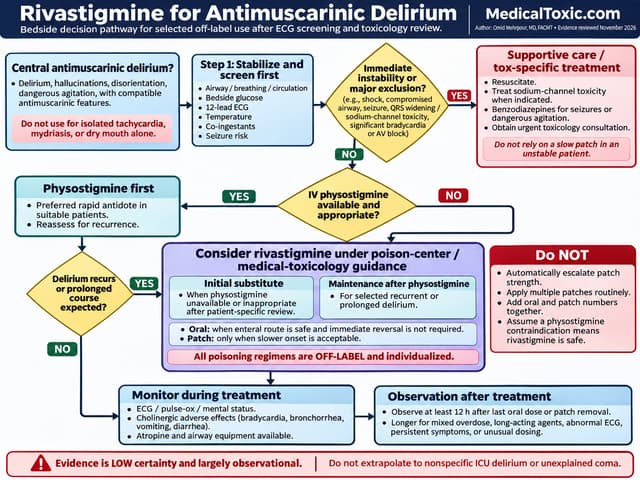
No: Investigate alternative diagnoses. Do not administer rivastigmine for peripheral antimuscarinic signs alone.
Yes: Proceed to Step 2.
Assess for:
Airway compromise
Respiratory failure
Shock
Seizures
Important conduction abnormalities
Significant bradycardia
Other serious co-ingestant effects
Yes: Stabilize, treat specific toxic complications, and seek urgent medical-toxicology advice. Do not wait for a slowly acting patch.
No: Proceed to Step 3.
Yes: Consider IV physostigmine under a local approved protocol and monitor for recurrence.
No: Under specialist guidance, consider off-label oral rivastigmine if swallowing and airway protection permit.
A transdermal approach may be considered only if its slower response is clinically acceptable.
A contraindication to physostigmine does not automatically establish eligibility for rivastigmine.
Reassess:
Exposure and expected duration
ECG
Clinical condition
Alternative diagnoses
Previous antidotal response
Selected patients may receive rivastigmine for maintenance under specialist direction.
The evidence is observational and substantially confounded by prior physostigmine.
Monitor cardiac and respiratory function.
Follow objective delirium improvement.
Monitor for cholinergic toxicity.
Do not escalate patch dosing automatically.
Stop rivastigmine and remove patches if clinically significant cholinergic toxicity develops.
Observe through clinical recovery and for at least 12 hours after the final oral dose or patch removal under Canadian guidance, longer when clinically necessary.
Trial registrations provide useful evidence-surveillance information, not proof of efficacy, clinical safety, or a validated dosing regimen.
The following status information reflects the targeted ClinicalTrials.gov review through November 12, 2026.
Registry | Study focus | Listed status | Interpretation |
|---|---|---|---|
Alexandria University; prospective single-arm rivastigmine study involving anticholinergic CNS depression and delirium | Completed | Published outcomes or posted results were not verified; registry doses are not established care | |
Washington University; randomized placebo-controlled rivastigmine trial in antimuscarinic delirium | Recruiting | Comparative prospective efficacy and safety evidence awaited | |
RIVA-AP; rivastigmine after initial physostigmine control | Suspended | Record attributes suspension to physostigmine unavailability at the site on June 1, 2026; not a reported rivastigmine safety finding |
The Alexandria registration includes CNS depression and patients with reduced consciousness.
Registration does not justify routine rivastigmine treatment for undifferentiated coma or low GCS without an established antimuscarinic syndrome.
This guideline is based on a targeted narrative review of PubMed-indexed literature and associated full texts concerning rivastigmine for antimuscarinic delirium.
Evidence reviewed includes:
Case reports
Retrospective cohorts
Poison-center studies
Clinical reviews
Canadian and provincial antidote protocols
University of Utah poison-center guidance
U.S. rivastigmine prescribing information
AHA resuscitation recommendations
ClinicalTrials.gov registrations
Search concepts included rivastigmine, physostigmine, antimuscarinic/anticholinergic delirium, oral treatment, transdermal treatment, poisoning, and toxicity.
The evidence review was completed through November 12, 2026.
This is not a registered systematic review, exhaustive evidence search, formal multidisciplinary consensus statement, or GRADE-rated guideline.
Predominantly uncontrolled antidotal efficacy evidence
No validated universal acute-poisoning dose
Limited independent initial-substitute evidence
Major confounding from previous physostigmine use
Insufficient pediatric comparative data
No validated high-dose patch regimen
No validated oral–patch equivalence
Limited experience with NG administration
No established intranasal poisoning route
No validated universal discharge clock
A safety signal from a randomized trial involving a different ICU-delirium indication
Author: Omid Mehrpour, MD, FACMT
Publisher: MedicalToxic.com (Medical Toxicology LLC)
Peer-review status: Independent external clinical review has not been documented for this author-revised edition.
Editorial relationship: Omid Mehrpour is CEO and co-founder of Medical Toxicology LLC, the publisher of MedicalToxic.com, and a coauthor of the 2025 article cited as reference 24.
No additional financial or institutional relationship is asserted without confirmation.
The 2025 Mehrpour et al. publication and the original MedicalToxic Guideline described oral 6 mg followed by additional 3 mg doses, higher-strength patches in adults over 100 kg, and a pediatric 4.6 mg/24-hour patch approach.
The revised advisory retains these regimens as examples of published or specialist practice but does not present them as mandatory, validated, or automatically weight-based orders.
It emphasizes individual patient selection, specialist review, careful monitoring, and explicit evidence limitations. [24]
Reassess this guideline within 12 months, or earlier following:
Publication of results from NCT07545382
Results from NCT06382649 or NCT06399679
Significant drug-label changes
New comparative effectiveness or safety evidence
Meaningful changes in physostigmine availability
Before institutional adoption, audit diagnostic eligibility, pretreatment ECG assessment, medical-toxicology consultation, dose/route documentation, co-treatments, adverse events, patch removal, recurrence, and disposition.
Local pharmacy and therapeutics (P&T) and medical-toxicology approval are required before converting this advisory into a medication order set.
Physostigmine remains the faster antidotal approach for selected patients with central antimuscarinic delirium.
Rivastigmine may be considered when physostigmine cannot be used or as maintenance after initial reversal, but these are different clinical uses supported by low-certainty evidence.
Select the patient before selecting the dose.
A reassuring ECG and exclusion of major co-toxicities are essential. Oral and transdermal regimens require individualized specialist decisions, and patch escalation should never be automatic.
A possible mortality signal in non-antimuscarinic ICU delirium reinforces the importance of using rivastigmine only for a convincing antimuscarinic indication.
This advisory does not replace medical-toxicology consultation or an approved institutional protocol.
Keep reading