Environmental and Occupational Toxicology
Battery Ingestion: Button Batteries, AA/AAA Cells, and Care
Omid Mehrpour
Post on 02 Jul 2024 · Updated 04 Nov 2026 · 14 min read

Omid Mehrpour
Post on 02 Jul 2024 · Updated 04 Nov 2026 · 14 min read
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/blogs/battery-ingestion-and-exposure-essential-preventi
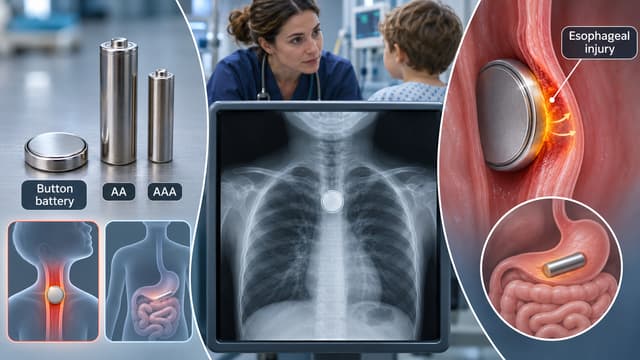
Battery ingestion is not a single type of exposure.
A swallowed button or coin battery can become lodged in the esophagus and generate hydroxide at the battery's negative pole, producing rapidly progressive alkaline tissue injury. A swallowed AA or AAA cylindrical battery usually behaves more like a large foreign body unless it is damaged, leaking, retained, or ingested in multiples.
That distinction changes both urgency and treatment.
For button batteries, serious esophageal injury can develop within approximately 2 hours, and a child may initially have few or no symptoms. [1]
For that reason, suspected button battery ingestion should never be managed like an ordinary swallowed coin.
A button or coin battery lodged in the esophagus is a medical emergency and should be removed immediately.
Do not wait for symptoms; serious injury can begin before a child looks ill.
For an eligible child aged 12 months or older who may have swallowed a lithium coin cell within the previous 12 hours, honey can be given while traveling to emergency care.
Honey does not replace urgent imaging or removal.
Other than eligible honey administration, patients should generally remain NPO until an esophageal battery has been excluded.
X-rays should adequately include the neck, esophagus, and abdomen when localization is required.
AA and AAA batteries have a different risk profile from button batteries; many intact cylindrical cells that reach the stomach can pass, but damaged, multiple, symptomatic, or retained batteries require specialist evaluation.
Heavy-metal poisoning is not the usual mechanism of injury from an intact swallowed battery.
Esophageal button-battery injury can continue to progress even after removal, with potentially delayed fistulas, bleeding, perforation, vocal-cord paralysis, and strictures.
Prevention has improved through Reese's Law, but button-battery ingestion remains a serious household hazard.
Button batteries are small enough to be swallowed easily, particularly by young children.
The greatest danger occurs when a battery lodges in the esophagus.
The main injury mechanism is not simply “battery acid leaking.”
Instead, contact between the battery and moist tissue completes an electrical circuit. Water is hydrolyzed around the negative pole, generating hydroxide and producing a highly alkaline local environment.
This can lead to liquefactive tissue necrosis.
Pressure injury and leakage may contribute, but electrochemical generation of hydroxide is the major mechanism of severe esophageal button-battery injury. [1]
A 2025 systematic review and meta-analysis involving 3,125 children found that approximately 60% were asymptomatic at presentation. Batteries at least 20 mm in diameter and batteries lodged in the esophagus were associated with greater complication risk. [2]
This is why absence of symptoms cannot safely exclude a dangerous esophageal battery.
Large lithium coin cells—particularly approximately 20 mm cells—have been strongly represented in severe pediatric injuries.
Their size makes esophageal lodgment more likely in small children, and their 3-volt output can produce rapid hydroxide generation.
However, a smaller battery should not automatically be considered harmless.
Serious injury can occur with different button-battery sizes depending on:
patient age;
anatomic location;
battery diameter;
duration of lodgment;
battery orientation;
underlying esophageal anatomy.
The important first question is therefore:
Where is the battery?

A child with an esophageal button battery may initially appear well.
Possible symptoms include:
coughing or choking;
noisy breathing;
wheezing or stridor;
drooling;
difficulty swallowing;
refusal to eat;
vomiting;
throat or chest discomfort;
abdominal pain;
gagging with food or fluids.
These symptoms are nonspecific and can resemble respiratory or gastrointestinal illness. [1]
Any unexplained acute swallowing or airway symptoms in a young child should therefore raise suspicion when access to a battery is possible.

Vomiting does not remove a lodged battery safely and may complicate the situation.
A child can initially be asymptomatic while substantial injury develops.
In the United States, call the National Battery Ingestion Hotline at 1-800-498-8666, use webPOISONCONTROL, or contact Poison Help at 1-800-222-1222 while proceeding for appropriate emergency evaluation. [3]
Current National Capital Poison Center guidance recommends immediate honey administration when:
a lithium coin cell may have been swallowed, or the battery type is unknown and is not clearly a small hearing-aid battery;
the child is 12 months of age or older;
ingestion occurred within the previous 12 hours;
the child is able to swallow;
honey is immediately available. [1]
Give:
10 mL — approximately 2 teaspoons — every 10 minutes for up to 6 doses while traveling to emergency care. [1]
Honey should never delay transport, imaging, endoscopy, or battery removal.
Do not give honey to infants younger than 12 months because of the risk of infant botulism.
The recommendation is based partly on experimental work showing that honey can reduce the alkaline tissue environment created by an esophageal lithium coin cell.
In a porcine model, honey and sucralfate reduced the rise in tissue pH and decreased the depth and extent of injury compared with saline. [4]
This evidence is preclinical—not a randomized human clinical trial.
But it is supported by mechanistic evidence and has been incorporated into National Capital Poison Center and ESPGHAN management recommendations. [1] [5]
Honey is therefore best understood as an injury-mitigation measure while definitive care is being arranged, not as treatment that makes removal less urgent.
Usually no.
Other than recommended honey in an eligible patient, National Capital Poison Center guidance advises keeping the patient NPO until an esophageal battery position is excluded by imaging. [1]
This corrects an important problem in the previous version of this article: blanket advice to avoid every oral substance omitted the current honey exception.
When button battery ingestion is suspected, prompt radiographic localization is critical.
For appropriate patients, radiographs should include the:
neck;
entire esophagus;
abdomen. [1]
A button battery can resemble a coin.
On an AP radiograph, a button battery may show a characteristic double-rim or halo sign.
On a lateral view, a step-off can sometimes help identify the battery and its orientation.
An ordinary coin does not produce the same electrochemical esophageal injury.
For the general management of objects that are truly non-toxic and non-battery foreign bodies, see Foreign Body Ingestion in Children: Poison Center Triage Guideline.
That pathway specifically excludes button and coin batteries because they require a different management strategy.
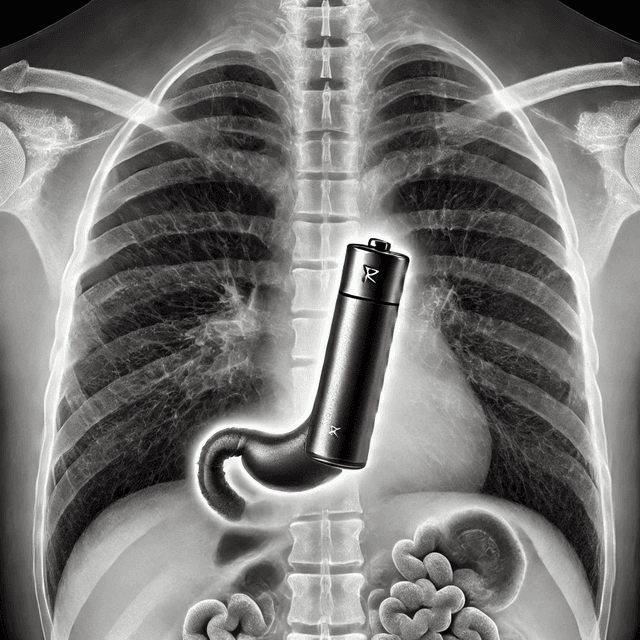
If the battery is lodged in the esophagus, it requires emergent endoscopic removal.
Serious injury can develop in approximately two hours. [1]
Do not delay removal because:
the child recently ate;
honey was administered;
sucralfate was administered;
the child currently appears well.
Endoscopy is preferred because it permits both removal and direct assessment of the surrounding esophageal injury.
Once imaging confirms an esophageal button battery, National Capital Poison Center guidance permits sucralfate suspension 1 g/10 mL, giving 10 mL orally every 10 minutes for up to three doses while awaiting endoscopic removal, if the clinical criteria are appropriate. [1]
Honey can be substituted in eligible children aged 12 months or older.
Neither honey nor sucralfate should be used when the battery may have been in the esophagus for more than 12 hours because perforation risk increases with delayed presentation.
Most importantly:
Neither intervention should delay removal.
Removal does not necessarily end the injury.
If no perforation is evident, current National Capital Poison Center guidance recommends considering irrigation of the injured esophageal area with 50–150 mL of sterile 0.25% acetic acid during endoscopy. [1]
The goal is to neutralize persistent alkaline tissue pH.
This approach is supported by experimental evidence showing effective pH neutralization without clinically significant thermal injury. [6]
This is a clinician-performed procedure.
It is not a home first-aid recommendation and vinegar should never be given to a child after suspected battery ingestion.
Button-battery tissue injury can continue after removal.
Potential complications include:
esophageal perforation;
tracheoesophageal fistula;
esophageal stricture;
recurrent laryngeal nerve injury;
vocal-cord paralysis;
mediastinitis;
aspiration pneumonia;
tracheal injury;
fistulization into a major blood vessel.
Rare vascular fistulas can cause catastrophic bleeding.
The Poison Center guideline emphasizes that some esophageal perforations and vascular fistulas develop days or weeks after battery removal. [1]
Therefore, follow-up depends on:
location of injury;
depth and severity;
battery orientation;
proximity to the airway and major vessels;
symptoms after removal.
A patient with significant esophageal injury should not be considered “cured” merely because the battery has been extracted.
Management differs once a button battery has clearly passed beyond the esophagus.
Many asymptomatic batteries in the stomach or intestine can pass spontaneously.
However, endoscopic retrieval may be appropriate when:
a magnet was also swallowed;
symptoms develop;
a large battery remains in the stomach beyond recommended observation periods;
there is concern that a large battery may previously have lodged in the esophagus;
imaging or history suggests significant injury. [1]
This is why individualized Poison Center or gastroenterology guidance is preferable to a blanket rule such as “all batteries must be removed” or “all batteries can be allowed to pass.”
AA and AAA batteries are cylindrical batteries, not button batteries.
They do not usually produce the same rapid electrochemical esophageal injury profile as a lodged lithium coin cell.
Their main risks include:
foreign-body obstruction;
prolonged gastric retention;
pressure injury;
casing damage;
leakage of alkaline contents;
caustic mucosal injury;
complications from multiple ingestions.
A 2025 pediatric study evaluated 45 children after cylindrical battery ingestion.
Fifteen had swallowed AA batteries and 30 had swallowed AAA batteries. Most batteries had reached the stomach or moved beyond it, and no intestinal perforations or surgical complications were reported. The authors concluded that conservative management is appropriate for many cases, while damaged batteries, multiple ingestions, prolonged gastric retention, symptoms, certain small cylindrical battery types, or previous abdominal surgery warrant more aggressive management. [7]
This evidence is far more informative than treating every AA or AAA ingestion as identical to a button-battery emergency.
A damaged cylindrical alkaline battery creates a different hazard.
Alkaline AA and AAA cells commonly contain potassium hydroxide or other alkaline electrolyte, not “battery acid.”
If the casing ruptures, the alkaline contents can cause caustic injury to:
lips;
mouth;
esophagus;
eyes;
skin.
A published pediatric case documented oropharyngeal and esophageal caustic injury after an infant ingested the internal contents of an AA battery. [8]
This should not be generalized into the claim that every intact swallowed AA or AAA battery causes chemical burns.
The casing condition matters.
Usually not.
The current Live version of this article repeatedly emphasizes “heavy metal poisoning” from batteries.
That framing is misleading for most acute whole-battery ingestions.
For button batteries, the dominant severe mechanism is local electrochemical and caustic tissue injury.
For intact cylindrical batteries, obstruction, retention, and leakage-related caustic injury are generally more clinically relevant than systemic metal poisoning.
National Capital Poison Center guidance specifically lists routine blood or urine testing for mercury or other battery ingredients and chelation among interventions that are unnecessary for typical button-battery ingestion. [1]
Systemic toxicity may become relevant in unusual circumstances involving extensively damaged cells or specific battery contents, but it should not be presented as the expected outcome of routine ingestion.
Button batteries do not have to be swallowed to cause serious tissue injury.
A battery lodged in the:
nose;
ear;
can cause rapid local tissue destruction.
Anyone who may have inserted a battery into the nose or ear should receive urgent medical evaluation.
Do not attempt repeated blind removal at home.
Prevention is particularly important because the highest-risk patients are often young children and the ingestion may be unwitnessed.
Reese's Law led to mandatory U.S. requirements for many consumer products containing button or coin batteries.
Current CPSC requirements include:
secured battery compartments;
resistance to battery liberation during use and abuse testing;
package warnings;
product warnings when practicable;
warning information in instructions;
child-resistant packaging requirements for many button or coin batteries. [9]
These regulations reduce access but do not eliminate risk.
CPSC continued to issue recalls in 2026 for products and battery packages that did not meet applicable child-access and warning requirements.
Parents and caregivers should:
keep spare button and coin batteries locked and out of sight;
discard or recycle used batteries promptly and safely;
check remote controls, key fobs, toys, scales, thermometers, lights, and other devices for secure battery compartments;
never leave loose batteries on counters or tables;
check floors and furniture after replacing a battery;
ensure visiting relatives also secure devices and spare batteries;
treat even a “dead” button battery as an ingestion hazard.
For broader household prevention measures, see How to Prevent Poisoning at Home: A Parent's Essential Safety Guide.
Button batteries and AA/AAA batteries are not the same emergency.
The mechanism and management depend on battery type and location.
Symptoms cannot rule out esophageal button-battery injury.
Many children are initially asymptomatic.
Honey is a specific exception to the NPO rule.
In an eligible child aged 12 months or older within 12 hours of suspected lithium coin-cell ingestion, honey should be started while traveling to emergency care.
Honey does not buy time for delay.
It mitigates injury; it does not stop it.
Do not call alkaline battery contents “battery acid.”
Common household alkaline cells contain alkaline electrolyte such as potassium hydroxide.
Do not overfocus on systemic heavy-metal poisoning.
Local electrochemical, caustic, obstruction, and retention injuries are usually more important.
The danger can continue after removal.
Delayed fistulas, bleeding, vocal-cord dysfunction, and strictures require risk-based follow-up.
Seek emergency evaluation immediately. Do not induce vomiting. If the child is at least 12 months old, can swallow, ingestion was within 12 hours, and a lithium coin cell may be involved, give 10 mL of honey every 10 minutes for up to six doses while traveling to emergency care. Do not delay transport or removal. [1]
No. A child with an esophageal button battery can initially appear well while severe injury develops.
No. Management depends on battery type, size, location, symptoms, and whether the battery is damaged or multiple batteries were swallowed. An esophageal button battery requires immediate removal; many batteries that have passed safely beyond the esophagus can be observed under appropriate guidance.
The person should receive medical assessment and radiographic localization, especially if the ingestion involves a child, more than one battery, a damaged battery, or symptoms. Many intact cylindrical batteries that move beyond the esophagus can pass spontaneously, but they should not simply be assumed harmless.
Usually not. Household alkaline batteries commonly contain alkaline material such as potassium hydroxide. It can cause chemical burns and should be rinsed promptly from skin or eyes, with Poison Center or medical guidance obtained for significant exposure.
Battery ingestion requires more precise thinking than the phrase “swallowed a battery” suggests.
A button battery lodged in the esophagus can cause severe alkaline injury within hours and requires immediate localization and removal.
In eligible children, honey can reduce injury while the child is being transported for definitive care—but it is never a substitute for emergency evaluation.
AA and AAA cylindrical batteries have a different risk profile. Many intact cells can pass once they reach the gastrointestinal tract, while damaged, multiple, symptomatic, or retained batteries require closer intervention.
The most important practical lessons are:
identify the battery, locate it quickly, treat esophageal button batteries as emergencies, use honey only under the correct criteria, and never let absence of symptoms create false reassurance.
© All copyright of this material is absolute to Medical toxicology
Dr. Omid Mehrpour (MD, FACMT) is a senior medical toxicologist and physician-scientist with over 15 years of clinical and academic experience in emergency medicine and toxicology. He founded Medical Toxicology LLC in Arizona and created several AI-powered tools designed to advance poisoning diagnosis, clinical decision-making, and public health education. Dr. Mehrpour has authored over 250 peer-reviewed publications and is ranked among the top 2% of scientists worldwide. He serves as an associate editor for several leading toxicology journals and holds multiple U.S. patents for AI-based diagnostic systems in toxicology. His work brings together cutting-edge research, digital innovation, and global health advocacy to transform the future of medical toxicology.
Keep reading
 Environmental and Occupational Toxicology

Amir Mohammad Mottaghi
 Environmental and Occupational Toxicology
Amir Mohammad Mottaghi
 Environmental and Occupational Toxicology
Omid Mehrpour
 Environmental and Occupational Toxicology
Omid Mehrpour