Public Health and Poison Prevention
Cortisol and Menopause: When to Suspect Cushing Syndrome
Omid Mehrpour
Post on 29 Jul 2025 · Updated 31 Oct 2026 · 13 min read

Omid Mehrpour
Post on 29 Jul 2025 · Updated 31 Oct 2026 · 13 min read
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/blogs/hidden-signs-of-cortisol-poisoning-during-menopause-what-do

Menopause can bring major changes in sleep, mood, body composition, concentration, menstrual patterns, and temperature regulation. Cortisol, the body's primary glucocorticoid stress hormone, also interacts with sleep, metabolism, circadian rhythms, and the hypothalamic-pituitary-adrenal (HPA) axis.
That overlap has helped popularize phrases such as “cortisol poisoning,” “cortisol overload,” and “cortisol belly.”
These phrases can be misleading.
“Cortisol poisoning” is not a standard medical diagnosis. Pathologic exposure to excessive cortisol is described clinically as hypercortisolism or, when it produces the characteristic clinical syndrome, Cushing syndrome. [1]
Menopause and perimenopause can produce symptoms such as sleep disturbance, mood changes, difficulty concentrating, weight change, and reduced sexual desire. These symptoms overlap with some features seen in Cushing syndrome, but the overlap does not mean that most menopausal symptoms are caused by excess cortisol. [2]
The clinically important question is therefore not:
“Do I have cortisol poisoning?”
It is:
“Are these symptoms consistent with the menopause transition, or are there progressive or unusual features that justify evaluation for true hypercortisolism?”
“Cortisol poisoning” is not a recognized clinical diagnosis.
Cortisol regulation may change during the menopausal transition, but this does not mean menopause routinely causes pathologic cortisol excess.
Weight gain, fatigue, poor sleep, anxiety, and concentration problems are too nonspecific to diagnose Cushing syndrome.
More specific Cushing clues include wide reddish-purple striae, easy bruising, proximal muscle weakness, facial plethora, progressive central fat redistribution, early osteoporosis, and clusters of progressive metabolic or cardiovascular abnormalities.
Long-term glucocorticoid medication exposure is the most common cause of Cushing syndrome.
Routine random blood cortisol testing is not recommended to screen for Cushing syndrome.
When testing is clinically indicated, validated options include late-night salivary cortisol, 24-hour urinary free cortisol, and dexamethasone suppression testing.
Menopause treatment should target evidence-based menopausal indications—not an assumed need to “detox cortisol.”
Cortisol is an essential steroid hormone produced by the adrenal cortex.
It helps regulate:
glucose metabolism;
blood pressure;
immune and inflammatory responses;
energy availability;
cardiovascular function;
adaptation to physiologic stress;
the sleep-wake cycle.
Cortisol is not inherently toxic.
Healthy cortisol secretion follows a circadian pattern. Levels are generally higher around waking and decline toward the evening and nighttime.
The HPA axis regulates this system through a feedback loop involving the hypothalamus, pituitary gland, adrenal glands, ACTH, and cortisol.
Temporary increases in cortisol are therefore a normal part of human physiology.
The problem is sustained pathologic glucocorticoid excess, not the mere presence of cortisol or a short-term stress response.
For a broader explanation of how chemicals can interfere with hormone signaling—an entirely different issue from normal endogenous cortisol physiology—see Endocrine-Disrupting Chemicals: How Everyday Exposures Affect Human Health.
The relationship is more complicated than “estrogen falls, so cortisol rises.”
Research has found associations between menopausal transition-related hormonal changes and cortisol regulation, but results vary across studies and measurement methods.
In the Seattle Midlife Women's Health Study, overnight cortisol measurements from 132 women were associated with estrone glucuronide, FSH, testosterone, epinephrine, and norepinephrine. Importantly, menopausal symptoms and perceived social stress did not simply track with cortisol levels, and menopausal stage itself did not provide a straightforward explanation for cortisol variation. [3]
Earlier longitudinal work from the same research program found that cortisol increased in some women around the late menopausal transition, but not consistently around every transition stage or the final menstrual period. [4]
Sleep also matters.
An experimental study found that sleep fragmentation increased bedtime cortisol and altered the cortisol awakening response. Estradiol suppression also affected aspects of cortisol physiology, although not in a pattern that supports the simple claim that lower estrogen automatically produces “cortisol toxicity.” [5]
The practical conclusion is:
Menopause can interact with stress physiology and the HPA axis, but cortisol changes during menopause are not equivalent to Cushing syndrome.
Many symptoms attributed online to “high cortisol” are common during midlife and have low diagnostic specificity.
These include:
fatigue;
sleep disturbance;
anxiety;
irritability;
difficulty concentrating;
memory complaints;
weight gain;
decreased libido;
menstrual irregularity.
ACOG specifically includes sleep changes, mood symptoms, concentration and memory changes, sexual-health changes, and weight gain among symptoms worth discussing during the menopause transition. [2]
None of these findings, by itself, establishes pathologic cortisol excess.
That is why symptom lists on social media are poor tools for diagnosing Cushing syndrome.
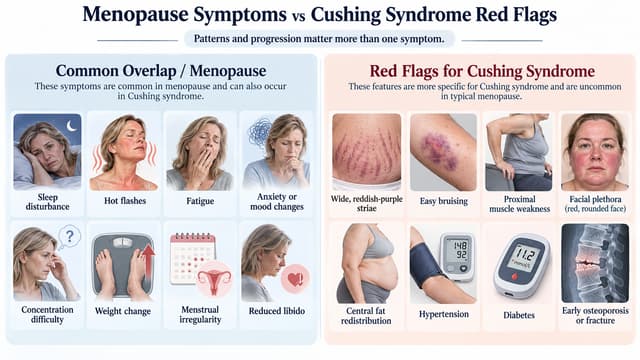
The most useful distinction is not whether a symptom can occur in both conditions.
It is whether a patient is developing multiple progressive features that are more discriminatory for Cushing syndrome.
Common or nonspecific finding | More concerning for Cushing syndrome |
|---|---|
Fatigue | Progressive proximal muscle weakness |
Poor sleep | Wide reddish-purple striae |
Anxiety or mood change | Easy or unexplained bruising |
Midlife weight gain | Rapid central weight gain with characteristic fat redistribution |
Concentration difficulty | Facial plethora |
Menstrual irregularity | Progressive combination of several Cushing features |
Reduced libido | Osteoporosis unusually early for age |
Generalized weakness | Hypertension or osteoporosis unusual for age, especially with other progressive Cushing features |
The Endocrine Society recommends considering Cushing testing particularly in patients with multiple and progressive features, especially those with higher discriminatory value, or unusual features for age such as premature osteoporosis or hypertension. [1]
Features that should increase clinical suspicion include:
easy bruising;
wide reddish-purple abdominal or axillary striae;
facial plethora;
proximal muscle weakness;
progressive central adiposity;
thin or fragile skin;
hypertension;
hyperglycemia or diabetes;
osteoporosis or fracture;
excess facial hair in women;
characteristic fat accumulation above the clavicles or upper back.
Cushing syndrome can also affect mood and cognition, so psychiatric or cognitive symptoms do not exclude it. [6]
The pattern and progression of findings matter more than any single symptom.
The most common cause of Cushing syndrome is not menopause.
It is exogenous glucocorticoid exposure. [1]
Examples include drugs such as:
prednisone;
prednisolone;
dexamethasone;
methylprednisolone;
hydrocortisone.
Clinicians should also review non-oral glucocorticoid exposure. Clinically significant systemic exposure can occur with injected, inhaled, topical, or intranasal corticosteroids, particularly with high-dose or prolonged use, repeated exposure, or drug interactions that increase glucocorticoid concentrations.
Relevant routes can include:
injections;
inhaled corticosteroids;
topical preparations;
nasal corticosteroids;
combinations of glucocorticoids administered through several routes.
Long-term high-dose glucocorticoid therapy is a well-established cause of exogenous Cushing syndrome. [6]
This medication history is especially important when a person develops progressive Cushingoid features.
No.
The Endocrine Society specifically recommends against widespread testing for Cushing syndrome in people without an appropriate clinical indication. [1]
This is important because many common symptoms of menopause overlap with symptoms seen in numerous other conditions.
Testing everyone with:
insomnia;
anxiety;
abdominal weight gain;
fatigue;
brain fog;
low libido;
would create a high risk of false-positive or difficult-to-interpret results.
Menopause itself is usually identified clinically from age, menstrual history, and symptoms rather than through broad hormone panels. The 2025 European Society of Endocrinology guideline states that biochemical testing for the diagnosis or management of (peri)menopause is generally unnecessary in women older than 45 years with a typical presentation; testing may be appropriate in younger women or when another diagnosis is being considered. [7]
The same principle applies to cortisol: test when the clinical question justifies the test, not because a nonspecific symptom appears on an online “high cortisol” checklist.
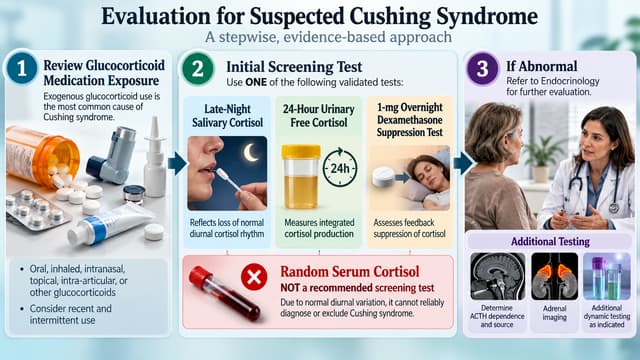
When clinical suspicion is appropriate, the Endocrine Society recommends validated initial tests such as: [1]
Normally, cortisol falls to a low level late at night.
Persistently elevated late-night salivary cortisol can therefore provide evidence that normal circadian cortisol suppression has been lost.
Testing generally requires more than one measurement.
A 24-hour urine collection estimates free cortisol production over an entire day.
Because cortisol secretion varies, repeated collections may be needed.
Dexamethasone should normally suppress endogenous cortisol production.
Failure to suppress appropriately may support further evaluation for hypercortisolism.
A random serum cortisol level is not recommended as a screening test for Cushing syndrome. [1]
This matters because a single cortisol value can be influenced by:
time of day;
acute illness;
sleep;
stress;
medication;
estrogen exposure;
laboratory methodology;
other physiologic factors.
An isolated “high cortisol” result therefore does not diagnose Cushing syndrome.
One abnormal screening result is not usually the end of the diagnostic process.
The Endocrine Society recommends further endocrine evaluation and usually a second appropriate test when an initial result is abnormal. [1]
Only after biochemical evidence of hypercortisolism is established should testing proceed toward determining the cause.
That distinction prevents unnecessary pituitary or adrenal imaging based only on vague symptoms or a single abnormal cortisol value.
No.
Cushing syndrome can cause characteristic central fat accumulation, but abdominal weight gain during midlife is extremely common and has many possible contributors.
These include:
aging;
changes in body composition;
reduced physical activity;
sleep disturbance;
diet;
metabolic disease;
menopause-related hormonal changes;
medication use.
Abdominal fat alone cannot distinguish menopause from Cushing syndrome.
The same caution applies to online claims that a specific body shape proves chronic cortisol excess.
“Adrenal fatigue” is not the same as adrenal insufficiency, Cushing syndrome, or validated HPA-axis disease.
Symptoms such as tiredness, poor sleep, and difficulty concentrating deserve appropriate evaluation, but assigning them automatically to “adrenal fatigue” or “cortisol imbalance” can obscure other causes.
Clinicians should instead evaluate the specific presentation and consider common alternatives such as:
menopause-related sleep disturbance;
depression or anxiety;
thyroid disease;
anemia;
sleep apnea;
medication effects;
metabolic disorders;
true endocrine disease when clinically indicated.
For someone without diagnosed hypercortisolism, the goal should not be to suppress cortisol as low as possible.
Cortisol is essential for normal physiology.
Healthy behaviors can improve general well-being during menopause, including:
maintaining regular sleep and wake times;
treating significant insomnia or sleep apnea;
regular physical activity;
resistance exercise for muscle and bone health;
balanced nutrition;
moderating alcohol;
smoking cessation;
addressing anxiety, depression, or chronic stress;
managing cardiovascular and metabolic risk.
These interventions should be framed as evidence-based health measures, not as a “cortisol detox.”
Supplements such as ashwagandha, rhodiola, holy basil, phosphatidylserine, magnesium, and other products are commonly marketed for “cortisol balance.”
They should not be presented as treatment for suspected Cushing syndrome.
A supplement may have limited evidence for stress or other outcomes without being proven to diagnose, prevent, or treat pathologic hypercortisolism.
Supplements can also cause adverse effects or interact with medications.
Most importantly, using supplements to self-treat suspected cortisol excess could delay investigation of a real endocrine disorder.
If Cushing syndrome is suspected, the appropriate next step is evidence-based endocrine testing—not a supplement regimen.
Menopausal hormone therapy is not prescribed primarily to “lower cortisol.”
Hormone therapy is an evidence-based option for appropriate patients with bothersome menopausal symptoms, particularly vasomotor symptoms and genitourinary syndrome of menopause. Treatment decisions depend on symptoms, age, time since menopause, medical history, contraindications, and individual benefit-risk assessment. [8]
A person should therefore not begin estrogen or progesterone simply because an online test or symptom list suggests “high cortisol.”
Menopausal symptoms and Cushing syndrome are different clinical questions.
If excessive glucocorticoid treatment is contributing to Cushingoid features, the solution is not necessarily abrupt discontinuation.
Long-term glucocorticoids can suppress the HPA axis.
The 2024 joint European Society of Endocrinology/Endocrine Society guideline emphasizes supervised tapering when long-term glucocorticoids are no longer required, because abrupt withdrawal after prolonged exposure may precipitate glucocorticoid withdrawal or adrenal insufficiency. [9]
Never stop long-term prednisone, dexamethasone, or another systemic glucocorticoid abruptly without discussing the plan with the prescribing clinician.
Consider discussing Cushing syndrome with a healthcare professional when symptoms are progressive, unusual, or clustered, particularly if several of the following occur together:
wide purple or reddish striae;
easy bruising;
progressive proximal muscle weakness;
facial plethora;
rapid central weight gain with characteristic fat redistribution;
difficult-to-control hypertension;
new or worsening diabetes;
osteoporosis or fractures earlier than expected;
significant glucocorticoid exposure;
multiple features that continue to progress.
Testing should be guided by the clinical pattern rather than fear generated by nonspecific symptom lists.
Symptoms are more likely to fit the menopause transition when they occur in the expected midlife context together with patterns such as:
changing menstrual cycles;
hot flashes;
night sweats;
sleep disruption;
vaginal dryness;
urinary or pelvic-floor changes;
changes in sexual function;
mood symptoms;
concentration or memory complaints.
These symptoms can still deserve treatment.
They simply do not automatically indicate cortisol excess.
“Cortisol poisoning” is not a diagnosis.
Use the terms hypercortisolism or Cushing syndrome when true pathologic cortisol excess is being considered.
Common symptoms have low specificity.
Fatigue, abdominal weight gain, anxiety, insomnia, and brain fog alone are not enough to justify a Cushing diagnosis.
Look for progressive discriminatory features.
Wide purple striae, easy bruising, proximal weakness, facial plethora, unusual osteoporosis, and clusters of progressive metabolic or cardiovascular abnormalities increase suspicion.
Medication history comes first.
Exogenous glucocorticoids are the most common cause of Cushing syndrome.
Do not screen with random cortisol.
Validated testing should be chosen according to clinical context.
Do not treat an unproven cortisol problem.
The Endocrine Society recommends against cortisol-lowering treatment when Cushing syndrome has not been established. [10]
No. “Cortisol poisoning” is not a standard diagnostic term. Pathologic excess cortisol is evaluated as hypercortisolism or Cushing syndrome.
No. Menopause can influence HPA-axis physiology, sleep, and stress responses, and some studies have observed cortisol changes during parts of the menopausal transition. These findings do not mean that menopause routinely causes pathologic cortisol excess.
Progressive proximal muscle weakness, wide reddish-purple striae, easy bruising, facial plethora, characteristic central fat redistribution, osteoporosis unusually early for age, and multiple progressive Cushing features are more informative than fatigue or weight gain alone.
Not routinely. Cushing testing is recommended when the clinical pattern raises meaningful suspicion. Random serum cortisol is not an appropriate screening test.
Some supplements are marketed for stress or “cortisol balance,” but they are not established treatments for Cushing syndrome and should not replace appropriate medical evaluation.
Cortisol and menopause interact through complex endocrine, sleep, and stress pathways, but this relationship is often oversimplified online.
Menopause can produce fatigue, poor sleep, mood changes, weight change, concentration problems, and menstrual irregularity. Those symptoms overlap with Cushing syndrome, but they do not prove pathologic cortisol excess.
The evidence-based approach is to distinguish common menopausal symptoms from progressive, more discriminatory signs of Cushing syndrome, review glucocorticoid medication exposure, and use validated endocrine testing only when clinically justified.
The goal is not to “detox cortisol.”
It is to identify the actual cause of symptoms and treat the right condition.
© All copyright of this material is absolute to Medical toxicology
Dr. Omid Mehrpour (MD, FACMT) is a senior medical toxicologist and physician-scientist with over 15 years of clinical and academic experience in emergency medicine and toxicology. He founded Medical Toxicology LLC in Arizona and created several AI-powered tools designed to advance poisoning diagnosis, clinical decision-making, and public health education. Dr. Mehrpour has authored over 250 peer-reviewed publications and is ranked among the top 2% of scientists worldwide. He serves as an associate editor for several leading toxicology journals and holds multiple U.S. patents for AI-based diagnostic systems in toxicology. His work brings together cutting-edge research, digital innovation, and global health advocacy to transform the future of medical toxicology.
Keep reading
 Public Health and Poison Prevention
Omid Mehrpour
 Public Health and Poison Prevention

Sherika Whitelocke
 Public Health and Poison Prevention
Omid Mehrpour
 Public Health and Poison Prevention
Omid Mehrpour