Food and Drug Toxicology
Ciguatera Fish Poisoning: Causes, Symptoms, and Treatment Guide
Omid Mehrpour
Post on 19 Feb 2025 · Updated 20 Oct 2026 · 15 min read

Omid Mehrpour
Post on 19 Feb 2025 · Updated 20 Oct 2026 · 15 min read
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/blogs/ciguatera-fish-poisoning-causes-symptoms-and-treatment-gu
Ciguatera fish poisoning (CFP) is a foodborne toxic syndrome caused by eating fish containing ciguatoxins. These heat-stable marine toxins originate from toxin-producing benthic dinoflagellates associated with coral and rocky reef ecosystems, particularly species within Gambierdiscus and Fukuyoa. Toxins enter marine food webs, can be transformed and concentrated as they move through trophic levels, and ultimately reach humans through contaminated fish. [1]
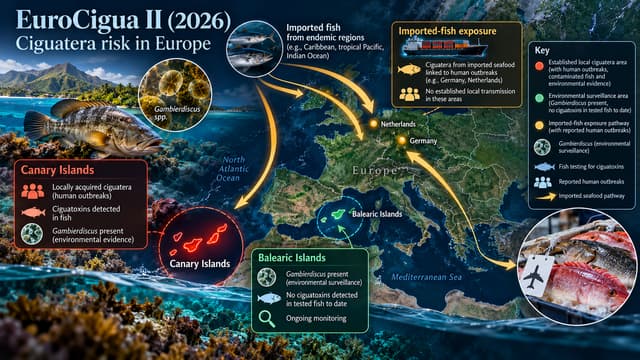
Ciguatera remains best known from tropical and subtropical regions of the Pacific, Indian Ocean, and Caribbean. But geography alone is becoming a less reliable diagnostic filter. International seafood trade can transport contaminated fish into non-endemic countries, while locally acquired European ciguatera has been documented in Macaronesia, particularly the Canary Islands.
The EuroCigua II scientific package published on October 14, 2026 substantially improves the evidence base for Europe. It integrates epidemiologic surveillance, fish and microalgal monitoring, analytical chemistry, and predictive modelling. The findings support a regional and heterogeneous European risk picture, not a simple claim that ciguatera incidence is uniformly increasing across Europe. [2]
Ciguatoxins are heat-stable; cooking, freezing, canning, salting, or smoking does not reliably make contaminated fish safe. [1]
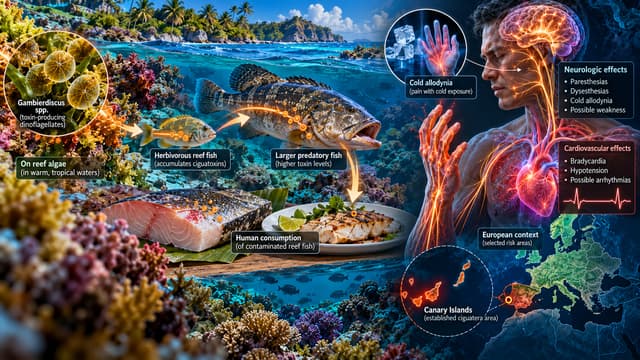
Typical illness combines gastrointestinal symptoms with neurologic findings such as paresthesias and cold allodynia; bradycardia and hypotension can occur in more severe cases.
There is no routinely available clinical blood test that confirms ciguatera in a patient; diagnosis is primarily clinical and epidemiologic.
Europe has two distinct exposure pathways: locally acquired ciguatera from fish harvested in European waters and ciguatera caused by imported fish.
EuroCigua II identified the Canary Islands as the European area with the most consistent combined epidemiologic, environmental, and fish-toxin evidence. [2]
Persistent Gambierdiscus populations have been demonstrated in the Balearic Islands, but environmental detection does not by itself prove contaminated fish or human ciguatera incidence.
EuroCigua II modelling suggests climate-related changes may reshape when and where risk occurs; it does not establish a uniform Europe-wide rise in clinical disease.
No specific antidote exists. Treatment remains supportive and symptom-directed.
IV mannitol remains controversial: uncontrolled reports suggested benefit, but the only double-blind randomized trial did not demonstrate superiority over normal saline. [10]
Surveillance and laboratory capability have improved, but gaps remain in case ascertainment, reference materials, method harmonization, and dose-response information.
Ciguatera begins with toxin-producing marine dinoflagellates living on macroalgae, coral, and other substrates.
Herbivorous and omnivorous fish consume material carrying these organisms or their toxins. Predatory fish then consume smaller fish, allowing ciguatoxins to move through the marine food web.
Large reef predators have historically been associated with many human cases, including:
barracuda;
grouper;
snapper;
amberjack and other jacks;
moray eel.
However, size and trophic position are risk indicators rather than guarantees. Herbivorous and omnivorous fish can also contain ciguatoxins, and EuroCigua II found toxin occurrence across multiple fish species and trophic levels in the Canary Islands. [2]
Ciguatoxins interfere with voltage-gated sodium-channel function in excitable tissues, helping explain the characteristic combination of sensory disturbances, autonomic effects, and cardiovascular abnormalities.
Another foodborne poisoning syndrome involving abnormal sodium-channel activity is discussed in Mad Honey Poisoning: Grayanotoxin, Bradycardia, Hypotension, and Treatment, although grayanotoxins and ciguatoxins are distinct toxins with different exposure pathways and clinical patterns.
Ciguatera remains predominantly associated with tropical and subtropical reef environments. The Caribbean, Pacific Islands, and Indian Ocean remain major endemic regions, and cases also occur in areas including Florida, Hawaii, and other island or coastal settings. [1]
However, three different mechanisms can place a ciguatera patient in a region traditionally considered non-endemic:
Exposure pathway | Meaning |
|---|---|
Local or autochthonous exposure | The implicated fish was harvested from local waters |
Imported-fish exposure | The fish was harvested outside the region or EU/EEA and imported |
Travel-associated exposure | The patient consumed contaminated fish while visiting an endemic area and became ill during or after travel |
These pathways should not be conflated. A case diagnosed in Germany, for example, does not necessarily mean German coastal waters have developed a local ciguatera ecology.
The EuroCigua II surveillance protocol was specifically designed to improve harmonized characterization of these epidemiologic patterns rather than treating all European cases as equivalent. [4]
EuroCigua II was the follow-up to the original European ciguatera project. Conducted from 2022 through 2026, it combined epidemiology, environmental surveillance, fish testing, laboratory-method development, toxin characterization, and predictive modelling to improve future European risk assessment. [2]
Importantly, the resulting papers are external scientific reports published through EFSA Supporting Publications. They are not a new EU clinical-treatment guideline and do not themselves create new regulatory limits. The reports explicitly state that they cannot be considered outputs formally adopted by EFSA. [2]
EuroCigua II collected 10 outbreaks involving 40 cases from 2020 through 2025.
Eight outbreaks involving 32 cases were classified as autochthonous, while two imported-fish outbreaks involved eight cases. The overall recorded EU incidence was very low; within the Canary Islands, the reported incidence for 2020–2025 was 0.24 cases per 100,000 population—lower than the corresponding rate reported during the earlier EuroCigua period. [3]
These numbers need careful interpretation.
They represent cases and outbreaks captured through the EuroCigua II surveillance framework. Ciguatera recognition and reporting remain incomplete, and the investigators themselves identify underdiagnosis and surveillance gaps.
Therefore:
10 outbreaks and 40 cases are not the total number of European ciguatera illnesses during that period.
Likewise, the dataset does not support a claim that clinical incidence is uniformly increasing across Europe.
The Canary Islands remain the clearest European setting for locally acquired ciguatera.
All eight autochthonous outbreaks collected during EuroCigua II were reported from Spain, with most linked to recreationally caught fish from the Canary Islands. Implicated genera included Seriola, Sphyraena, Epinephelus, and Pomatomus. [3]
The environmental and fish evidence points in the same direction.
EuroCigua II found CTX-like toxicity across multiple fish species and trophic levels in the Canary Islands, while long-running official control records reinforce the region's status as an established European ciguatera risk area. [7]
That convergence matters:
human outbreaks + ciguatoxin-positive fish + toxin-producing microalgae = much stronger evidence of an established exposure pathway than any one of those findings alone.
Europe can also experience ciguatera without local toxin production.
The two imported EuroCigua II outbreaks occurred after consumption of fish imported from India. The implicated species was Lutjanus bohar, and cases were reported in the Netherlands and Germany despite distribution of the fish to several countries. [3]
A separate EuroCigua II project specifically investigated ciguatoxins in imported fish using a risk-based sampling strategy. [5]
Targeted imported-fish samples tested during that surveillance work did not demonstrate detectable CTX contamination under the applied sampling and analytical conditions. That is reassuring for the sampled products, but it does not prove that imported seafood poses no ciguatera risk.
The documented German and Dutch outbreaks themselves demonstrate why.
A risk-based sample is a snapshot of selected products; an outbreak is evidence that contaminated imported fish can reach consumers.
The Mediterranean findings require even more careful interpretation.
EuroCigua II documented well-established and persistent Gambierdiscus populations in the Balearic Islands. Environmental monitoring therefore demonstrates ecological suitability and the presence of potentially toxigenic organisms. [6]
But fish testing produced a different layer of evidence.
In contrast with the Canary Islands, EuroCigua II reported no ciguatoxins detected in the tested Balearic fish to date, despite the presence of potentially toxigenic microalgae. [2]
That distinction is crucial.
Finding Gambierdiscus in Mediterranean waters does not automatically establish:
toxin accumulation in local edible fish;
human exposure;
a ciguatera outbreak;
increasing clinical incidence.
Instead, it identifies an environmental signal worth monitoring.
The earlier version of this Blog stated broadly that climate change, coral degradation, and rising ocean temperatures were increasing the geographic spread of ciguatera and “leading to more cases.”
That wording is too simple.
Temperature, nutrients, habitat conditions, coastal disturbance, and other environmental variables can influence Gambierdiscus ecology. But the path from environmental suitability to human illness involves several additional steps:
toxin-producing microalgae → toxin production → food-web transfer → contaminated edible fish → human consumption → recognition and reporting of disease.
EuroCigua II modelling confirms that ciguatera risk is region-specific, environmentally driven, and temporally lagged. In the Canary Islands, models identified an approximate lag between environmental conditions and subsequent CTX occurrence in fish. In the Balearics, Gambierdiscus abundance showed marked seasonality that could potentially inform targeted monitoring. [8]
Most importantly, the modelling report concludes that ocean warming is more likely to reshape the temporal and spatial distribution of risk than increase it uniformly. Responses also differ by region because nutrient regimes and local ecology matter. [8]
So the scientifically appropriate conclusion is:
Climate and environmental change may alter future ciguatera hazard and exposure pathways, but environmental modelling is not evidence of a uniform increase in confirmed European human incidence.
EuroCigua II also substantially expanded European laboratory capability.
Approaches used across the project included cell-based bioassays and mass-spectrometric methods such as LC-MS/MS and high-resolution mass spectrometry. Reference-material development and interlaboratory capacity building were major components of the project. [9]
Yet analytical limitations remain substantial.
The final report identifies:
limited availability of reference standards;
need for greater laboratory harmonization;
very low toxin concentrations in some environmental matrices;
incomplete toxicological and dose-response data;
insufficient quantities of outbreak-linked fish for quantitative analysis;
absence of legally established maximum CTX levels. [2]
The European surveillance protocol likewise notes that specialized analytical methods can detect or characterize ciguatoxins in fish, but laboratory testing should not be confused with a routine clinical test for patients. [4]
Travel to the Caribbean or Pacific is no longer required before ciguatera enters the differential diagnosis.
Clinicians should consider CFP when a compatible syndrome follows consumption of:
reef-associated fish from a traditional endemic region;
fish harvested from a recognized European risk area such as the Canary Islands;
imported fish of uncertain origin;
a shared fish meal followed by similar illness in several diners.
At the same time, a patient becoming ill in mainland Europe does not establish local European marine transmission.
The fish's harvest origin can be as important as the patient's location.
Symptoms most often begin within hours of eating contaminated fish, although onset can be delayed.
Early gastrointestinal illness commonly includes nausea, vomiting, diarrhea, and abdominal pain. CDC's 2026 Yellow Book describes gastrointestinal symptoms as typically appearing within approximately 1–6 hours, although later presentations occur. [1]
Neurologic manifestations are particularly characteristic and can outlast gastrointestinal symptoms.
They include paresthesias, numbness, burning sensations, itching, weakness, myalgia, dizziness, ataxia, metallic or unusual taste, fatigue, and sensory disturbances.
Cold allodynia—pain or abnormal burning sensation triggered by cold—is among the most clinically distinctive findings. Patients may also describe apparent hot-cold sensory reversal.
Symptoms can persist for weeks and, in some patients, much longer. [1]
More severe poisoning can involve:
bradycardia;
hypotension;
heart block;
other rhythm abnormalities.
Death is uncommon; CDC estimates a mortality rate below 0.1%, although outcome depends on toxin dose and access to supportive medical care. [1]
Ciguatera is primarily a clinical diagnosis.
The most useful clues are:
compatible gastrointestinal and neurologic symptoms;
recent consumption of potentially ciguatoxic marine fish;
cold allodynia or another characteristic sensory syndrome;
similar illness among people who shared the meal;
epidemiologic information about the fish species and harvest origin.
There is currently no routine clinical diagnostic test for ciguatoxin in human blood or urine. [1]
Remaining fish can sometimes be tested in specialized laboratories, particularly during outbreak investigation. Techniques may include functional assays and mass-spectrometric toxin characterization, but these are specialized public-health or research methods—not consumer bedside tests.
The old FAQ statement that a commercial kit provides a practical way to determine whether fish is safe has therefore been removed.
There is no specific antidote.
Management is primarily supportive and guided by the patient's symptoms and physiology. [1]
Patients with significant vomiting or diarrhea may require IV fluids and electrolyte replacement. Symptomatic hypotension should be treated according to hemodynamic status, while clinically important bradycardia may require atropine and appropriate cardiac monitoring.
Persistent neuropathic symptoms can be difficult to manage. Medications used for neuropathic syndromes—including gabapentin, pregabalin, or amitriptyline—have been reported to provide symptom relief in selected patients, but evidence for these treatments is limited.
Mannitol has a long history in ciguatera treatment, but the evidence is mixed.
Early uncontrolled reports and case series described rapid improvement in neurologic symptoms. A later evidence review concluded that mannitol can reasonably be considered in acute CFP but emphasized that overall human evidence is low quality. [10]
The key randomized evidence is less reassuring.
A double-blind randomized trial comparing mannitol with normal saline found no significant superiority of mannitol and reported more infusion-related discomfort in the mannitol group. [11]
Current CDC guidance still notes that mannitol may be considered relatively early in the course of illness, but only in hemodynamically stable, adequately hydrated patients, while acknowledging variable evidence. [1]
Accordingly, mannitol should not be described as a proven first-line antidote or a therapy known to shorten recovery.
Gastrointestinal symptoms generally resolve before neurologic symptoms.
Paresthesias, fatigue, pruritus, sensory abnormalities, and other neurologic complaints may persist or recur for weeks to months, and occasionally longer.
CDC travel-medicine guidance advises patients recovering from ciguatera to avoid alcohol, caffeine, fish, and nuts for an extended period because these have been reported to provoke symptom recurrence in some patients. [1]
This advice is based on recurrence observations rather than proof that each trigger affects every patient.
Prevention remains more reliable than treatment.
Ciguatoxins do not change a fish's smell, taste, or appearance and are not reliably destroyed by cooking, freezing, smoking, salting, pickling, or canning. [1]
Risk can be reduced by avoiding fish known to be high risk in endemic locations and avoiding organs in which toxins may be concentrated, including the liver, intestines, roe, and head.
Fish size can provide some risk information because bioaccumulation can increase with trophic exposure, but “choose a smaller fish” is not a guarantee of safety. EuroCigua II documented an outbreak in the Canary Islands that contributed to revision of a control-program weight threshold, illustrating why species, location, and local surveillance matter in addition to size. [3]
International seafood trade also means prevention cannot rely solely on knowing where the meal is eaten.
For another unusual marine foodborne poisoning syndrome with a different and incompletely defined toxicology, see Deadly Delicacy: The Hidden Danger of Eating Sea Turtles.
Do not make geography a binary rule. Ciguatera remains predominantly tropical and subtropical, but locally acquired Canary Islands cases and imported-fish outbreaks show why European presentation does not exclude it.
Ask where the fish was caught—not only where it was eaten.
Environmental detection is not clinical incidence. Finding Gambierdiscus demonstrates ecological hazard, not necessarily contaminated fish or human disease.
Cold allodynia remains a valuable diagnostic clue. It is highly characteristic when present, although it is not universal.
Cooking does not detoxify ciguatoxin.
No routine human ciguatoxin test exists. Specialized fish testing belongs primarily to public-health, regulatory, or research settings.
Mannitol is not a proven antidote. Evidence remains inconsistent and includes a negative randomized trial.
Climate modelling describes changing potential risk—not a count of future patients.

Yes. Locally acquired outbreaks are well established in the Canary Islands, and earlier events have also occurred in Macaronesia. Europe also receives cases through imported contaminated fish and travel. EuroCigua II identified the Canary Islands as the European region with the most consistent combined epidemiologic and environmental evidence. [2]
Not necessarily. Persistent Gambierdiscus populations have been documented in the Balearic Islands, but EuroCigua II reported no CTXs in the tested Balearic fish to date. Environmental presence identifies potential hazard and surveillance need; it does not establish local human incidence. [2]
No. Ciguatoxins are heat-stable and are not reliably destroyed by cooking, freezing, canning, smoking, salting, or pickling. [1]
No consumer method should be relied upon to prove that a fish is safe. Specialized laboratory methods can detect or characterize CTXs in fish, but important analytical and reference-standard limitations remain. [9]
No. There is no established antidote for ciguatera. Mannitol has been used for acute neurologic symptoms, but evidence is inconsistent and a randomized controlled trial did not show superiority over normal saline. [10]
Ciguatera remains a classic marine-toxin syndrome, but the epidemiology is more complex than a simple map of tropical hotspots.
The 2026 EuroCigua II reports strengthen evidence for an established local exposure pathway in the Canary Islands, demonstrate the continuing relevance of imported-fish outbreaks, document persistent potentially toxigenic Gambierdiscus populations in parts of the western Mediterranean, and improve European analytical and modelling capacity. At the same time, the project highlights major uncertainties in surveillance, toxin quantification, analytical standardization, dose-response assessment, and Europe-wide risk estimation. [2]
The distinction between documented disease, environmental hazard, contaminated fish, and modelled future risk is essential. None of these should automatically be used as a proxy for another.
For clinicians, the practical lesson is straightforward: consider ciguatera after a compatible gastrointestinal-neurologic syndrome even outside traditional tropical settings, ask about the fish species and harvest origin, recognize cold allodynia and cardiovascular toxicity, and provide supportive care while involving poison-control or public-health authorities when an outbreak or contaminated food product is suspected.
© All copyright of this material is absolute to Medical toxicology
Dr. Omid Mehrpour (MD, FACMT) is a senior medical toxicologist and physician-scientist with over 15 years of clinical and academic experience in emergency medicine and toxicology. He founded Medical Toxicology LLC in Arizona and created several AI-powered tools designed to advance poisoning diagnosis, clinical decision-making, and public health education. Dr. Mehrpour has authored over 250 peer-reviewed publications and is ranked among the top 2% of scientists worldwide. He serves as an associate editor for several leading toxicology journals and holds multiple U.S. patents for AI-based diagnostic systems in toxicology. His work brings together cutting-edge research, digital innovation, and global health advocacy to transform the future of medical toxicology.
Keep reading
 Food and Drug Toxicology

Amir Mohammad Mottaghi
 Food and Drug Toxicology

Amirhosein Shabrang
 Food and Drug Toxicology
Amirhosein Shabrang
 Food and Drug Toxicology
Amirhosein Shabrang