Food and Drug Toxicology
Can You Overdose on Vitamin D? Symptoms and Treatment
Omid Mehrpour
Post on 08 Aug 2024 · Updated 12 Nov 2026 · 15 min read

Omid Mehrpour
Post on 08 Aug 2024 · Updated 12 Nov 2026 · 15 min read
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/blogs/can-you-overdose-on-vitamin-d-2

Vitamin D is essential for calcium regulation and bone health. But because it is fat-soluble and can accumulate after excessive intake, taking too much vitamin D can cause serious health problems.
Yes, vitamin D overdose is possible.
Most clinically important cases involve excessive supplements, concentrated preparations, dosing mistakes, or products containing more vitamin D than expected—not ordinary food intake or normal sunlight exposure.
The central danger is hypercalcemia, a condition in which blood calcium becomes abnormally high. Severe hypercalcemia can cause dehydration, confusion, kidney injury, abnormal heart rhythms, and potentially life-threatening complications. [1]
However, a high vitamin D blood-test result is not automatically the same as clinical poisoning.
A 2026 study examining 185,604 vitamin D test results found that marked elevations in 25-hydroxyvitamin D did not always coincide with hypercalcemia. [2]
The important question is therefore not simply “How much vitamin D did someone take?” but also:
“How long was it taken, what formulation was involved, and has it caused clinically significant calcium disturbance?”
Excess vitamin D can cause toxicity, usually through high blood calcium.
Serious poisoning is generally associated with excessive or repeated high-dose exposure, although unusual product errors and other exposures can also cause illness.
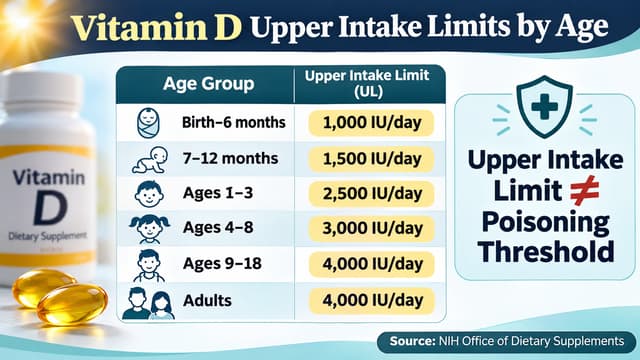
The adult tolerable upper intake level is 4,000 IU (100 micrograms) daily, but this is not a threshold that automatically diagnoses poisoning.
Upper intake limits are lower for infants and younger children.
Vitamin D toxicity is typically associated with serum 25(OH)D concentrations above approximately 150 ng/mL (375 nmol/L), but laboratory results must be interpreted alongside calcium and clinical findings.
Symptoms can include nausea, vomiting, constipation, increased thirst, frequent urination, weakness, dehydration, and confusion.
Severe cases may involve acute kidney injury, nephrocalcinosis, arrhythmias, or other complications of hypercalcemia.
Taking a prescribed high-dose preparation on the wrong schedule is an important preventable cause.
Treatment focuses on stopping excessive exposure and managing hypercalcemia under medical supervision.
Routine vitamin D testing is not recommended for every healthy person, but testing is important when toxicity is suspected.
Vitamin D toxicity, or hypervitaminosis D, occurs when excessive vitamin D activity causes harmful biochemical or clinical effects.
Vitamin D has two common nutritional forms:
Vitamin D2 (ergocalciferol)
Vitamin D3 (cholecalciferol)
Both can raise vitamin D status. Vitamin D3 often raises or maintains circulating 25(OH)D more effectively in comparative studies, but both forms have legitimate medical and nutritional uses. [1]
After absorption, vitamin D undergoes metabolic activation in the liver and kidneys.
The liver produces 25-hydroxyvitamin D [25(OH)D], the principal laboratory marker of vitamin D status.
The kidneys and some other tissues convert vitamin D metabolites into 1,25-dihydroxyvitamin D [1,25(OH)2D], also called calcitriol.
Vitamin D increases intestinal calcium absorption and participates in calcium and phosphate regulation.
When excessive vitamin D exposure disrupts this balance, calcium levels can rise enough to damage the kidneys and other organs.
Most clinically important symptoms are consequences of hypercalcemia.
Symptoms may include:
nausea;
vomiting;
loss of appetite;
constipation;
abdominal discomfort;
increased thirst;
frequent urination;
fatigue;
muscle weakness;
dehydration.
These findings can be nonspecific.
A person may initially assume that nausea, fatigue or increased urination is caused by an infection, a gastrointestinal illness or another medication.
Marked hypercalcemia can produce:
substantial dehydration;
confusion or altered mental status;
severe weakness;
acute kidney injury;
calcium deposition in the kidneys;
cardiac electrical abnormalities;
rarely, life-threatening arrhythmias or coma.
The severity depends on calcium concentration, duration of exposure, underlying disease and the patient's physiologic condition. [3]
Vitamin D overdose should not be diagnosed from a long list of nonspecific symptoms alone.
Laboratory evaluation is essential when clinically significant toxicity is suspected.
The answer depends on age, total intake, duration, formulation and medical circumstances.
A crucial distinction is between:
Recommended intake: the amount generally needed to meet nutritional requirements;
Tolerable Upper Intake Level (UL): a long-term intake unlikely to produce adverse effects in most healthy people;
Toxic exposure: an amount and duration that actually produce, or present substantial risk of, clinically important harm.
These are not interchangeable.
The following U.S. tolerable upper intake levels are published by the National Institutes of Health Office of Dietary Supplements. [1]
Age | Upper daily limit |
|---|---|
Birth–6 months | 1,000 IU (25 mcg) |
7–12 months | 1,500 IU (approximately 38 mcg) |
1–3 years | 2,500 IU (approximately 63 mcg) |
4–8 years | 3,000 IU (75 mcg) |
9–18 years | 4,000 IU (100 mcg) |
Adults 19+ | 4,000 IU (100 mcg) |
Pregnancy and lactation | 4,000 IU (100 mcg) |
Important: These limits apply to usual long-term intake in the general population. They do not mean that exceeding a limit once causes poisoning, nor do they replace individualized treatment prescribed for a diagnosed medical condition.
For dose conversion:
1 microgram of vitamin D = 40 IU.
Therefore, 100 micrograms is equivalent to 4,000 IU.
Read the actual label unit carefully. Confusing milligrams, micrograms, international units, drops and milliliters can produce serious dosing errors.
A high-dose vitamin D preparation may be prescribed for specific clinical indications.
For example, a clinician may prescribe a 50,000 IU capsule on a weekly schedule for a limited treatment period.
The number 50,000 IU alone does not establish poisoning.
The relevant question is whether the preparation is taken according to the prescribed schedule and whether appropriate follow-up is arranged.
Taking a product intended for weekly use every day by mistake is a different exposure.
Repeated dosing errors can produce a large cumulative vitamin D intake and increase the risk of toxicity.
The same problem can occur when a person combines:
a prescription vitamin D product;
a multivitamin;
vitamin D gummies;
concentrated drops;
calcium and vitamin D combination products.
Total intake across all products matters.
Prolonged intake of excessive vitamin D is a common mechanism of toxicity.
Because vitamin D is fat-soluble, the consequences of repeated overuse may develop gradually rather than immediately after a single dose.
Infants are particularly vulnerable when caregivers confuse different liquid concentrations or use an adult-strength supplement.
On August 7, 2026, the German Federal Institute for Risk Assessment (BfR) warned after another serious infant vitamin D poisoning case in Germany.
The reported exposure involved a high-dose food supplement intended for adults that had been purchased online and given instead of an appropriate infant preparation. [4]
This was an official safety communication about a documented exposure.
It does not mean that properly administered infant vitamin D supplementation is generally unsafe.
The preventable problem was use of the wrong preparation or concentration.
Label accuracy and manufacturing quality can also matter.
A 2025 Japanese pediatric case report described a seven-year-old boy who developed significant hypercalcemia and a serum 25(OH)D concentration of 727 ng/mL after prolonged use of vitamin D-containing supplements.
Subsequent third-party testing found substantial discrepancies between declared and actual vitamin D contents, with some capsules containing more than 12 times the stated amount. [5]
This is a direct, product-specific case report—not evidence that all supplements have such manufacturing problems.
It illustrates why product quality and accurate labeling matter as much as the intended dose.
Food-related vitamin D poisoning is rare, but it can occur.
A 2025 case series described three adults from the same household who developed severe hypercalcemia and acute kidney injury after consuming contaminated cooking oil.
Laboratory analysis of the retained oil confirmed markedly excessive vitamin D3 content. One patient required dialysis. [6]
This outbreak is an exception to the usual pattern of supplement-related toxicity.
It should not be generalized to ordinary fortified foods.
The main test used to assess vitamin D status is serum 25-hydroxyvitamin D [25(OH)D].
Results may be reported in:
ng/mL;
nmol/L.
The conversion is:
1 ng/mL = 2.5 nmol/L.
A 25(OH)D concentration of at least 20 ng/mL is generally considered adequate for most healthy individuals under the U.S. National Academies framework, although universal optimal targets have not been established.
Concentrations above approximately 50–60 ng/mL may raise concern about unnecessary excess exposure, but they do not by themselves diagnose toxicity.
A level above 100 ng/mL is markedly elevated and warrants assessment of supplementation and clinical context.
Clinically important vitamin D intoxication is commonly associated with concentrations above approximately 150 ng/mL, especially when accompanied by hypercalcemia and suppressed parathyroid hormone. [1]
These values are interpretive guides, not absolute diagnostic boundaries.
A 2026 retrospective study at a tertiary hospital in Barcelona analyzed 185,604 adult 25(OH)D test results collected during 2020–2025.
Of those results, 393 were above 100 ng/mL.
Calcium measurements were available for 324 of the elevated results, and 14 of 324 (4.3%) were accompanied by albumin-adjusted hypercalcemia. [2]
This shows that a high vitamin D result does not invariably mean hypercalcemia is present.
However, the study was single-center, included laboratory results rather than a representative population sample, and could include repeated testing of individual patients.
The 4.3% figure should not be interpreted as the risk of hypercalcemia for everyone taking high-dose vitamin D.
In a patient with suspected significant vitamin D overdose, clinicians may evaluate:
Test | Why it matters |
|---|---|
Serum total calcium and albumin, or ionized calcium | Identifies clinically important hypercalcemia |
Serum 25(OH)D | Assesses vitamin D exposure and status |
Parathyroid hormone (PTH) | Usually suppressed in vitamin D-associated hypercalcemia |
Creatinine and kidney function | Detects renal impairment |
Phosphate and other electrolytes | Assesses associated metabolic disturbances |
ECG when clinically indicated | Evaluates possible cardiac effects of significant hypercalcemia |
The pattern is usually more informative than any individual value.
1,25-dihydroxyvitamin D is not the routine first-line test for nutritional vitamin D overdose. It may be appropriate when other causes of hypercalcemia, including certain granulomatous diseases or lymphoma, are being investigated. [3]
Occasionally, yes.
A 2026 case report described a patient with severe hypercalcemia and an apparently very high vitamin D result who was ultimately diagnosed with multiple myeloma.
Confirmatory liquid chromatography–tandem mass spectrometry testing demonstrated that the initial vitamin D measurement had been falsely elevated because of laboratory interference. [7]
This was an unusual case.
It reinforces a broader clinical principle: when the history and laboratory results do not fit, clinicians should reassess the diagnosis rather than assuming every elevated measurement proves vitamin D poisoning.
Treatment depends on whether the exposure has caused hypercalcemia, how severe it is, and whether kidney or other organ injury is present.
When overdose is suspected, do not take additional nonessential vitamin D supplements while obtaining medical or poison-center advice.
Clinicians may also temporarily stop calcium-containing supplements when appropriate.
Do not independently discontinue necessary prescription treatment for a complex medical condition without arranging prompt medical guidance.
Hypercalcemia can cause increased urination and fluid losses.
Patients with clinically significant dehydration or hypercalcemia may require intravenous isotonic fluids in a monitored medical setting.
Fluid management must be individualized, particularly for people with heart failure or impaired kidney function.
Depending on the cause and severity, hospital-based treatment can involve:
intravenous fluid resuscitation;
calcitonin for selected situations requiring relatively rapid calcium reduction;
bisphosphonates or other antiresorptive medicines in selected patients;
glucocorticoids for certain vitamin D-mediated causes of hypercalcemia;
renal replacement therapy in uncommon severe or refractory cases.
These treatments are not interchangeable, and selection depends on the specific cause of hypercalcemia, kidney function and clinical condition. [3]
Loop diuretics should not be presented as a routine home or first-line strategy for “flushing out calcium.” Modern hypercalcemia management emphasizes correction of volume depletion; forced diuresis is not routinely recommended solely to lower calcium and may be considered for fluid-overload management in selected patients. [8]
Vitamin D-related hypercalcemia may persist after supplementation is stopped, especially after prolonged or large exposures.
Clinicians may need to repeat:
serum calcium;
kidney function;
electrolytes;
25(OH)D at an appropriate interval.
The follow-up schedule should reflect clinical severity, rather than applying the same testing frequency to every person who has taken vitamin D.
The response depends on the person, product and amount.
An extra routine-strength tablet taken once is not equivalent to prolonged daily use of a concentrated high-dose supplement.
Important details include:
age and weight;
exact product;
concentration and formulation;
amount taken;
whether the event was a single ingestion or repeated dosing;
other calcium or vitamin D products;
current symptoms;
relevant medical conditions.
Do not induce vomiting or attempt home detoxification.
For an uncertain or potentially large ingestion, contact a poison center for individualized advice.
In the United States, Poison Help is available at 1-800-222-1222.
For more information about this service, see Poison Control: Your Lifeline in Emergencies.
Severe confusion, collapse, marked weakness, dehydration with inability to keep fluids down, or other serious symptoms require urgent medical evaluation.
Ordinary sun exposure is not regarded as a typical cause of vitamin D intoxication.
The skin has regulatory mechanisms that limit ongoing formation of active vitamin D precursors with prolonged ultraviolet exposure. [1]
That does not mean prolonged ultraviolet exposure is harmless.
Excessive UV exposure can damage skin and increase skin-cancer risk, so intentionally increasing sun exposure is not an appropriate way to manage a suspected vitamin D deficiency without considering standard sun-protection advice.
For most people, ordinary fortified foods and a balanced diet do not produce the extremely high vitamin D intake associated with classic toxicity.
Always verify whether the label uses:
IU;
micrograms (mcg or µg);
amount per drop;
amount per milliliter;
amount per capsule.
A liquid product that provides vitamin D in one drop is not interchangeable with a product requiring a larger measured volume.
Account for vitamin D from all supplements rather than assessing each product separately.
A weekly prescription should not be treated as a daily supplement.
Infant formulations and adult high-dose products should never be assumed interchangeable.
The Endocrine Society's 2024 clinical practice guideline recommends against routine 25(OH)D screening for generally healthy adults without an established indication.
It also favors daily, lower-dose vitamin D over intermittent high-dose regimens in adults aged 50 years or older when supplementation or treatment is indicated for the purposes addressed by the guideline. [9]
These recommendations do not override treatment for a diagnosed deficiency or a specialized medical condition.
The FDA does regulate dietary supplements, but not through the same premarket approval process used for prescription drugs.
Manufacturers are generally responsible for ensuring that products meet applicable safety and labeling requirements before marketing. FDA can take action against adulterated or misbranded products. [10]
For context on toxicity from other vitamins and supplements, see Vitamin Toxicity: When “Natural” Isn’t Safe.
Vitamin D toxicity is primarily a calcium problem.
The most important acute complications usually arise from hypercalcemia.
The upper intake level is not a toxic dose.
It is a population-level safety reference for long-term intake.
A high 25(OH)D result does not automatically equal clinical poisoning.
Interpret calcium, PTH, renal function, symptoms and exposure history together.
Repeated dosing errors matter.
A weekly high-dose product taken daily may create a very different exposure.
Infant drops require particular care.
Concentrated adult preparations and unclear dose measurements can cause serious errors.
Not every apparent vitamin D intoxication is real.
Rare laboratory interference may require confirmation when results are clinically implausible.
Treatment depends on the severity and cause of hypercalcemia.
It is not appropriate to recommend a universal drug regimen for all suspected vitamin D exposures.
Yes. Excessive or repeated high-dose supplementation can cause vitamin D toxicity, generally through hypercalcemia.
A daily intake of 5,000 IU exceeds the standard adult tolerable upper intake level of 4,000 IU, but it does not automatically cause poisoning. Clinical context, duration, other sources and the reason for treatment matter.
Severe vitamin D intoxication is commonly associated with 25(OH)D concentrations above approximately 150 ng/mL, especially when hypercalcemia is present. A single blood result cannot establish clinical poisoning by itself.
A one-time extra dose is usually different from prolonged excessive intake. The actual risk depends on the dose, formulation, age and other circumstances. A poison center can advise on a specific ingestion.
Yes. Persistent or severe hypercalcemia may cause dehydration, acute kidney injury, kidney stones or calcium deposition in renal tissues.
Many patients recover with recognition and appropriate treatment. Severe or prolonged disease can sometimes cause persistent kidney damage or other complications.
Vitamin D is essential, but more is not always better.
Excessive supplementation, prescribing mistakes, concentrated formulations and poor product quality can cause vitamin D intoxication.
The main clinical concern is hypercalcemia and its consequences, particularly dehydration, neurologic symptoms and kidney injury.
Modern evidence also shows why the diagnosis requires care: a markedly elevated vitamin D laboratory result does not always mean clinically important toxicity is present.
The safest approach is to use the appropriate formulation, follow the intended dosing schedule, avoid unnecessary high-dose supplementation and obtain prompt medical advice when an excessive exposure is suspected.
© All copyright of this material is absolute to Medical toxicology
Dr. Omid Mehrpour (MD, FACMT) is a senior medical toxicologist and physician-scientist with over 15 years of clinical and academic experience in emergency medicine and toxicology. He founded Medical Toxicology LLC in Arizona and created several AI-powered tools designed to advance poisoning diagnosis, clinical decision-making, and public health education. Dr. Mehrpour has authored over 250 peer-reviewed publications and is ranked among the top 2% of scientists worldwide. He serves as an associate editor for several leading toxicology journals and holds multiple U.S. patents for AI-based diagnostic systems in toxicology. His work brings together cutting-edge research, digital innovation, and global health advocacy to transform the future of medical toxicology.
Keep reading
 Food and Drug Toxicology

Amir Mohammad Mottaghi
 Food and Drug Toxicology

Amirhosein Shabrang
 Food and Drug Toxicology
Amirhosein Shabrang
 Food and Drug Toxicology
Amirhosein Shabrang