Dextromethorphan Poisoning: Clinical Recognition, Triage, and Management
Published on 24 Jul 2024

Published on 24 Jul 2024
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/guidelines/dextromethorphan-poisoning-symptoms-treatment-and-prevention
This guideline covers acute and repeated dextromethorphan (DXM) exposures in children and adults. It includes exploratory pediatric ingestions, intentional misuse, self-harm, therapeutic errors, serotonergic drug interactions, and prescription DXM combination products. Detailed management of coingestants such as acetaminophen is covered in their own MedicalToxic.com guidelines.
Identify the product before applying any dose threshold. The isolated-DXM dose thresholds apply only after every active ingredient is known. Many products also contain acetaminophen, chlorpheniramine, a sympathomimetic, guaifenesin or bupropion.
DXM is not a mu-opioid agonist. Its toxicity comes mainly from NMDA antagonism by its metabolite dextrorphan and from serotonin reuptake inhibition.
Intent overrides dose. Any self-harm, misuse or suspected malicious ingestion goes to an emergency department regardless of the amount.
Isolated pediatric exploratory ingestions are usually mild. Serious outcomes cluster in intentional misuse, large ingestions, combination products and serotonergic interactions.
Severe toxicity is a hyperthermic, agitated or comatose patient. Treat with benzodiazepines, active cooling and airway support; recognize serotonin toxicity with the Hunter criteria.
Some exposures last longer. Extended-release polistirex products and CYP2D6 inhibition (quinidine, bupropion, fluoxetine, paroxetine) prolong effects and justify longer observation.
Chronic heavy use has its own signature. DXM hydrobromide can cause bromism, with spurious hyperchloremia and a low or negative anion gap.
Clinical warning
Identify every active ingredient before applying DXM dose thresholds; isolated-DXM thresholds apply only to isolated, unintentional immediate-release exposure.
Refer all self-harm, intentional misuse, suspected malicious ingestion, or patients with more than mild effects to an ED regardless of dose.
For isolated immediate-release DXM: >7.5 mg/kg → ED; 5–7.5 mg/kg → poison-center follow-up every 2 h for up to 4 h; <5 mg/kg and asymptomatic → home.
Serotonergic co-medications and extended-release polistirex require longer observation. Do not induce emesis or give activated charcoal at home.
Severe toxicity: benzodiazepines for agitation/seizures, active cooling for hyperthermia, and airway support. Use Hunter criteria for serotonin toxicity. Measure acetaminophen in every intentional, unknown, or combination-product ingestion.
# | Recommendation | Strength [Chyka grade] | Basis |
|---|---|---|---|
1 | Identify every active ingredient before applying DXM dose thresholds | Must | Chyka 2007 scope; expert consensus |
2 | Refer self-harm, intentional misuse or suspected malicious ingestion to an ED regardless of dose | Must [D] | Chyka 2007 |
3 | Refer any patient with more than mild effects to an ED | Must [C] | Chyka 2007 |
4 | For isolated immediate-release DXM in any age: ED above 7.5 mg/kg; poison center follow-up every 2 hours for 4 hours at 5 to 7.5 mg/kg; home below 5 mg/kg if asymptomatic | Must [C] / Should [D] | Chyka 2007 |
5 | With a serotonergic co-medication, follow up every 2 hours for 8 hours | Should [D] | Chyka 2007 |
6 | After extended-release polistirex, observe at least 8 hours | Should | Expert opinion; Seltzer 2022 |
7 | Measure acetaminophen in every intentional ingestion and every unknown or combination product | Must | Standard toxicology practice |
8 | Do not induce emesis or give activated charcoal at home; consider charcoal in the ED for an alert patient after a recent large ingestion | Must [D] / Consider | Chyka 2007; extrapolated from CTRC 2026 |
9 | Use benzodiazepines first for agitation and seizures, and active external cooling for temperature above 40 °C | Must [C] | Chyka 2007 |
10 | Diagnose serotonin toxicity with the Hunter criteria; consider cyproheptadine | Should | Dunkley 2003; expert opinion |
11 | Naloxone may be tried for coma or respiratory depression, but ventilatory support is definitive | Consider [C] | Chyka 2007 |
12 | In chronic users, check chloride and anion gap and send a bromide level if the gap is low or negative | Should | Case reports |
13 | Behavioral health assessment after any intentional ingestion | Must | Standard practice |
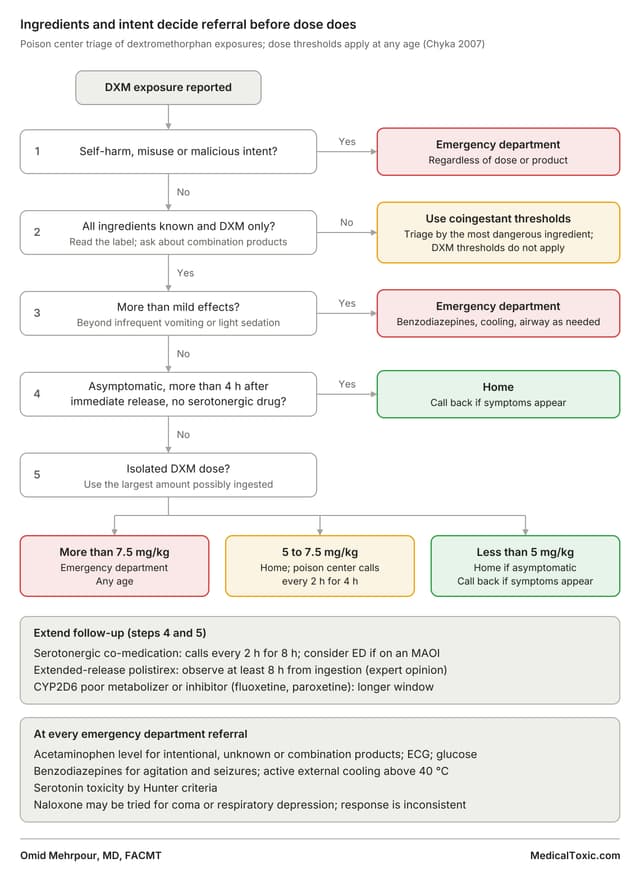
Work down the steps and stop at the first box that refers the patient. Red boxes mean emergency department, amber means follow-up or coingestant triage, and green means home.
The product, not the DXM dose alone, decides the risk. DXM is sold as the hydrobromide salt in syrups, liquid-filled capsules, tablets and lozenges; the usual maximum OTC adult dose is 120 mg per day.
Product type | Examples | Why it matters for triage |
|---|---|---|
Immediate-release single-ingredient | Cough syrups, liquid gels, lozenges | Isolated-DXM thresholds apply; effects usually begin within 1 hour and peak by 2 to 3 hours |
Extended-release polistirex | Delsym (DXM polistirex suspension) | Resin binding slows release; duration of action is roughly two to three times that of standard DXM; onset and peak are delayed |
OTC combination products | Day/night cold products, “cough and cold” tablets | May contain acetaminophen, chlorpheniramine or doxylamine, phenylephrine or pseudoephedrine, guaifenesin; the coingestant may dominate toxicity |
DXM with chlorpheniramine | Coricidin HBP Cough & Cold (30 mg DXM + 4 mg chlorpheniramine per tablet) | Misused as “triple C”; adds anticholinergic toxicity and seizures |
DXM with quinidine (prescription) | Nuedexta, for pseudobulbar affect | Quinidine blocks CYP2D6, raising DXM exposure; quinidine itself causes QRS and QT prolongation in overdose |
DXM with bupropion (prescription) | Auvelity 45/105 mg and 30/105 mg ER tablets, for major depression and Alzheimer’s agitation | Bupropion inhibits CYP2D6, giving nonlinear, greater than dose-proportional DXM exposure; bupropion adds dose-related seizures and cardiotoxicity |
Bulk DXM powder | Purchased online for misuse | Dose is unknown and may be very large; deaths have been reported |
DXM-containing OTC cough products are not recommended for young children, and many U.S. states restrict sales to minors.
Poison center calls involving DXM fall into three groups with different risks: exploratory ingestions in young children, intentional misuse in adolescents and young adults, and therapeutic errors or interactions in adults.
Misuse peaked and then declined. In NPDS, single-substance DXM abuse calls tripled from 2000 to 2006 and then plateaued. Rates were highest at ages 14 to 17 and fell by 56% in that group between 2006 and 2015. [10]
Recent adult data (2015 to 2023). An FDA analysis of NPDS found that adult misuse exposures had been falling sharply before COVID-19; increases during the pandemic were small. Unintentional therapeutic errors rebounded, especially in women, and exceeded pre-pandemic levels by 2023. [12]
Recent pediatric data. In children aged 6 to 17, intentional cold and cough exposures were mostly suspected suicide, with abuse or misuse the second most common reason; adolescents dominated. [11]
Young children. A 2008 to 2014 U.S. surveillance study found 773 cases with an adverse event after a DXM-only product. Of these, 60% involved children younger than 4 years, 78% followed an overdose, and none were fatal; ataxia and tachycardia were the most common effects. [15]
NPDS counts are reported exposures, not confirmed poisonings, and do not capture every case.
DXM is the d-isomer of a morphinan but has negligible mu-opioid activity; its toxicity is dissociative and serotonergic, not opioid. Sigma receptors are no longer classified as opioid receptors. [3]
Target | Main mediator | Clinical correlate |
|---|---|---|
NMDA receptor antagonism | Dextrorphan, the active CYP2D6 metabolite, more than DXM itself | Dissociation, hallucinations, nystagmus, ataxia, agitation; PCP- and ketamine-like picture |
Serotonin and norepinephrine reuptake inhibition | DXM | Serotonin toxicity, especially with MAOIs, SSRIs, SNRIs, linezolid or other serotonergic drugs; DXM inhibits the serotonin transporter without meaningful direct serotonin receptor binding |
Sigma-1 receptor agonism | DXM | Possible contribution to psychotomimetic effects; clinical importance uncertain |
Mu-opioid receptor | Negligible affinity | Explains why naloxone response is inconsistent |
Flushing or urticarial rash (18%) and dystonia (5%) were also reported in pediatric DXM-only adverse events; their mechanism is not established. [15]
CYP2D6 activity and formulation decide how long a DXM exposure lasts. Immediate-release DXM generally peaks within 2 to 3 hours; extended-release polistirex has delayed and prolonged absorption and must be considered separately.
Parameter | Extensive metabolizer | Poor metabolizer or CYP2D6 inhibited | Source |
|---|---|---|---|
Main circulating species | Conjugated dextrorphan; parent DXM barely detectable | Parent DXM | Schadel 1995 |
DXM half-life | About 2 to 4 h | 16 h with quinidine; 19 to 30 h in poor metabolizers | Schadel 1995; Capon 1996 |
DXM exposure (AUC) | Reference | About 150-fold higher in poor metabolizers; 43-fold higher with quinidine | Capon 1996 |
Metabolism. CYP2D6 O-demethylates DXM to dextrorphan; CYP3A4 forms minor metabolites. Clearance of parent DXM depends mainly on CYP2D6 activity rather than renal excretion; its metabolites are excreted in urine, and the effect of severe renal impairment is not well characterized. [17]
Poor metabolizers. About 5% to 10% of people of European ancestry lack CYP2D6 activity. They accumulate parent DXM and may have longer, more serotonergic toxicity.
CYP2D6 inhibitors. Quinidine, bupropion, fluoxetine and paroxetine convert extensive metabolizers toward the poor-metabolizer pattern. Bupropion in Auvelity gives nonlinear, greater than dose-proportional DXM exposure. [2]
Serotonergic co-medications. MAOIs, SSRIs, SNRIs, linezolid, methylene blue, tramadol and meperidine add serotonin toxicity risk. MAOI combinations carry the highest risk.
Extracorporeal removal. No evidence supports hemodialysis or other extracorporeal removal for DXM.
DXM toxicity looks dissociative and sympathomimetic: ataxia, nystagmus, agitation and tachycardia are the signature findings. Effects of immediate-release products usually begin within an hour.
Severity | Findings |
|---|---|
Mild | Infrequent vomiting; somnolence with the patient arousable to voice or light touch |
Moderate | Ataxia, nystagmus, mydriasis, agitation, hallucinations, tachycardia, hypertension, diaphoresis, dystonia, flushing or urticarial rash |
Severe | Hyperthermia above 40 °C, rigidity or clonus, seizures, coma, respiratory depression, psychosis with danger to self or others |
Dose is a weak predictor of severity. The consensus guideline's evidence review found case reports with symptoms after 5 to 21 mg/kg in young children given combination or extended-release products; most doses were unverified and coingestants could not be excluded. The 5 and 7.5 mg/kg values used in triage below are operational referral thresholds, not toxicity cutoffs. Earlier statements that “moderate toxicity occurs at 7.7 mg/kg and severe at 7.8 mg/kg” have no biological meaning and should not be used. [5]
Suspect it when DXM is taken with an MAOI, SSRI, SNRI, linezolid or another serotonergic drug, or in a large ingestion.
Diagnose with the Hunter criteria:
spontaneous clonus;
inducible or ocular clonus with agitation or diaphoresis;
tremor with hyperreflexia; or
hypertonia with temperature above 38 °C and ocular or inducible clonus. [7]
Small case series, mainly from India, describe children under 5 years with sudden unresponsiveness after DXM-containing cough syrup and cytotoxic edema of both cerebellar hemispheres on MRI, resembling opioid-associated POUNCE syndrome.
Two further children recovered fully with supportive care and IV methylprednisolone. Causality and mechanism are unproven, and a role for coformulated ingredients has not been excluded.
Consider brain MRI in a young child with persistent or otherwise unexplained encephalopathy, coma or marked ataxia after a DXM-containing product, particularly when the course is atypical or not improving.
Reserve neurosurgical consultation for demonstrated cerebellar edema with mass effect or hydrocephalus. [1] [19]
Repeated use of DXM hydrobromide can cause bromism: confusion, ataxia, psychosis and stupor. Bromide interferes with chloride assays, producing spurious hyperchloremia and a low or negative anion gap. Chronic misuse is also linked to mania, psychosis and dependence. [14]
Apply the checks in order and stop at the first that sends the patient to an emergency department.
The dose thresholds come from the AAPCC consensus guideline and apply to children and adults alike; they are valid only for isolated, unintentional ingestion of an immediate-release product. [5]
Step | Situation | Action | Strength [Chyka grade] |
|---|---|---|---|
1 | Self-harm, intentional misuse, or suspected malicious administration | ED referral regardless of dose or product | Must [D] |
2 | Product unknown, or contains acetaminophen, an antihistamine, a sympathomimetic, quinidine or bupropion | Triage by the most dangerous ingredient; isolated-DXM thresholds do not apply | Must |
3 | More than mild effects: more than infrequent vomiting, or somnolence beyond arousable to voice or light touch | ED referral | Must [C] |
4 | Asymptomatic, more than 4 hours after an immediate-release ingestion, and no serotonergic co-medication | Home | Should [C] |
5 | More than 7.5 mg/kg | ED referral | Must [C] |
6 | 5 to 7.5 mg/kg | Home, with poison center follow-up about every 2 hours for up to 4 hours; ED if more than mild symptoms develop | Should [D] |
7 | Less than 5 mg/kg and asymptomatic | Home, with standard advice to call back | Should |
Serotonergic co-medication (MAOI, SSRI and similar): poison center follow-up every 2 hours for 8 hours [Chyka D]. For a patient taking an MAOI, consider ED referral for any ingestion above a therapeutic dose (expert opinion).
Extended-release polistirex: the 4-hour window does not cover delayed absorption. Extend follow-up to at least 8 hours from ingestion, and refer if symptoms appear (expert opinion; not studied).
Known poor metabolizer or CYP2D6 inhibitor: expect slower onset and longer effects; use the same thresholds but a longer follow-up window (expert opinion).
At home: do not induce emesis, and do not give activated charcoal [Chyka D].
The previous MedicalToxic.com threshold that allowed home management of children up to 10 mg/kg is retired; it was not supported by the cited consensus guideline.
The ED workup aims to find the coingestant, serotonin toxicity and hyperthermia; there is no useful DXM level.
Examine core temperature, mental status, pupils, nystagmus, tone, reflexes and clonus at arrival and at each reassessment.
Test | When | Why |
|---|---|---|
Serum acetaminophen concentration | Every intentional ingestion and every unknown or combination product | Combination products are common, and acetaminophen toxicity is silent early |
Salicylate concentration | Product unknown or salicylate-containing | Unrecognized coingestant |
Point-of-care glucose | Altered mental status | Excludes hypoglycemia |
ECG | All ED patients | Isolated DXM rarely affects conduction; QRS or QTc changes point to quinidine, bupropion or an antihistamine |
Electrolytes, creatinine, chloride and anion gap | Moderate or severe toxicity; chronic use | Low or negative anion gap with high chloride suggests bromism; send a serum bromide |
Creatine kinase | Agitation, rigidity, hyperthermia or seizures | Rhabdomyolysis |
Pregnancy test | People of reproductive age | Affects drug choices and disposition |
Brain MRI | Consider in a young child with persistent or unexplained encephalopathy, coma or marked ataxia | Cerebellar edema (DANCE) |
Urine drug screens. DXM is associated with false-positive phencyclidine immunoassays. A positive PCP screen in a DXM exposure needs confirmation and should not change management. [16]
Serum DXM concentrations are not available in a clinically useful time and do not guide treatment.
Treatment is supportive and symptom-directed: benzodiazepines, active cooling and airway support manage almost every severe case. There is no specific antidote.
Problem | Treatment | Notes |
|---|---|---|
Decontamination | Single-dose activated charcoal 1 g/kg (max 50 g) for an alert patient with a protected airway after a recent large ingestion | Chyka supports use within 1 hour [D]. The 2026 CTRC recommendations allow individualized use beyond 1 hour for selected poisons and an additional dose when absorption is prolonged. Applying this to DXM, including polistirex, is expert extrapolation; it matters most for polistirex and for coingestants such as acetaminophen. No DXM-specific outcome data exist. No emesis or lavage. |
Agitation, psychosis | IV benzodiazepines titrated to calm, for example lorazepam 1 to 2 mg in adults, 0.05 to 0.1 mg/kg in children | Calm environment. Avoid physical restraint without sedation, which worsens hyperthermia. Antipsychotics are second-line and avoided when serotonin toxicity or hyperthermia is suspected (expert opinion). |
Seizures | IV benzodiazepines first; phenobarbital or propofol if refractory | Check for bupropion or other proconvulsant coingestants |
Hyperthermia above 40 °C | Active external cooling (ice-water immersion or evaporative cooling) plus benzodiazepines | Antipyretics do not work. Refractory cases need sedation, intubation and non-depolarizing paralysis. [Chyka C] |
Serotonin toxicity | Stop serotonergic drugs; benzodiazepines; cooling | Consider cyproheptadine: adults 12 mg orally or by tube, then 2 mg every 2 hours while symptoms persist; evidence is limited. Severe cases need intubation and non-depolarizing paralysis; avoid succinylcholine if rhabdomyolysis is possible. |
Coma, respiratory depression | Airway and ventilatory support; naloxone in standard opioid-reversal doses may be tried | Response is inconsistent because DXM has negligible mu-opioid activity. A marked response should raise suspicion of an opioid coingestant. [Chyka C] |
Dystonia | Benzodiazepine or diphenhydramine | Avoid diphenhydramine if anticholinergic toxicity is present |
Bromism | Stop exposure; IV sodium chloride with adequate urine output | Hemodialysis for severe neurologic toxicity or renal failure |
Acetaminophen coingestant | Acetylcysteine by the standard nomogram or protocol | See the MedicalToxic.com acetaminophen guideline |
The charcoal approach above uses the DXM-specific consensus guideline and, where explicitly stated, extrapolation from the 2026 CTRC activated-charcoal recommendations. [5] [9]
After medical stabilization, every intentional ingestion must have a psychiatric or behavioral health assessment, and adolescents with misuse should be offered substance use counseling.
The coingestant often causes the serious morbidity. In one report of adolescent Coricidin cases, one patient had prolonged anticholinergic toxicity and another developed acetaminophen hepatotoxicity after recreational use of a flu product. [13]
Coingestant | Typical products | Added toxicity | Key action |
|---|---|---|---|
Acetaminophen | Day and night cold and flu products | Delayed hepatotoxicity, often silent early | Acetaminophen concentration at 4 hours or later; acetylcysteine by protocol |
Chlorpheniramine, doxylamine, diphenhydramine | Coricidin HBP Cough & Cold, nighttime products | Anticholinergic delirium, hyperthermia, seizures; diphenhydramine adds QRS widening | ECG; treat as anticholinergic toxicity with toxicologist input |
Phenylephrine, pseudoephedrine | Decongestant combinations | Hypertension, tachycardia; reflex bradycardia with phenylephrine | Benzodiazepines; treat severe hypertension |
Guaifenesin | Expectorant combinations | Low acute toxicity | Usually no specific action |
Bupropion | Auvelity | Seizures, which may be delayed with extended release; tachycardia; QRS and QTc prolongation | Triage by bupropion thresholds; see the MedicalToxic.com bupropion guideline |
Quinidine | Nuedexta | QRS and QT prolongation, hypotension, cinchonism | ECG and cardiac monitoring |
Ethanol, cannabis, other drugs | Recreational co-use | Additive CNS depression or agitation | Ask directly; screen for intent |
Young children. Most exploratory ingestions of DXM-only products cause mild CNS and autonomic effects. Large polistirex ingestions can be life-threatening: a 23-month-old who took 71.4 mg/kg of DXM polistirex needed intubation, with toxicity lasting as long as the formulation's duration of action. Therapeutic dosing errors are common; OTC cough products are not recommended for young children. [18]
Adolescents and young adults. Intentional misuse always goes to the ED. Ask about Coricidin and acetaminophen products, alcohol and other drugs, and screen for self-harm.
Older adults and prescription users. Patients on Nuedexta or Auvelity, including those with dementia, face therapeutic errors and serotonergic polypharmacy. Assess the quinidine or bupropion component separately.
CYP2D6 poor metabolizers. Expect delayed onset, higher parent DXM exposure and longer duration; extend observation.
Pregnancy. Therapeutic DXM use was not associated with more major malformations than baseline. Overdose management is the same; the best fetal care is maternal stabilization, with obstetric consultation when the fetus is viable. Auvelity is not recommended in pregnancy. [8]
Observation length follows the formulation and the interaction risk, not the dose alone. Windows longer than 4 hours below are expert opinion.
Situation | Minimum observation from ingestion | Discharge or medical clearance when |
|---|---|---|
Immediate-release DXM only | 4 hours | Asymptomatic or only mild effects that have resolved; normal vital signs and temperature |
Extended-release polistirex | At least 8 hours, longer if symptomatic | Symptoms resolved and no new findings for several hours |
Serotonergic co-medication or MAOI | 8 hours | No clonus, hyperreflexia, hyperthermia or agitation |
Combination product | Longest window of any ingredient | Acetaminophen concentration non-toxic; coingestant criteria met |
Auvelity or Nuedexta | By the bupropion or quinidine component | ECG normal; no seizures; component criteria met |
Admit patients with persistent moderate effects, repeated benzodiazepine needs, serotonin toxicity or seizures.
Admit to ICU for hyperthermia above 40 °C, coma, respiratory depression, refractory agitation or seizures.
Consult a medical toxicologist for severe toxicity, serotonin toxicity, prescription DXM combinations, suspected bromism or suspected cerebellar edema in a child.
Before discharge, intentional ingestions need behavioral health clearance; families of young children need safe-storage advice.
Age-restricted sales are already widespread. California first banned DXM sales to minors in 2012, and 21 states had age-18 sales laws by July 2021. [6]
Families: store all cough and cold products up and away; use the dosing device supplied; do not combine products with overlapping ingredients; avoid OTC cough products in young children.
Adolescents: parents, schools and pharmacists should recognize misuse signs and Coricidin or bulk-powder purchases.
Prescribers and pharmacists: check for serotonergic drugs and CYP2D6 inhibitors before recommending DXM, and screen for duplicate DXM or bupropion before starting Auvelity.
Poison centers: report DXM cases to NPDS with product and intent coded, so prescription combinations and polistirex exposures can be tracked separately.
Most recommendations here rest on case reports, case series and consensus; none is supported by a randomized trial.
The 5 and 7.5 mg/kg thresholds date from 2007 and have not been validated prospectively.
The toxic dose and kinetics of polistirex overdose are not defined; the 8-hour observation window is expert opinion.
Overdose data for Auvelity and Nuedexta are sparse.
Activated charcoal has no DXM-specific outcome data.
Cyproheptadine and naloxone benefit in DXM toxicity rests on case reports.
DANCE syndrome has fewer than ten published cases; incidence, mechanism and the role of corticosteroids are unknown.
Keep reading