Battery Ingestion and Exposure: Clinical Recognition, Triage, and Management
Published on 24 Jul 2024 · Updated 02 Oct 2026

Published on 24 Jul 2024 · Updated 02 Oct 2026
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/guidelines/battery-ingestion-and-exposure-a-comprehensive-guide
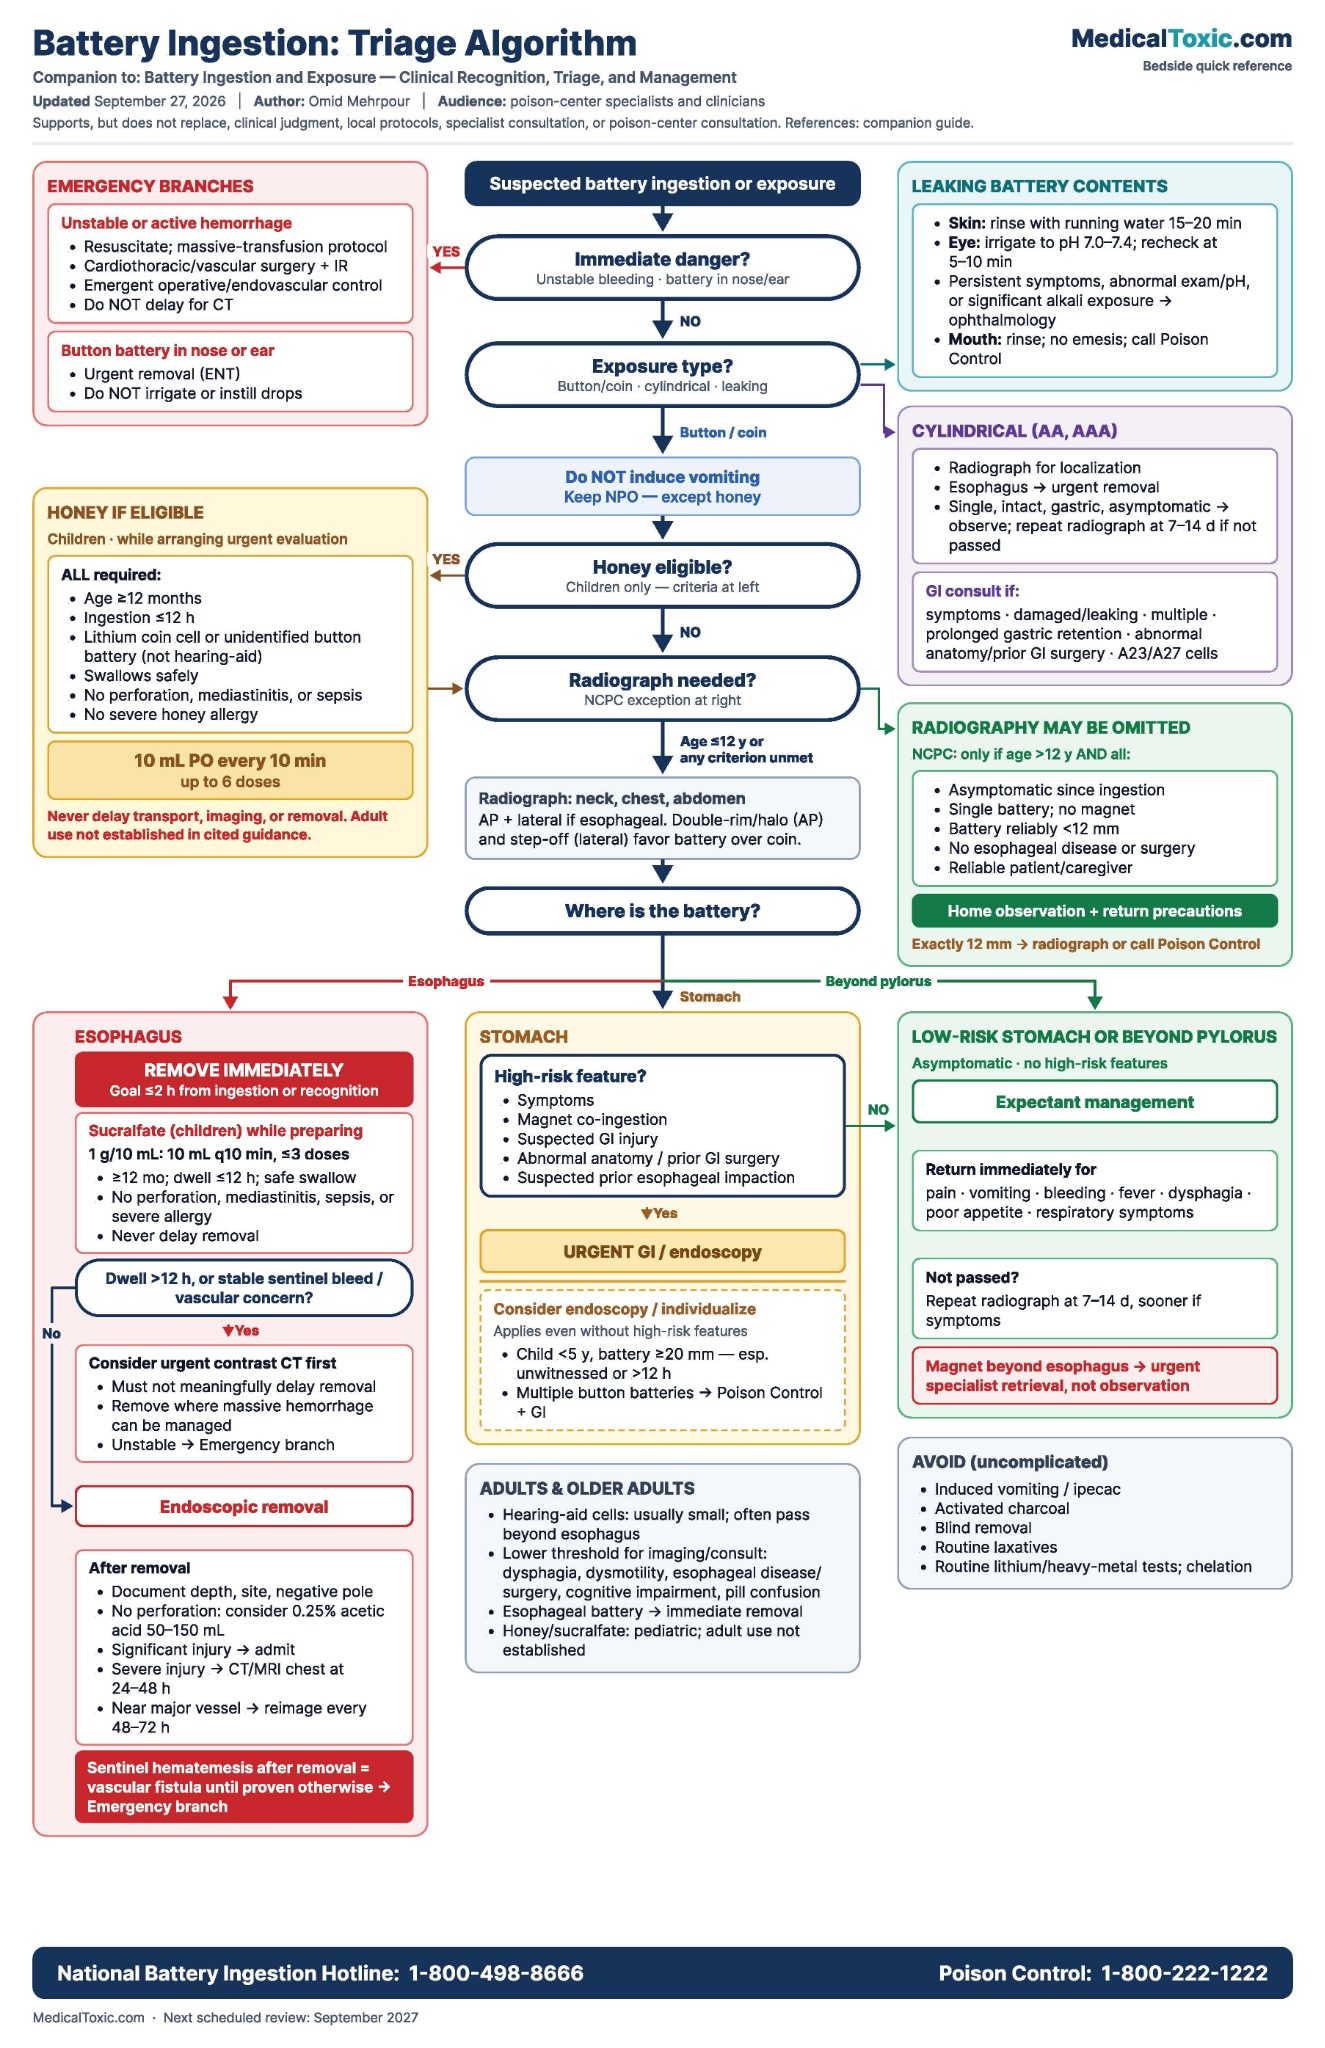
Evidence-informed clinical guideline
This evidence-informed guide supports, but does not replace, clinical judgment, local protocols, specialist consultation, or poison-center consultation.
This evidence-informed guide addresses the initial assessment and management of button or coin battery ingestion, cylindrical battery ingestion, batteries lodged in the nose or ear, and exposure to leaking battery contents.
The guide emphasizes pediatric exposures because most formal management algorithms are pediatric, but battery ingestion also occurs in adults. In older adults, hearing-aid batteries are a common source of button-battery ingestion. [13]
Management should be based primarily on:
battery type and size;
patient age;
anatomic location;
time since ingestion;
symptoms;
whether the battery is intact or damaged;
number of batteries ingested;
magnet co-ingestion; and
relevant gastrointestinal anatomy or prior surgery.
Button or coin batteries require particular attention because an esophageal battery can produce severe tissue injury within approximately 2 hours. [1–3]
Clinical warning
Suspected esophageal button or coin battery ingestion is a time-critical emergency. Severe tissue injury may develop within approximately 2 hours, and an esophageal battery should be removed immediately. Do not wait for symptoms to develop, and do not delay emergency evaluation or removal to administer honey or sucralfate. [1–3]
If a lithium coin cell may have been swallowed—or the button-battery type is unidentified and is not known to be a hearing-aid battery—give honey only when the child is ≥12 months old, ingestion occurred within the previous 12 hours, swallowing is safe, and honey is immediately available: 10 mL orally every 10 minutes for up to 6 doses. Honey is a mitigation measure, not definitive treatment. [2,3,5]
After removal, risk does not end. Esophageal injury may continue to progress, and delayed perforation, airway fistula, vascular fistula with catastrophic hemorrhage, stricture, recurrent laryngeal nerve injury, and other complications may develop days to weeks later. [1–3]
Battery exposures remain an important pediatric injury problem.
A U.S. national study estimated 70,322 battery-related emergency department visits among children younger than 18 years from 2010 through 2019, corresponding to 9.5 visits per 100,000 children annually. Button batteries accounted for 84.7% of cases in which battery type was documented, and ingestion accounted for 90% of visits. Children 5 years or younger had the highest emergency-department visit rate. [4]
Large lithium coin cells are responsible for a disproportionate share of severe esophageal injuries. Batteries approximately 20 mm or larger, particularly in young children, have the greatest risk of becoming lodged in the esophagus. [1–3]
In the United States, Reese's Law, enacted in 2022, established federal requirements addressing button and coin battery packaging, labeling, and battery-compartment security in consumer products. [10]
Determine, when possible:
battery type: button/coin versus cylindrical or another form;
battery diameter or dimensions;
number of batteries;
time of ingestion;
presence of a magnet or other foreign body;
symptoms;
whether the battery was chewed, damaged, or leaking;
previous esophageal or gastrointestinal disease or surgery.
Do not assume an unwitnessed ingestion is benign. Serious button battery ingestions are often unwitnessed.
Possible symptoms include:
drooling;
dysphagia;
refusal to eat;
vomiting;
chest or abdominal pain;
coughing;
choking;
gagging;
wheezing;
noisy breathing;
hematemesis;
melena;
unexplained respiratory symptoms.
A child with an esophageal button battery may initially be asymptomatic. [1–3]
The major mechanism of injury from an impacted button battery is electrolysis of tissue fluid with hydroxide production at the battery's negative pole, producing rapidly progressive alkaline tissue injury.
Pressure and leakage of battery contents can contribute, but systemic absorption of battery metals is not the principal mechanism of severe injury. [3,6]
Clinically important injury may begin within minutes, and severe esophageal injury can develop within approximately 2 hours.
Tissue injury can continue to progress after the battery has been removed. [1–3]
Do not induce vomiting.
If a lithium coin cell may have been swallowed, or the button-battery type is unidentified and is not known to be a hearing-aid battery, give honey while arranging immediate medical evaluation when all of the following apply:
child is 12 months or older;
ingestion occurred within the previous 12 hours;
the child can swallow normally;
honey is readily available.
Give:
Honey 10 mL orally every 10 minutes for up to 6 doses.
Honey may reduce progression of local esophageal injury but must never delay emergency evaluation or battery removal.
Do not give honey:
to infants younger than 12 months;
when the battery may have been in the esophagus for more than 12 hours;
when swallowing is unsafe;
when esophageal perforation, mediastinitis, or sepsis is suspected;
in a patient with a known severe honey allergy. [2,3,5]
Except for appropriate honey administration, keep the patient NPO until an esophageal battery has been excluded.
Children with known or suspected button battery ingestion generally require immediate radiographic localization.
Radiographs should include the entire:
neck;
esophagus;
abdomen.
A button battery may be distinguished from a coin by:
the double-rim or halo sign on the AP view;
a step-off on the lateral view.
AP and lateral views should be obtained when an esophageal battery is identified or suspected. [3]
Do not assume that an apparent coin is actually a coin until a button battery has been excluded.
Most suspected pediatric button battery ingestions require radiographic localization.
The National Capital Poison Center permits observation without initial radiography only in a narrow lower-risk group involving patients older than 12 years when all of the following are satisfied:
completely asymptomatic;
only one battery swallowed;
no magnet swallowed;
battery reliably identified as <12 mm;
no history of prior esophageal surgery, stricture/narrowing, motility disorder, or other esophageal disease;
patient or caregiver is reliable, mentally competent, and agrees to promptly report symptoms and seek evaluation when indicated.
The current NCPC webpage is internally inconsistent at exactly 12 mm: the parent criterion refers to batteries ≤12 mm, but the detailed eligibility subcriterion specifies <12 mm.
This guideline therefore uses the more conservative detailed threshold of <12 mm.
For a battery measured at exactly 12 mm, obtain radiographic localization or consult Poison Control rather than assuming eligibility for the no-radiograph pathway.
If any other criterion is not met, radiographic localization is appropriate. [3]
An esophageal button battery is a medical emergency.
The battery should be removed immediately, ideally within 2 hours of ingestion or recognition, regardless of fasting status. [1–3]
Honey or sucralfate must not delay endoscopy.
After radiographic confirmation of an esophageal battery, sucralfate suspension 1 g/10 mL may be given as:
10 mL orally every 10 minutes for up to 3 doses
while preparing for endoscopic removal when:
the patient is at least 12 months old;
the battery has not potentially been in the esophagus for more than 12 hours;
the patient can swallow safely.
Avoid sucralfate when:
esophageal perforation is suspected;
mediastinitis is suspected;
sepsis is suspected;
swallowing is unsafe;
there is a known severe sucralfate allergy.
Sucralfate must never delay removal. [1,3,5]
Endoscopic removal allows both retrieval and assessment of mucosal injury.
The endoscopist should document:
location of the battery;
orientation of the negative pole;
depth and circumferential extent of injury;
evidence of perforation;
proximity of injury to the airway or major vessels.
If no perforation is evident after removal, 50–150 mL of sterile 0.25% acetic acid irrigation may be considered to neutralize residual alkaline injury where institutional expertise and protocols support this practice. [1,3,6]
Removal of the battery does not end the risk.
Tissue injury can continue after extraction.
Potential delayed complications include:
esophageal perforation;
mediastinitis;
tracheoesophageal fistula;
esophageal stricture;
vocal cord paralysis;
tracheal injury;
spondylodiscitis;
arterial-esophageal fistula and catastrophic hemorrhage.
These complications may appear days to weeks after removal, and strictures or neurologic complications may present even later. [1–3]
The intensity of post-removal monitoring should be based on the location and severity of injury.
Patients with significant esophageal injury generally require admission.
If diagnosis or removal is delayed, particularly more than 12 hours, or if there is a sentinel bleed or other concern for vascular proximity in a hemodynamically stable patient, urgent contrast-enhanced CT should be considered before removal to evaluate vascular proximity or injury.
MRI is an option only after the battery has been removed.
Pre-removal imaging should be obtained as part of the emergency pathway and must not meaningfully delay battery removal.
A long-dwelling esophageal battery with suspected vascular proximity should be removed in a setting prepared for massive hemorrhage, with immediate surgical and/or interventional vascular support available.
Prioritize:
resuscitation;
massive-hemorrhage/transfusion activation;
emergent operative and/or endovascular hemorrhage control.
Do not delay definitive hemorrhage control for CT imaging. [1,2]
If severe mucosal injury is identified at endoscopy, current ESPGHAN guidance supports contrast CT or MRI of the chest within approximately 24–48 hours.
When esophageal wall injury is close to a major vessel, repeat imaging every 48–72 hours should be considered to assess progression. [1,2]
Sentinel hematemesis or other gastrointestinal bleeding after significant esophageal battery injury should be treated as potentially life-threatening vascular fistulization until proven otherwise.
When significant esophageal injury is present, feeding should not automatically resume immediately after removal.
Assessment for perforation or leak, commonly with an esophagram, should guide advancement of diet.
Subsequent imaging, endoscopy, bronchoscopy, and dietary restrictions depend on the depth and location of injury. [1–3]
Gastric location does not automatically eliminate risk because the battery may previously have lodged in the esophagus.
Urgent endoscopic assessment is indicated or strongly considered when:
the patient is symptomatic;
a magnet was also ingested;
gastrointestinal injury is suspected;
relevant abnormal gastrointestinal anatomy or previous surgery is present;
delayed passage or prior esophageal impaction is suspected.
For an asymptomatic child younger than 5 years with a battery ≥20 mm, particularly after an unwitnessed ingestion or when ingestion occurred more than 12 hours previously, endoscopic evaluation should be considered because clinically important esophageal injury may have occurred before the battery reached the stomach. [1–3,11]
Current NCPC and ESPGHAN algorithms do not define a specific mandatory-removal threshold for this scenario.
Multiple-battery ingestion is excluded from the NCPC lower-risk no-radiograph pathway, and gastric mucosal injury has been reported after ingestion of multiple button cells. [3,15]
Obtain poison-center and gastroenterology consultation and individualize the decision regarding early endoscopic retrieval rather than treating the case as routine single-battery observation.
If ingestion was witnessed and radiography confirms that the battery reached the stomach very rapidly, the likelihood of significant prior esophageal impaction is lower.
If none of the high-risk features above are present and the patient is asymptomatic, expectant outpatient management is usually appropriate.
Give clear return precautions and, if passage has not been documented, repeat radiography in approximately 7–14 days, or sooner if symptoms develop. [1,2]
An asymptomatic patient with a button battery beyond the pylorus and no evidence of gastrointestinal injury can usually be managed expectantly.
Parents or caregivers should watch for passage when practical and return immediately for:
abdominal or chest pain;
vomiting;
hematemesis or melena;
fever;
difficulty swallowing;
decreased appetite;
respiratory symptoms;
other new concerning symptoms.
Use the same return precautions and follow-up interval described above for a low-risk gastric battery.
If passage has not been documented, repeat radiography in approximately 7–14 days, or sooner if symptoms develop. [1,2]
Endoscopic or surgical retrieval is required when symptoms, non-progression, magnet co-ingestion, or other high-risk circumstances warrant intervention.
Button-battery ingestion also occurs in adults, particularly older adults.
In a prospective cohort of patients aged 65 years and older, 76% of ingested button batteries came from hearing aids and most patients were asymptomatic. Hearing-aid cells are typically small, commonly zinc-air button cells, and usually pass after they have traversed the esophagus. [13]
Risk assessment in adults should not rely on battery size alone.
Particular caution is warranted in patients with:
dysphagia or impaired esophageal motility;
known esophageal disease;
prior esophageal surgery;
cognitive impairment;
ingestion caused by mistaking a battery for medication.
A button battery lodged in the adult esophagus is managed with the same urgency as in a child: immediate removal is required.
Symptoms, uncertain location, an unknown or larger battery, or concern for impaired passage should prompt radiographic localization and appropriate specialty consultation. [3,13]
The pre-removal honey and sucralfate recommendations in this guide are derived from pediatric guidance and pediatric/animal evidence.
Their use in adults is not specifically established by the cited guidelines; if considered, it should be individualized with poison-center and procedural-specialist input and must never delay localization or removal.
Cylindrical batteries should not be managed as if they have the same risk profile as button batteries.
Most intact cylindrical batteries that reach the stomach or intestine pass without serious injury.
Clinically important injury is more likely when a battery:
becomes lodged;
is damaged or leaking;
remains in the stomach for a prolonged period;
is one of multiple batteries;
causes symptoms;
is ingested by a patient with abnormal gastrointestinal anatomy or prior gastrointestinal surgery. [7,8]
A 2025 pediatric series included 45 children with AA/AAA ingestion. Endoscopic removal was performed in 12 of 45; none of those 12 had esophageal or gastric mucosal lesions. No intestinal perforations or surgical complications were reported in the full cohort. The authors supported conservative management for most uncomplicated cases. [8]
A cylindrical battery retained in the esophagus should be removed urgently.
A single, intact cylindrical battery in an asymptomatic patient can generally be observed with clinical follow-up.
The ESGE/ESPGHAN pediatric endoscopy guideline specifically suggests outpatient observation for a single cylindrical battery in the stomach, with repeat radiography in approximately 7–14 days if passage has not been documented.
Earlier reassessment is warranted if symptoms develop. [7]
Endoscopic consultation or removal should be considered for:
symptoms;
damaged or leaking batteries;
multiple batteries;
prolonged gastric retention;
prior gastrointestinal surgery or abnormal anatomy;
specialized high-voltage cylindrical cells such as A23 or A27 batteries.
A23 batteries are constructed from stacked button cells. [8]
Routine corticosteroids or prophylactic antibiotics are not standard therapy for uncomplicated cylindrical battery ingestion.
Rechargeable lithium-ion cells, nickel-metal hydride cells, nickel-cadmium cells, and other battery designs should not be converted into separate presumed systemic poisoning syndromes solely on the basis of their chemical constituents.
Ingestion management should primarily consider:
physical size and shape;
location;
obstruction risk;
symptoms;
whether the casing is intact;
evidence of leakage or rupture.
The category “nickel lithium battery” is not a clinically useful standard consumer battery classification and should not be used as a separate toxicologic category.
Routine serum lithium concentrations, routine heavy-metal testing, or chelation are not indicated for an uncomplicated intact button battery ingestion.
For unusual ruptured or leaking batteries, management should be individualized with poison-center consultation and, when necessary, product-specific composition information. [3]
Thermal runaway, fire, explosion, and inhalation of decomposition products from damaged lithium-ion batteries represent a different exposure scenario from ingestion and should be assessed according to the actual burn, inhalational, or chemical exposure.
Button batteries in the nose or external auditory canal are also emergencies because local electrical injury can rapidly produce tissue necrosis.
Complications include:
nasal septal necrosis or perforation;
external auditory canal injury;
tympanic membrane injury;
hearing impairment;
deeper tissue destruction.
Remove the battery urgently, usually with ENT involvement when necessary.
Do not irrigate the ear or nose and do not instill drops before removal, because additional fluid can facilitate electrochemical injury. [9]
A ruptured or leaking battery can expose the skin, eyes, or mucous membranes to irritating or caustic material.
Remove contaminated clothing and rinse exposed skin immediately with copious running water for approximately 15–20 minutes.
Remove contact lenses if readily possible and begin immediate, copious irrigation with room-temperature water or an isotonic irrigating solution.
Do not stop solely because a fixed irrigation time has elapsed.
Continue irrigation until ocular surface/conjunctival pH has returned to the physiologic range of approximately 7.0–7.4.
After irrigation is stopped, wait approximately 5–10 minutes and recheck pH in the conjunctival fornix so that residual irrigation fluid does not falsely normalize the measurement.
Resume irrigation if pH is abnormal or rebounds.
Inspect and irrigate the fornices carefully for retained particulate material when relevant.
Persistent pain, visual symptoms, abnormal examination findings, or significant alkali exposure warrants urgent medical and ophthalmologic evaluation. [12,14]
Rinse the mouth.
Do not induce vomiting.
Contact a poison center for product-specific advice if battery contents were swallowed or significant oral exposure occurred.
For uncomplicated battery ingestion, avoid:
induced vomiting or ipecac;
activated-charcoal gastrointestinal decontamination;
blind removal techniques;
routine laxatives;
routine serum or urine heavy-metal testing;
routine chelation.
Management should focus on localization, timely removal when indicated, assessment of local injury, and appropriate follow-up. [3]
For suspected button battery ingestion in the United States:
National Battery Ingestion Hotline:
1-800-498-8666
Poison Control:
1-800-222-1222
Poison-center consultation is particularly useful when the battery type, size, timing, or appropriate disposition is uncertain.
Button and coin batteries should be stored where children cannot reach them, including used batteries, which may retain enough voltage to cause severe injury.
Battery compartments should remain securely closed.
Products with broken or easily accessible battery compartments should be repaired, replaced, or kept away from children.
Reese's Law and subsequent CPSC regulations established child-resistant packaging, warning-label, battery-compartment, and product-safety requirements for many button and coin battery products in the United States. [10]
For broader prevention information, see Battery Ingestion and Exposure: Essential Prevention and Treatment Tips.
Esophageal button battery: immediate removal, ideally within 2 hours.
Honey: 10 mL every 10 minutes, up to 6 doses, when a lithium coin cell is suspected or the button-battery type is unidentified unless known to be a hearing-aid battery; the child is ≥12 months; ingestion occurred within 12 hours; and the child can swallow. Avoid honey if perforation, mediastinitis, or sepsis is suspected, swallowing is unsafe, or there is a severe honey allergy. Do not delay transport.
Sucralfate: after esophageal localization, 10 mL every 10 minutes, up to 3 doses while preparing for removal when the patient is ≥12 months, exposure is within 12 hours, and swallowing is safe. Avoid sucralfate if perforation, mediastinitis, or sepsis is suspected or there is a severe sucralfate allergy. Never delay removal to administer it.
Imaging: neck, esophagus, and abdomen; look for the double-rim and step-off signs.
After removal: injury may progress. Assess depth, vascular proximity, airway involvement, perforation, and risk of delayed fistula or stricture.
Gastric button battery: management depends on symptoms, age, battery size, timing, magnet co-ingestion, possible prior esophageal impaction, and whether more than one battery was ingested. Multiple gastric button batteries are not covered by a firm removal threshold in current major algorithms; obtain poison-center/GI input and individualize management.
Cylindrical battery: most uncomplicated intact batteries can be managed conservatively once beyond the esophagus; symptoms, damage, multiple batteries, abnormal anatomy, or prolonged retention increase the need for intervention.
Systemic lithium or heavy-metal poisoning is not the primary concern after routine intact battery ingestion.
Aydin O, Urganci N, Yıldız MP, Kalyoncu D. The dangerous foreign body in the esophagus: Alkaline. World J Pediatr Surg. 2018.
Blatnik DS, Toohill RJ, Lehman RH. Complication of an alkaline battery as a foreign body in the esophagus. Ann Otol Rhinol Laryngol. 1977;86(5 Pt 1):611-615.
Chandler, M. D., Ilyas, K., Jatana, K. R., Smith, G. A., McKenzie, L. B., & MacKay, J. M. (2022). Pediatric Battery-Related Emergency Department Visits in the United States: 2010–2019. Pediatrics, 36032018. DOI: 10.1542/peds.2022-056709.
Chaudhary S, Shrivastava V, Thanlange SB. Lithium toxicity secondary to ingestion of lithium button battery. Indian J Pediatr. 2008;75(5):559-561.
Corbus D, Hammel C, Mark J. Current status of environmental, health, and safety issues of nickel-metal-hydride batteries for electric vehicles. Energy. 1993.
Granata G, Pagnanelli F, Moscardini E, Takahashi S, Toro L, Beolchini F. Recycling of spent nickel-cadmium batteries by selective precipitation. J Clean Prod. 2012;24:8-13.
Hammami M, Alkaade S, Piraka C, Taylor JR. Endoscopic Retrieval vs Observation in Cylindrical Battery Ingestion. Ochsner J. 2018;19:157-165.
Hui ML-Y, Ng JH-Y. First case of nickel-metal hydride battery ingestion in a child. J Surg Case Rep. 2023.
Järup L. Hazards of heavy metal contamination. Br Med Bull. 2003;68:167-182.
Koşar I, Gorgulu M. Ingestion of cylindrical battery: A medical treatment challenge. Pediatr Emerg Care. 2021.
Koşar M, Gorgulu O. Ingestion of Cylindrical Battery and Medical Treatment. Pak J Med Sci. 2021;37(2):595-597.
Leinwand KL, Brumbaugh D, Kramer R. Button Battery Ingestion in Children: A Paradigm for Management of Severe Pediatric Foreign Body Ingestions. Gastrointest Endosc Clin N Am. 2016;26(1):99-118.
Litovitz T. Battery ingestions: product accessibility and clinical course. Pediatrics. 1985;75(3):469-76.
Litovitz T, Whitaker N, Clark L. Preventing Battery Ingestions: An Analysis of 8648 Cases. Pediatrics. 2010;125(6):1178-1183.
Litovitz T, Whitaker N, Clark L, White N, Marsolek M. Emerging battery-ingestion hazard: Clinical implications. Pediatrics. 2010;125(6):1168-1177.
Luttrell JB, Bennett SD, Bose S. What's inside a battery? An unusual caustic ingestion in an infant. Clin Pediatr (Phila). 2021;60(7-8):355-358.
Luttrell H, Bennett WE, Bose P. What’s Inside of a AA Battery? An Unusual Caustic Ingestion in an Infant. JPGN Reports. 2021;2.
Mallon P, White J, Thompson RL. Absorption of lithium following ingestion of a lithium button battery. Hum Exp Toxicol. 2004;23(4):193-195.
Marom T, Goldfarb A, Russo E, Roth Y. Battery ingestion in children. Int J Pediatr Otorhinolaryngol. 2010;74(8):849-54.
Maves MD, Carithers JS, Birck HG. Esophageal burns secondary to disc battery ingestion. Ann Otol Rhinol Laryngol. 1984;93(4):364-369.
Maraqa L, Sharma A, Sargsyan D, Rios-Diaz AJ, Reiter M, Tandon R. Your pocket burns: an occupational hazard from an e-cigarette lithium battery explosion. Burns. 2018;44(4):912-914.
Nnorom IC, Osibanjo O. Heavy metal characterization of waste portable rechargeable batteries used in mobile phones. Int J Environ Sci Technol. 2009;6(4):641-650.
Nogueira C, Margarido F. Leaching behaviour of electrode materials of spent nickel–cadmium batteries in sulphuric acid media. Hydrometallurgy. 2004;72(1-2):111-118.
Păduraru G, Nichita A, Filip F, Tătăranu E, Diaconescu S. Accidental ingestion of cylindrical batteries in children – interventional or conservative management? Rom J Pediatr. 2021.
Peng F, Lu J, Zhao Y, Wu L, Shen H, Zhang T. Investigation of toxic hazards of lithium-ion batteries. J Power Sources. 2020;448:227-234.
Rebhandl W, Pomberger R, Hasenboehler EA, Schemper M, Vécsei V. Release of metals from button batteries retained in the stomach: An in vitro study. J Pediatr Surg. 2002;37(6):855-859.
Rosenfeld EH, Sola R, Yu YR, St. Peter SS, Shah SR. Battery ingestions in children: Variations in care and development of a clinical algorithm. J Pediatr Surg. 2018;53(8):1537-1541.
Singh S, Gupta R, Kumar V, et al. Injury of sodium ingestion. Int J Clin Pediatr Dent. 2014;7(1):46-49.
Tanaka J, Yamashita M, Yamashita M, Aoyama K. Electrochemical study of lithium deposition and dissolution in aprotic organic solvents. Electrochim Acta. 1998;43(7):915-920.
Tzanetakis N, Scott K. Recycling of nickel–metal hydride batteries. I: Dissolution and solvent extraction of metals. J Chem Technol Biotechnol. 2004;79(9):919-926.
Voelker J, Buchanan P, Dickerson L, Holt M, Saad J, Krahn L. Harm from lithium button battery aspiration: an in vitro study. J Emerg Med. 2020;58(6):883-888.
Park Y, Kim M, Kim HS, Lee B. Risk assessment of lithium-ion battery explosion: chemical leakages. J Toxicol Environ Health B Crit Rev. 2018;21(7):370-381.
Safi AF, Ali SP, Habibi M, Rostami N. Endoscopic removal of esophageal foreign bodies: a retrospective study. Clin Endosc. 2017;50(5):420-426.
Laugel V, Meyer P, Leclair MD, Vial C. Management of esophageal button battery ingestion in children: a report of two cases with unusual complications. J Pediatr Surg. 1999;34(11):1640-1642.
Zipursky, A. R., & Ratnapalan, S. (2021). Button battery ingestions in children. Canadian Medical Association Journal, 193(37), E1468-E1474. DOI: 10.1503/cmaj.202666.
Keep reading