Acute Radiation Syndrome (ARS)
Published on 10 Oct 2025 · Updated 16 Nov 2026

Published on 10 Oct 2025 · Updated 16 Nov 2026
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/guidelines/acute-radiation-syndrome-ars-clinical-guideline
Clinical Guideline | Emergency Department, Inpatient, Hematology, and Radiation Medicine
Evidence revision: November 15, 2026
Clinical manuscript: Omid Mehrpour, MD, FACMT
Acute radiation syndrome (ARS) is an acute illness after sufficiently high, rapidly delivered, penetrating ionizing radiation exposure affecting the whole body or a substantial fraction of it. Classic ARS has been described after short-duration exposures generally above 0.7 Gy; milder manifestations may occur below that level. Localized cutaneous radiation injury and internal radionuclide contamination can occur with or without systemic ARS. Clinical management requires immediate resuscitation, differentiation of irradiation from contamination, serial hematologic evaluation, and early radiation-specialist involvement. [1], [2]
Clinical warning
Immediate Safety Warnings
Do not delay life-saving airway, circulatory, trauma, burn, or hemorrhage care for radiation survey, decontamination, dose reconstruction, cytogenetic testing, or consultant response.
Initial well appearance, absence of vomiting, or a normal first blood count does not exclude clinically important exposure.
External irradiation alone does not make the patient radioactive. Use contamination precautions only when radioactive material is suspected or confirmed.
Nonuniform, partial-body, mixed neutron, and protracted exposures complicate standard dose and ALC-based estimates.
Both Ca-DTPA and Zn-DTPA carry boxed warnings involving nebulized asthma exacerbation and trace-metal depletion. [3], [4]
Radioiodine thyroid blockade, decorporation with Prussian blue, and DTPA chelation are nuclide-specific interventions; they are not treatments for external irradiation or ARS itself.
Resuscitate first: ABCs, hemorrhage control, trauma/burn care, and shock management take precedence over radiation surveys or decontamination.
Separate irradiation from contamination. A patient irradiated by an external source is not automatically radioactive; decontaminate only when radioactive material is suspected or confirmed.
Staff safety: irradiation alone does not make a patient radioactive. For low-level contamination in controlled post-decontamination areas, standard precautions generally protect staff; coordinate PPE, surveys and personal dosimetry with the RSO when contamination is suspected. [5], [6]
Document exact exposure chronology and serial CBC with differential/absolute lymphocyte count (ALC); promptly involve radiation specialists and send cytogenetic biodosimetry where indicated.
Do not use time-to-emesis, a single ALC, or an estimated Gy value alone to decide futility or disposition. Reassess longitudinally.
For likely myelosuppressive whole-/large-part-body exposure (>2 Gy), discuss early FDA-approved H-ARS countermeasures; do not wait for ANC nadir or dicentric results if indication is clinically compelling.
KI, Prussian blue, and Ca/Zn-DTPA treat selected radionuclide contamination; they do not reverse external irradiation or treat ARS itself.
Mass-casualty crisis standards differ from individual-patient care. Comfort-focused allocation cannot be determined from a single estimated dose threshold.
Acute radiation syndrome is an acute illness following sufficiently high, rapidly delivered, penetrating ionizing-radiation exposure of the whole body or a substantial fraction of the body. CDC describes classic ARS after short-duration exposure generally above 0.7 Gy; milder manifestations may occur at lower doses. Localized cutaneous radiation injury (CRI) and internal contamination may occur with or without ARS. [1], [2]
Evidence labels used in this document: [FDA-ARS Animal Rule] = U.S.-approved H-ARS indication supported by adequate animal efficacy studies and extrapolation; [FDA label] = labeled dosing/indication or warning; [Consensus/REMM] = expert operational guidance; [Crisis standard] = scarcity-dependent mass-casualty guidance, not routine care. Labels describe provenance, not a universal evidence-quality score.
Radiation / pathway | Clinical significance | Management emphasis |
|---|---|---|
Gamma / high-energy X-rays | Deeply penetrating; high acute whole-body dose may produce classical ARS. | Reconstruct time, geometry, dose and ALC; no decon if irradiation only. |
Neutrons / mixed gamma + neutron | High relative biologic effectiveness; radiation weighting differs from photons. | Request specialist physical dosimetry; do not convert Gy to Sv as a clinical ARS shortcut. |
Beta particles | Surface/eye injury and local contamination often predominate; skin injury may be delayed. | Local wound/eye assessment, skin dose, survey and decon when indicated. |
Alpha particles | Limited external penetration, but potentially serious internal deposition. | Identify inhalation/ingestion/wound route; radionuclide-specific bioassay and therapy. |
External / internal contamination | Material on body, clothing or within body; may coexist with irradiation. | Isolation of radioactive material, survey, decon, sampling and isotope-specific mitigation. |
Clinical dose units: Gray (Gy) = absorbed energy per kilogram; Sievert (Sv) = weighted protection quantity that incorporates radiation/tissue weighting. Keep measured physical dose and organ-specific risk estimates distinct. 1 Gy = 100 rad. [1], [7], [5]
Phase / syndrome | Typical pattern | Interpretive caveat |
|---|---|---|
Prodromal | Nausea, vomiting, fatigue; diarrhea and neurologic symptoms with more severe exposure. | Timing is supportive, never diagnostic by itself. |
Latent | Patient may transiently feel well despite evolving cellular injury. | Normal symptoms early do not justify automatic discharge. |
Manifest illness | Hematopoietic: cytopenias/infection/bleeding; GI: fluid loss, mucosal damage, sepsis; neurovascular: severe neurologic/circulatory effects. | Overlapping injury patterns and combined trauma influence prognosis. |
Recovery / late sequelae | Marrow recovery or prolonged cytopenia, skin injury, thyroid risk, psychosocial consequences. | Long-term follow-up can be necessary even when ARS resolves. |
Approximate CDC ranges for rapid, extensive whole-body exposure: hematopoietic syndrome is most relevant from approximately 0.7–10 Gy; severe GI syndrome usually >10 Gy (some GI manifestations at ~6 Gy); full cardiovascular/CNS syndrome usually >50 Gy (some features at ~20 Gy). These ranges are descriptive, not individual triage or futility cutoffs. [1], [2]
Gate | Action | Escalation / next step |
|---|---|---|
1. RESUSCITATE | ABCs, vital signs, glucose as appropriate, vascular access; treat trauma, burn, airway compromise and shock immediately. | Activate ED incident command/RSO and radiation medicine / REAC/TS. |
2. CONTAMINATION? | Ask whether radioactive material is on/in the patient. External irradiation alone is not radioactive contamination. | If NO: ARS assessment only. If YES/uncertain: PPE, contamination-control zone, survey if available. |
3. DECONTAMINATE if indicated | Remove contaminated outer clothing (can remove up to ~90% of external material); bag/label; cover wounds; gentle soap-and-water washing without abrasion. | Re-survey with trained staff; record instrument, background, geometry and site-specific measurements. |
4. INTERNAL UPTAKE? | Consider inhalation, ingestion, wound contamination, fragments. Obtain radionuclide identification and targeted urine/bioassay. | Nasal swabs per nostril early if indicated; limited utility >1 h; consult health physics. |
5. SYSTEMIC INJURY? | Record onset of vomiting and other symptoms; collect initial CBC/differential, platelets, electrolytes, organ injury tests, pregnancy test where relevant. | Repeat CBC for ALC kinetics and arrange reference-laboratory biodosimetry; specialist-guided disposition. |
The separate contamination and exposure pathways must be maintained in any site graphic or quick card. Survey/decon never supersedes essential treatment. [7], [5], [8]
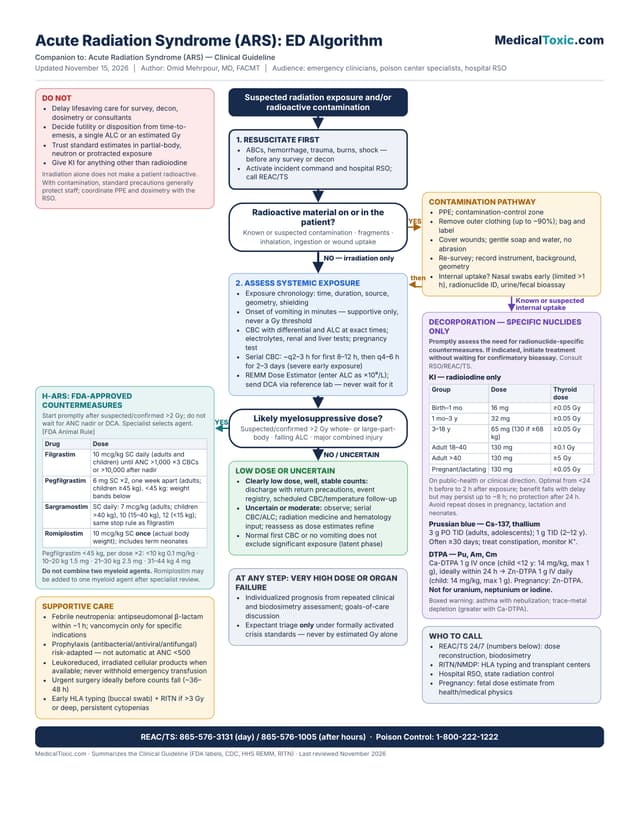
Clinician Order Set — Initial Evaluation
CBC/differential with explicit ALC, ANC and platelets, with exact collection times relative to exposure; chemistry, Mg/Phos, renal/hepatic tests and lactate as clinically indicated; type and screen, and HLA typing where severe marrow failure/HCT is a concern (ideally before transfusion if feasible).
Document exact onset and frequency of emesis/diarrhea, fever, neurologic changes, skin erythema, burns and trauma; serial weight, intake/output, photographs of cutaneous findings, and all exposure reconstruction details.
If febrile neutropenia or another infection is suspected, obtain cultures when feasible before antibiotics without delaying empiric therapy; do not routinely order blood cultures for every asymptomatic exposure.
For contaminated patients, trained health physics personnel document contamination pattern and source, survey setup and instrument, radionuclide identity, and sample chain of custody.
For suspected severe early whole-body exposure, CDC recommends CBC/differential approximately every 2–3 hours during the first 8–12 hours after exposure, then every 4–6 hours for the following 2–3 days when appropriate. REMM also provides a less resource-intensive small-event schedule (three CBCs/day for 2–3 days, then twice/day for 3–6 days). Choose one context-appropriate schedule with radiation-medicine guidance rather than combining them into a universal order. [1], [9]
Serial ALC decline supports dose estimation but is affected by nonuniform exposure, sampling time, concomitant illness/trauma and baseline status. An ALC <100/µL near 48 hours indicates profound injury but does not establish a unique absorbed dose or independently determine prognosis. Interpret with established depletion curves, clinical findings and physical/cytogenetic dosimetry. [2], [9]
Bedside decision support: use the interactive REMM Dose Estimator (time-to-emesis, lymphocyte-depletion kinetics, and DCA); see the Andrews nomogram in the CDC ARS clinician guidance. Enter ALC in the units required by the tool (×10⁹ cells/L), not unconverted cells/µL. Model outputs are estimates with uncertainty, not definitive triage thresholds. [1], [10]
Early vomiting has a historical association with higher dose (e.g., onset within 1 hour may suggest major exposure), but stress, trauma, medicines and other causes substantially reduce specificity. Do not translate <30 minutes or <1 hour into a definitive Gy threshold or use absence of vomiting to exclude ARS. Record onset in minutes and use only as one input to reassessment. [11]
Arrange peripheral blood for dicentric chromosome assay (DCA) with a reference laboratory; coordinate collection timing, handling, sampling and chain of custody. Triage scoring may begin with ~20–50 metaphases during mass-casualty conditions; 500–1,000 cells may be used for refinement or suspected inhomogeneous exposure when available. DCA may take days; never defer urgent management solely for its result. [12]
Risk pattern | Disposition approach |
|---|---|
Clearly low dose, no concerning injury or hematologic trend | Consider discharge with return precautions, event registry entry, and scheduled CBC/temperature follow-up per public-health/radiation team. |
Uncertain or moderate exposure, declining ALC, significant symptoms | Observed ED/inpatient assessment; hematology and radiation medicine input; serial evaluation and dose refinement. |
Suspected myelosuppressive dose >2 Gy or major combined injury | Admission/transfer discussion; myeloid countermeasure eligibility, infection/bleeding support, HLA/RITN assessment where appropriate. |
Very high estimated dose, organ failure or mass casualty crisis | Individualized prognostic reassessment; goals-of-care discussion. Crisis-standard expectant triage ONLY under formally activated scarcity processes; not by Gy alone. |
Early treatment gate: In clinically credible suspected or confirmed myelosuppressive radiation exposure generally >2 Gy, obtain CBC if feasible but do not delay appropriate countermeasures while awaiting DCA or ANC decline. A specialist selects the agent(s); availability, formulation, supply and adverse-effect risks matter. [13], [14], [15], [16], [17]
Drug / evidence | Adult / older child dose | Pediatric dose | Course / key caution |
|---|---|---|---|
Filgrastim (Neupogen) [FDA-ARS Animal Rule] | 10 mcg/kg SC once daily | 10 mcg/kg SC once daily | Start promptly after suspected/confirmed >2 Gy. Continue until ANC >1,000/mm³ for 3 consecutive CBCs OR >10,000/mm³ after radiation nadir. [14] |
Pegfilgrastim (Neulasta) [FDA-ARS Animal Rule] | 6 mg SC, 2 doses 7 days apart (all adult weights) | ≥45 kg: 6 mg ×2, 7 days apart; <45 kg: weight-band table below | Not “once until ANC recovers.” Give first dose promptly after suspected/confirmed >2 Gy. [15] |
Sargramostim (Leukine) [FDA-ARS Animal Rule] | 7 mcg/kg SC daily (adults; children >40 kg) | Children >40 kg: 7; 15–40 kg: 10; <15 kg: 12 mcg/kg SC daily | Continue until ANC >1,000/mm³ for 3 consecutive CBCs OR >10,000/mm³ after nadir. Check formulation and benzyl alcohol precautions. [16] |
Romiplostim (Nplate) [FDA-ARS Animal Rule] | 10 mcg/kg SC once | 10 mcg/kg SC once; includes term neonates | Single H-ARS dose; calculate 10 mcg/kg using the patient’s measured actual body weight (kg). Do not use ITP dose titration. Adjunctive use alongside a myeloid agent requires specialist assessment. [17] |
Weight | Dose per injection | Schedule |
|---|---|---|
<10 kg | 0.1 mg/kg | Two doses, one week apart |
10–20 kg | 1.5 mg | Two doses, one week apart |
21–30 kg | 2.5 mg | Two doses, one week apart |
31–44 kg | 4 mg | Two doses, one week apart |
≥45 kg | 6 mg | Two doses, one week apart |
Drug evidence context: randomized human efficacy trials in H-ARS are not feasible. FDA H-ARS indications largely rely on Animal Rule efficacy with human PK/safety bridging. No default superiority of filgrastim is established. Select the myeloid agent and dosing regimen under an expert protocol; do not routinely combine two myeloid cytokines (e.g., filgrastim with sargramostim or pegfilgrastim). Romiplostim targets the megakaryocytic/platelet axis and may be considered in addition to a myeloid agent after specialist assessment; the additive clinical survival benefit of combinations in humans with ARS is unproven. [13], [14], [15], [16], [17]
Sargramostim timing evidence: the pivotal nonhuman-primate survival study initiated treatment at 48 ± 1 hours after irradiation. In a separate nonhuman-primate delayed-start study, survival benefit was observed when therapy began as late as 96 hours; hematologic improvement was reported with starts up to 120 hours. These animal data do not set a validated deadline for human benefit. Begin indicated therapy promptly rather than withholding it solely because presentation is delayed. [16], [18]
Crisis-standard note: REMM discusses altered dosing or allocation if supplies are constrained after a nuclear detonation. Such contingency recommendations are separate from FDA-labeled treatment and must not silently replace routine doses. [13], [19]
Monitor ANC, platelets, signs of mucositis, hemodynamics, skin integrity and fever. Use local neutropenic-infection pathways and protective precautions appropriate to degree/duration of immunosuppression.
Febrile neutropenia: promptly administer an empiric antipseudomonal beta-lactam (e.g., cefepime, piperacillin-tazobactam or meropenem), selected for allergies, renal function and local resistance. Aim for rapid administration (generally within ~1 hour of recognition).
Do not add vancomycin routinely; reserve for indications such as suspected catheter/skin infection, pneumonia, hemodynamic instability or resistant Gram-positive concern. Reassess daily; individualize duration and de-escalation.
Risk-adapted prophylaxis: consider antibacterial, antiviral and antifungal prophylaxis for selected patients expected to develop profound/prolonged neutropenia, depending on mucosal injury, infection risk, transplantation plans and local antimicrobial stewardship. ANC <500/µL alone is not an automatic prescription for all three classes.
All infection decisions are [Consensus/REMM] and should be co-managed with infectious diseases and hematology; chemotherapy-derived neutropenic guidelines are supporting analogs rather than directly validated radiation-only thresholds. [2], [20]
Provide resuscitation fluids, balanced electrolyte repletion, antiemetics (ondansetron first-line), nutrition and pain control. Evaluate persistent diarrhea and fluid loss; antimotility therapy only when clinically appropriate and infection/ileus has been assessed.
Individualize transfusion thresholds to bleeding, procedures and comorbidity. Significant immunosuppression from ARS favors leukoreduced and irradiated cellular blood components when available. Emergency life-saving transfusion must not be withheld solely due to product unavailability.
Time nonessential procedures around anticipated cytopenias. When urgent surgery is indicated after major exposure, early intervention may be advantageous before blood counts fall (often within 36–48 hours), but this is not an immutable timing rule.
Evidence: [Consensus/REMM]. [2], [21]
Consider early HLA typing, marrow-failure assessment and RITN consultation for selected high-risk patients (e.g., estimated whole-body dose >3 Gy, deep persistent cytopenias, rapid platelet decline, reasonable chance of surviving nonhematologic injury). Buccal-swab DNA HLA typing is feasible; do not require preserved lymphocyte counts. HCT is uncommon in ARS and is NOT triggered automatically by a 14- or 21-day clock. Reassess autologous marrow recovery, extent of GI/neurovascular injury, donor availability and patient-specific prognosis. [22]
Examine and photograph early, but warn that erythema, epilation, desquamation, ulceration and necrosis may be delayed days to weeks. Dose depth, radiation type, exposed surface and geometry govern injury. Use analgesia, gentle local care, nonadherent dressings, infection surveillance and early dermatology/burn/plastic-surgery involvement when extensive. Avoid routine aggressive debridement without multidisciplinary assessment. [2], [23]
These countermeasures target a specific nuclide/pathway and are not a treatment for pure external irradiation. Establish isotope, route and likely uptake; consult RSO, REAC/TS or internal-dosimetry specialists early. [7], [24], [25]
Countermeasure selection: When internal contamination is known or strongly suspected, promptly assess the need for a radionuclide-specific countermeasure using the source, exposure pathway, credible dose/burden and clinical context. If indicated, start KI for radioiodine, Prussian blue for cesium/thallium, or Ca/Zn-DTPA for Pu/Am/Cm without waiting for confirmatory bioassay; obtain baseline measurements when feasible without delaying time-sensitive treatment. Do not administer all agents empirically for an unidentified radionuclide. Coordinate with the hospital RSO/health physics and REAC/TS. [7], [24], [25], [3], [4]
KI blocks thyroid uptake of radioiodine only when indicated for projected thyroid exposure and directed by public-health/radiation authorities; it does not prevent or treat ARS or protect against other radionuclides. The WHO optimal administration window is less than 24 hours before to 2 hours after the expected onset of radioiodine exposure; benefit declines with delay but administration may still be reasonable up to approximately 8 hours afterward. CDC emphasizes greatest effectiveness within 24 hours before or 4 hours after exposure. Administration later than 24 hours after exposure offers no protection. Do not delay evacuation or sheltering to obtain KI. [24], [26], [27], [28], [29]
Risk group | KI dose (as potassium iodide) | Projected thyroid exposure trigger* |
|---|---|---|
Birth–1 month | 16 mg PO | ≥0.05 Gy thyroid |
>1 month–3 years | 32 mg PO | ≥0.05 Gy thyroid |
>3–12 years | 65 mg PO | ≥0.05 Gy thyroid |
>12–18 years | 65 mg PO; 130 mg if ≥68 kg (150 lb) | ≥0.05 Gy thyroid |
Adults 18–40 years | 130 mg PO | ≥0.1 Gy thyroid |
Adults >40 years | 130 mg PO | ≥5 Gy thyroid |
Pregnant / lactating | 130 mg PO | ≥0.05 Gy thyroid |
Thresholds are projected thyroid absorbed dose from radioiodine (not external whole-body dose). FDA uses thresholds ≥0.05, ≥0.1 and ≥5 Gy according to risk group. A single KI dose protects for approximately 24 hours; additional dosing requires public-health direction. Pregnant/lactating patients and neonates should generally avoid repeated doses if alternative protection is feasible; infants need thyroid-function follow-up after KI. [24], [26]
Contraindications/major cautions include prior serious KI hypersensitivity, dermatitis herpetiformis, hypocomplementemic vasculitis, and nodular thyroid disease with heart disease. Benefits in extreme incidents require individualized benefit-risk assessment. Contrast-media “iodine allergy” is not a stand-alone basis for prohibiting KI. [24], [26]
Group | Dose | Monitoring / duration |
|---|---|---|
Adults and adolescents | 3 g orally three times daily (9 g/day) | Start promptly when Cs or Tl intake is suspected. Course may last 30 days or longer; isotope-specific urine/fecal monitoring guides duration. |
Children 2–12 years | 1 g orally three times daily (3 g/day) | Manage constipation, monitor electrolytes (including potassium) and elimination. |
Children <2 years | Labeled safety/efficacy not established | Radiation-medicine/pediatric expert decision required. |
Pregnancy | Weigh internal contamination risks; specialist decision | GI absorption is minimal; human pregnancy evidence limited. |
When clinically indicated for known or suspected internal cesium/thallium contamination, initiate insoluble Prussian blue as soon as feasible; collect baseline whole-body measurements or bioassay when available without delaying treatment. Delayed initiation may still confer benefit. Radiogardase can slow gastrointestinal motility and prolong residence of radioactive cesium or thallium within the gastrointestinal tract, potentially increasing radiation absorbed dose to the GI mucosa. Monitor for and treat constipation, assess transit, and monitor electrolytes. [25]
Agent / indication | Adult or adolescent IV dose | Pediatric IV (<12 y) | Sequence / limitations |
|---|---|---|---|
Ca-DTPA: known/suspected internal Pu/Am/Cm | 1 g IV ONCE initially, ideally in first 24 hours | 14 mg/kg IV once (max 1 g) | Usually first agent if available early; switch to Zn-DTPA for subsequent daily chelation. Consider benefit even after delay. [3] |
Zn-DTPA: known/suspected internal Pu/Am/Cm | 1 g IV initially if Ca unavailable; then 1 g IV once daily if ongoing chelation indicated | 14 mg/kg IV (max 1 g) initially/daily as appropriate | Preferred continuation after first day; choice depends on isotope/body burden and specialist evaluation. [4] |
FDA BOXED WARNING for both Ca-DTPA and Zn-DTPA: asthma exacerbation with nebulization and depletion of essential trace metals. Ca-DTPA generally produces greater zinc depletion than Zn-DTPA; also monitor magnesium, manganese and other electrolytes as indicated. Monitor CBC, BUN/creatinine, urinalysis, and radionuclide bioassay, and supplement deficiencies under specialist guidance. [3], [4]
Important nuclide exclusion: Ca-DTPA and Zn-DTPA are indicated for internal contamination with plutonium, americium or curium; neither is expected to be effective for uranium or neptunium. DTPA does not chelate radioactive iodine. Select a chelator based on a credible radionuclide-specific exposure scenario; request confirmation and bioassay, but do not delay indicated treatment solely for laboratory identification. [3], [4]
Route distinction: IV is recommended if the uptake pathway is unknown or multiple (including wounds). Ca-DTPA nebulization is an alternative for inhalation-only intake in the previous 24 hours; Zn-DTPA nebulization is an alternative for inhalation-only intake without that explicit 24-hour limit in its label. For either agent, dilute the labeled 1-g/5-mL solution 1:1 with sterile water or saline before nebulization. Instruct patients not to swallow expectorated material. Nebulized use is not established as safe/effective in children and can provoke respiratory adverse events. In pregnancy, Zn-DTPA is generally preferred when chelation is indicated; Ca-DTPA needs exceptional benefit-risk justification. [3], [4]
Follow-up: use radionuclide-specific bioassay (spot/24-hour urine, fecal samples, whole-body/organ counting as appropriate) and elimination trends under internal-dosimetry guidance. Do not apply one daily×3–5 then weekly sample schedule to every nuclide. [7], [3], [4]
Obtain pediatric radiation-medicine input early; children have differing susceptibility and require exact product-specific dose and concentration checks, particularly KI and pegfilgrastim weight bands.
In suspected inhalation contamination, separately collected nasal swabs in the first hour can contribute to assessment but are unreliable after delays and never substitute for bioassay. The yield and logistics vary in mass casualties.
Pregnancy does not remove indication for maternal stabilization. For radioactive iodine use KI only per projected-thyroid-dose/public-health criteria; minimize repeat dosing. For transuranic uptake, Zn-DTPA is preferred when chelation warranted. For Cs/Tl consider Prussian blue with specialist input.
For a pregnant patient with suspected significant irradiation or radionuclide uptake, urgently request an individualized fetal absorbed-dose estimate from health physics/medical physics, considering both external maternal exposure and internal maternal/fetal uptake, and interpret it by gestational age. Do not infer fetal dose from the maternal whole-body dose alone. Coordinate counseling with maternal–fetal medicine and radiation specialists. [30]
In lactation/internal contamination, investigate whether breastfeeding should be interrupted based on the isotope and formal label/health-physics advice, rather than issuing a generic one-size-fits-all duration.
Treat injury first. Cover wounds for initial skin decon and have RSO identify fragments; remove radioactive shrapnel safely when clinically feasible. Collect and label wound material as indicated. Irradiation plus trauma/burn may worsen survival, and infection management and surgery timing may differ from isolated injury. [7], [5], [21]
A very high estimated short-duration whole-body dose (e.g., approximately ≥10 Gy) is associated with extremely poor prognosis if severe GI and combined-organ injury is present. Nevertheless, estimated dose alone must not establish futility in individual care, particularly where exposure is heterogeneous, partially shielded or protracted. Goals-of-care discussions may be appropriate based on repeated clinical and biodosimetry assessments. [1], [2], [19]
In a declared mass-casualty setting with critical scarcity, REMM describes separate Immediate/Delayed/Minimal/Expectant allocation categories; some >10 Gy cases remain potentially appropriate for aggressive treatment depending on circumstances. These are [Crisis standard] recommendations and should be activated through incident command/ethics/public-health policy, not silently applied to routine ED arrivals. [19]
Use combined clinical syndrome severity, serial hematology, physical reconstruction and DCA to determine discharge/admission/transfer; register incident details according to policy.
Give returning patients clear triggers for reassessment: fever, persistent emesis/diarrhea, bleeding, weakness/syncope, erythema/skin lesions and neurologic changes; organize repeat CBC when at risk.
Arrange longitudinal hematologic, skin, endocrine/thyroid (when relevant), psychosocial and malignancy-risk counseling through appropriate specialists.
Contact | Route | What to request |
|---|---|---|
REAC/TS (daytime) | 865-576-3131 | Radiation medicine advice; coordinate specialty consultation and biodosimetry. |
REAC/TS after hours / weekends | 865-576-1005; ask for REAC/TS | DOE/Oak Ridge emergency route; radiation consultation. |
RITN / NMDP | 1-800-MARROW-2 or 612-627-5800 | HLA typing and potential marrow support / RITN center location. |
Local Hospital RSO / State radiation control | Institution-specific contact | Survey, contamination management, isotope identification, physical dosimetry, regulatory reporting. |
Poison Control (U.S.) | 1-800-222-1222 | Toxicologic consultation and coordination as available. |
REAC/TS numbers were checked against HHS REMM and the NMDP/RITN HLA-typing contact numbers against the current RITN Treatment page (reviewed 15 Nov 2026). Confirm local emergency routing before operational deployment. [31], [32]
Recommendation | Evidence basis | Confidence / limitation |
|---|---|---|
Early filgrastim, pegfilgrastim, sargramostim, romiplostim after likely >2 Gy | FDA-ARS Animal Rule drug labels | Approved indications; no human randomized ARS head-to-head comparative outcomes. |
CBC/ALC kinetics, DCA, contamination separation | CDC + HHS REMM clinical guidance | Established operational practice; timing varies by event and resource availability. |
KI, Prussian blue, Ca/Zn-DTPA | FDA guidance/labels; radionuclide specificity | Pharmacologic efficacy depends on isotope, source, time, internal dose and administration. |
HLA typing, RITN and possible HCT | RITN/REMM consensus | HCT exceptional, not routine; case-by-case balance. |
Expectant triage under crisis conditions | REMM crisis-standard tool | Restricted to formally resource-limited event settings; ethical incident command required. |
For an educational overview complementary to this bedside Guideline, see Acute Radiation Poisoning: Essential Guide for Emergency Clinicians.