Public Health and Poison Prevention
At-Home Ketamine Therapy: Evidence, Risks, and Safety
Omid Mehrpour
Post on 28 May 2024 · Updated 03 Nov 2026 · 16 min read

Omid Mehrpour
Post on 28 May 2024 · Updated 03 Nov 2026 · 16 min read
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/blogs/at-home-ketamine-therapy-evidence-risks-safety

At-home ketamine therapy has expanded rapidly through telehealth programs offering compounded oral, sublingual, and, more recently, other formulations for psychiatric conditions such as depression, anxiety, and post-traumatic stress disorder (PTSD).
The appeal is understandable. Ketamine can produce rapid antidepressant effects in selected patients, while remote treatment may reduce travel, cost, and access barriers.
But at-home ketamine also creates a different safety environment from treatment in a monitored clinic.
The U.S. Food and Drug Administration (FDA) has specifically warned about compounded ketamine products used for psychiatric conditions outside healthcare settings. Racemic ketamine is not FDA-approved for depression, anxiety, PTSD, or any other psychiatric disorder, and compounded ketamine products are themselves not FDA-approved for safety, effectiveness, quality, dose, or route of administration. [1]
At the same time, emerging observational studies suggest that carefully selected patients participating in structured telehealth programs can experience meaningful improvements in depression and anxiety symptoms.
The evidence therefore supports neither extreme:
At-home ketamine should not be dismissed as inherently unsafe, but current evidence is not strong enough to treat remote ketamine therapy as equivalent to an established, standardized, FDA-approved psychiatric treatment.
Racemic ketamine is FDA-approved as an anesthetic, not as a psychiatric treatment.
Compounded oral, sublingual, or nasal ketamine products are not FDA-approved.
At-home telehealth studies have reported substantial symptom improvement in selected patients.
The strongest 2026 systematic review rated the evidence for effectiveness and safety as very low certainty.
Most published at-home evidence comes from commercial-provider programs and lacks randomized control groups.
Important acute risks include sedation, dissociation, blood-pressure changes, psychiatric effects, and respiratory depression.
Repeated ketamine exposure can also be associated with misuse, dependence, urinary tract injury, and hepatobiliary complications.
Alcohol, opioids, benzodiazepines, and other CNS depressants can increase sedation and respiratory risk.
FDA-approved esketamine (Spravato) is not an at-home treatment; it must be administered in a certified healthcare setting with monitoring.
A safer telehealth model depends on careful patient selection, monitoring, follow-up, emergency planning, and avoidance of unsupervised self-escalation.
Ketamine is a dissociative anesthetic and N-methyl-D-aspartate (NMDA) receptor antagonist.
FDA-approved injectable ketamine has been used for decades for induction and maintenance of anesthesia. Its psychiatric use developed later after clinical studies showed that subanesthetic ketamine can produce rapid antidepressant effects in some patients.
The antidepressant mechanism is more complex than simple NMDA blockade. Ketamine influences glutamatergic signaling, AMPA-receptor activity, synaptic plasticity, and downstream pathways involved in neural adaptation.
However, a drug can have a biologically plausible and clinically useful effect while still requiring careful control of dose, route, patient selection, and monitoring.
That distinction becomes especially important when treatment moves from a clinical environment into a patient's home.
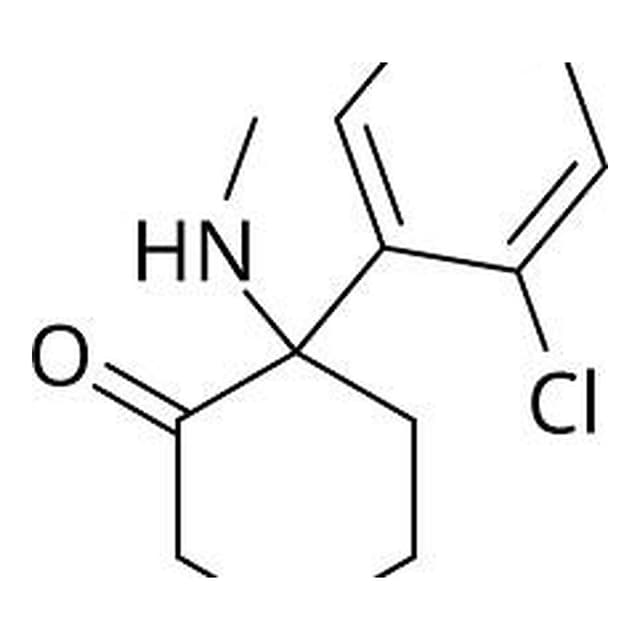
There is no single standardized at-home ketamine model.
Programs may differ in:
route of administration;
compounded formulation;
frequency of dosing;
clinician involvement;
psychotherapy or integration support;
physiological monitoring;
presence of another adult during treatment;
follow-up requirements;
emergency procedures.
Much of the published U.S. evidence has involved compounded sublingual racemic ketamine prescribed through telehealth.
More recently, at-home subcutaneous ketamine has also been studied.
These models should not be treated as interchangeable.
Oral, sublingual, intranasal, intravenous, intramuscular, and subcutaneous ketamine have different pharmacokinetic properties and cannot simply be assumed to have equivalent efficacy or risk.
A 2026 systematic review specifically evaluated telehealth-supported ketamine for depression and anxiety.
Only three studies met the review criteria. All came from U.S. commercial providers. Across studies, reported response rates were approximately 49.5%–62.8% for depression and 47.6%–62.9% for anxiety, with remission rates around 20.7%–32.6% and 23.9%–31.3%, respectively. [2]
Those numbers sound encouraging.
The methodological assessment is equally important.
The reviewers rated all three studies at critical overall risk of bias and judged the certainty of evidence for both effectiveness and safety to be very low. Follow-up outcome data were also available for only a subset of the much larger enrolled populations. [2]
The correct interpretation is therefore:
Telehealth-supported ketamine is associated with symptom improvement in selected patients, but the current evidence does not establish high-certainty comparative effectiveness or long-term safety.

A 2024 longitudinal study analyzed 11,441 patients receiving four at-home telehealth-supported sublingual ketamine sessions over four weeks.
Depression scores improved substantially in many participants, and reported adverse events occurred in approximately 3.0%–4.8% of patients, predominantly involving neurologic or psychiatric symptoms. [3]
However, the study had important limitations:
no randomized control group;
no comparison group;
no fixed-dose procedure;
real-world rather than controlled-trial design.
The study also used data from a commercial telehealth service. One author was an employee of the provider and another reported consulting fees from the company. [3]
These conflicts do not invalidate the findings.
They do make independent replication particularly important.
A July 2026 retrospective cohort study evaluated at-home, telehealth-supported subcutaneous ketamine in 3,870 patients across 38 U.S. states.
The program used clinical assessment, remote physiological screening, blood-pressure monitoring, clinician-guided treatment, and mandatory peer monitoring.
After six sessions, depression, anxiety, and PTSD symptom scores declined substantially among evaluated patients. Adverse events were reported in approximately 2.8%–3.2%, and the investigators reported no serious complications attributable to the subcutaneous administration protocol. [4]
This is important new evidence, but it remains observational.
The study used a convenience sample rather than randomization, and several authors were employees or paid contractors of the commercial ketamine provider whose clinical data were analyzed. [4]
It therefore supports feasibility under a structured program, not a conclusion that unsupervised at-home ketamine is generally safe.
Evidence | Main finding | Key limitation |
|---|---|---|
2026 systematic review | Symptom improvement across telehealth programs | All included studies at critical risk of bias; very low certainty |
2024 sublingual cohort | Improvement in 11,441 patients; adverse events 3.0%–4.8% | No control group; variable dosing |
2026 subcutaneous cohort | Improvement in depression, anxiety, and PTSD; adverse events 2.8%–3.2% | Retrospective convenience sample; provider-linked authors |
FDA safety warning | Serious concerns with unmonitored compounded ketamine | Regulatory safety signal, not comparative efficacy evidence |
The strongest overall message is that structured remote care is not the same thing as unsupervised use.
Racemic ketamine is not FDA-approved for depression.
FDA-approved ketamine hydrochloride injection is indicated for anesthesia. [5]
Using racemic ketamine for depression, anxiety, PTSD, or another psychiatric disorder is therefore off-label.
Off-label prescribing is not inherently inappropriate. Clinicians commonly prescribe FDA-approved drugs for indications outside the formal label when supported by clinical judgment and evidence.
The important distinction is that FDA has not independently established an approved psychiatric dose, route, treatment schedule, monitoring protocol, or benefit-risk profile for racemic ketamine.
Compounded products introduce an additional distinction: compounded ketamine formulations themselves have not undergone FDA premarket approval for safety, effectiveness, manufacturing quality, or psychiatric use. [1]
This distinction causes frequent confusion.
Ketamine is a racemic mixture containing both R-ketamine and S-ketamine.
Esketamine is the S-enantiomer.
FDA-approved esketamine is marketed as Spravato.
Current FDA labeling allows Spravato for adults with treatment-resistant depression, with or without an oral antidepressant, and for depressive symptoms in adults with major depressive disorder and acute suicidal ideation or behavior when used with an oral antidepressant. [6]
But Spravato is not mailed to patients for unsupervised home use.
Because of risks including sedation, dissociation, respiratory depression, abuse, and misuse, it is available through a Risk Evaluation and Mitigation Strategy (REMS). It can only be administered in certified healthcare settings, and patients must be monitored for at least two hours. [6]
For a broader comparison of these compounds, see Ketamine vs. Esketamine: Are These Mind-Altering Medications Safe for Treating Depression?.
The broader regulatory landscape for esketamine and other psychoactive therapies is also reviewed in Psychedelics in 2025: What’s Evidence-Based, What Isn’t, and How to Counsel Patients.
FDA's concern is not simply that ketamine can cause hallucinations.
The agency identified several clinically significant risks:
sedation;
dissociation;
psychiatric events or worsening psychiatric illness;
increased blood pressure;
respiratory depression;
abuse and misuse;
lower urinary tract and bladder symptoms. [1]
FDA specifically noted that at-home administration adds risk because an onsite healthcare professional is not present if serious sedation, dissociation, respiratory compromise, or cardiovascular effects develop.
In one reported 2023 case, a patient experienced respiratory depression after taking compounded oral ketamine outside a healthcare setting for PTSD. [1]
A single adverse-event report does not establish incidence.
It does demonstrate that serious toxicity is biologically and clinically possible.
Dissociation can include altered perception of:
self;
surroundings;
time;
body;
sensory experience.
During a therapeutic session these effects may be expected to some degree.
They can nevertheless impair judgment, balance, coordination, and the ability to respond appropriately to an emergency.
More intense exposure may lead to marked sedation, confusion, agitation, hallucinations, or loss of responsiveness.
The absence of a clinician in the room changes the practical consequences of these effects.
Ketamine commonly increases blood pressure and heart rate.
The current FDA ketamine label specifically warns about hemodynamic instability and identifies significant blood-pressure elevation as a concern in patients for whom such an increase would pose a serious hazard. [5]
That is one reason appropriate cardiovascular history and baseline assessment matter before treatment.
It does not mean that every patient with hypertension can never receive ketamine.
It means the risk must be assessed in the context of the individual's cardiovascular status and the treatment environment.
Ketamine is sometimes described as preserving breathing better than many sedatives.
That should not be translated into the claim that respiratory depression is impossible.
FDA identifies respiratory depression as a known risk of ketamine, particularly with excessive exposure or rapid administration. [5]
The risk becomes more concerning when other sedating substances are involved.
The current ketamine prescribing information warns that combining ketamine with opioids, benzodiazepines, alcohol, or other central nervous system depressants can produce profound sedation, respiratory depression, coma, or death. [5]
This makes a complete medication and substance-use history an essential part of patient assessment.
It also means that the safety of a prescribed ketamine dose cannot be evaluated in isolation from other substances being used.
Ketamine is a Schedule III controlled substance.
Its euphoric and dissociative effects create potential for nonmedical use, escalating use, and psychological dependence.
Not every patient receiving therapeutic ketamine develops problematic use.
Risk is nevertheless clinically relevant, particularly when patients:
have a history of substance-use disorder;
receive repeated supplies at home;
have access to unsupervised extra doses;
escalate frequency or amount outside the treatment plan.
Safe prescribing therefore requires more than simply confirming that ketamine improved mood.
Clinicians also need to monitor how the medication is being used.
Repeated or chronic ketamine exposure has been associated with significant urinary complications.
The current FDA label describes reports of:
cystitis;
reduced bladder capacity;
urinary frequency;
urgency;
dysuria;
hematuria;
ureteral narrowing or obstruction;
hydronephrosis. [5]
Much of the severe urinary literature comes from chronic misuse or prolonged exposure rather than brief therapeutic courses.
The risk therefore should not be presented as inevitable in psychiatric treatment.
But new urinary pain, frequency, urgency, or blood in the urine during repeated ketamine treatment should not be ignored.
Recurrent ketamine exposure has also been associated with hepatobiliary injury, including biliary abnormalities reported during repeated medical use and misuse.
The 2026 FDA ketamine label includes warnings regarding drug-induced liver injury and hepatobiliary complications with recurrent exposure. [5]
The long-term safety of repeated at-home psychiatric ketamine remains less certain than the short-term symptom-response data.
Ketamine is used to treat psychiatric illness, but it can also produce acute psychiatric effects.
Potential concerns include:
severe anxiety;
panic;
agitation;
perceptual disturbance;
worsening psychotic symptoms in vulnerable patients;
mania or behavioral activation;
suicidality requiring more intensive care.
A remote ketamine program therefore cannot rely only on a depression questionnaire.
Assessment should also consider psychiatric history, current mental state, suicide risk, substance-use history, medication use, and whether the home environment is appropriate for the treatment model.
There is a major difference between:
prescribed ketamine within a structured telehealth program
and
buying ketamine online or using it independently without medical oversight.
FDA took enforcement action in June 2026 against multiple websites offering unapproved and misbranded ketamine products to U.S. consumers.
In one warning letter, FDA specifically emphasized the risks of easy internet access to unapproved ketamine products and noted the possibility of contamination, counterfeit products, variable active ingredients, or different ingredients altogether. [7]
Online availability should not be mistaken for legitimate medical prescribing.
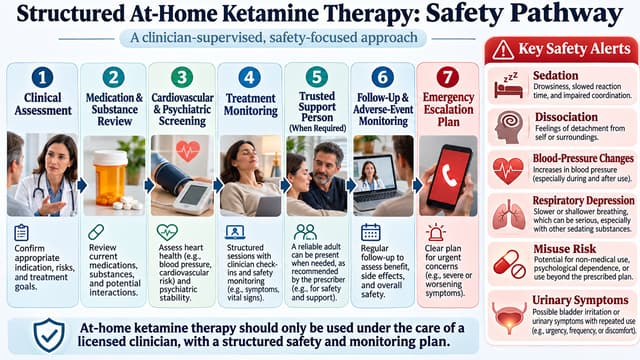
There is no FDA-approved universal at-home psychiatric ketamine protocol.
The better-studied telehealth models nevertheless share several safety features.
These may include:
clinician assessment before treatment;
review of medical and psychiatric history;
medication and substance-use screening;
cardiovascular assessment;
suicide-risk assessment;
clear treatment instructions;
defined limits on dosing and frequency;
physiological monitoring when appropriate;
another responsible adult present under some protocols;
rapid access to clinical support;
scheduled follow-up;
monitoring for misuse and adverse effects;
an emergency plan.
The 2026 subcutaneous study, for example, used clinical assessment, remote physiological screening, home blood-pressure monitoring, mandatory peer monitoring, and clinician-guided treatment. [4]
Those safeguards are part of the intervention.
They should not be stripped away when interpreting the study's safety findings.
No single checklist can determine suitability for every patient.
Particular attention is warranted when there is:
significant cardiovascular disease or poorly controlled blood pressure;
history of psychosis or mania;
active or high-risk substance misuse;
significant respiratory disease;
concurrent opioids, benzodiazepines, alcohol, or other sedatives;
pregnancy or plans for pregnancy;
liver disease;
urinary symptoms or prior ketamine-associated cystitis;
active suicidal crisis requiring a higher level of care.
These factors do not all function as absolute contraindications to every ketamine formulation.
They are reasons for individualized clinical assessment and, in some cases, choosing a more closely monitored setting.
The possible benefits should not be ignored.
A remote model can reduce:
travel burden;
geographic barriers;
time away from work;
clinic overhead;
repeated transportation requirements.
For patients who are carefully screened and who participate in a structured program, observational studies suggest meaningful improvement can occur.
The central uncertainty is not whether anyone benefits.
The uncertainty is how reliably those benefits and safety findings generalize beyond selected commercial-program populations, and how they compare with other evidence-based treatments over the long term.
Important unanswered questions remain.
We still need stronger evidence regarding:
randomized comparative effectiveness;
long-term benefit;
optimal maintenance strategies;
long-term cognitive effects;
cumulative urinary and hepatobiliary risk;
misuse and dependence over prolonged treatment;
which patients can safely receive treatment remotely;
which monitoring components are essential;
differences between compounded formulations and routes;
rare but serious adverse events.
The 2026 systematic review is therefore particularly important: large patient numbers do not automatically equal high-certainty evidence when the underlying studies are uncontrolled and at critical risk of bias. [2]
Urgent medical assessment is appropriate after ketamine exposure if a person develops:
difficulty breathing;
inability to stay awake or be awakened normally;
severe confusion or agitation;
seizure;
collapse or loss of consciousness;
severe chest pain;
dangerous blood-pressure symptoms;
severe or persistent vomiting with impaired consciousness;
suicidal behavior or rapidly worsening psychiatric symptoms.
Suspected overdose or dosing errors should be treated as medical toxicology problems—not managed by taking additional sedatives or attempting to “sleep it off.”
Ketamine and Spravato are not interchangeable regulatory concepts.
Racemic ketamine psychiatric treatment is off-label; esketamine has specific FDA-approved psychiatric indications and a REMS.
Telehealth evidence is encouraging but low-certainty.
Large observational datasets show improvement, but randomized comparative evidence remains limited.
Structured home treatment is not unsupervised use.
Screening, monitoring, peer support, follow-up, and emergency planning are part of the safety model.
Absence of onsite staff changes the risk environment.
A side effect that is manageable in a clinic may be more consequential at home.
Do not ignore cumulative toxicity.
Bladder, urinary tract, hepatobiliary, misuse, and dependence risks matter with repeated exposure.
Other sedatives can change the risk substantially.
Alcohol, opioids, benzodiazepines, and other CNS depressants can increase dangerous sedation and respiratory depression.
No. Racemic ketamine is not FDA-approved for any psychiatric disorder. At-home psychiatric use generally involves off-label prescribing and often compounded formulations.
Observational telehealth studies report substantial improvement in selected patients with depression and anxiety. However, a 2026 systematic review rated the evidence for effectiveness and safety as very low certainty because the available studies were at critical risk of bias.
No. Spravato is FDA-approved esketamine and must be administered in a REMS-certified healthcare setting. Compounded ketamine products are not FDA-approved.
No. Published structured telehealth programs have reported relatively low short-term adverse-event rates in selected patients. Those findings should not be generalized to unmonitored self-use or loosely supervised prescribing.
Yes. Chronic or repeated ketamine exposure has been associated with cystitis and other urinary tract complications. Severe cases are more strongly associated with prolonged exposure and misuse, but urinary symptoms during treatment deserve evaluation.
At-home ketamine therapy sits in an unusual evidence gap.
There is credible evidence that ketamine can produce rapid antidepressant effects, and large telehealth cohorts suggest that carefully selected patients can improve while receiving structured treatment at home.
But the evidence specifically supporting at-home psychiatric ketamine remains predominantly observational, provider-generated, and low-certainty.
At the same time, FDA has identified real concerns involving compounded ketamine, including sedation, dissociation, psychiatric effects, blood-pressure changes, respiratory depression, misuse, and urinary toxicity.
The appropriate conclusion is therefore not that at-home ketamine is universally dangerous—or universally safe.
Its risk-benefit profile depends heavily on who is treated, which formulation and route are used, how the patient is screened, what monitoring occurs, how adverse events are handled, and whether the medication remains within a structured clinical program.
Access is valuable.
But with ketamine, access should not come at the cost of clinical safeguards.
© All copyright of this material is absolute to Medical toxicology
Dr. Omid Mehrpour (MD, FACMT) is a senior medical toxicologist and physician-scientist with over 15 years of clinical and academic experience in emergency medicine and toxicology. He founded Medical Toxicology LLC in Arizona and created several AI-powered tools designed to advance poisoning diagnosis, clinical decision-making, and public health education. Dr. Mehrpour has authored over 250 peer-reviewed publications and is ranked among the top 2% of scientists worldwide. He serves as an associate editor for several leading toxicology journals and holds multiple U.S. patents for AI-based diagnostic systems in toxicology. His work brings together cutting-edge research, digital innovation, and global health advocacy to transform the future of medical toxicology.
Keep reading
 Public Health and Poison Prevention
Omid Mehrpour
 Public Health and Poison Prevention
Omid Mehrpour
 Public Health and Poison Prevention

Sherika Whitelocke
 Public Health and Poison Prevention
Omid Mehrpour