Clinical Toxicology
The Impact of Insulin Resistance on Poisoning Outcomes
Omid Mehrpour
Post on 28 Jan 2025 · Updated 16 Oct 2026 · 10 min read

Omid Mehrpour
Post on 28 Jan 2025 · Updated 16 Oct 2026 · 10 min read
 Medical Toxicologymedicaltoxic.com
https://medicaltoxic.com/blogs/the-impact-of-insulin-resistance-on-poisoning-outcomes
Insulin resistance means that tissues respond less effectively to insulin. It commonly accompanies obesity, metabolic syndrome, prediabetes, type 2 diabetes, and metabolic dysfunction-associated steatotic liver disease (MASLD), although none of these diagnoses directly measures insulin sensitivity. [1]
Because insulin influences glucose utilization, cardiovascular function, and cellular energy metabolism, pre-existing insulin resistance could plausibly modify the response to certain toxic exposures. But biological plausibility is not proof of a worse clinical outcome.
At present, human studies have not established pre-existing insulin resistance as an independent predictor of poisoning severity, mortality, or antidote requirements across acute poisonings. The most relevant clinical intersection is severe calcium channel blocker (CCB) poisoning: the exposure itself disrupts insulin secretion and myocardial energy metabolism, while high-dose insulin is a recommended treatment. [2] [3]
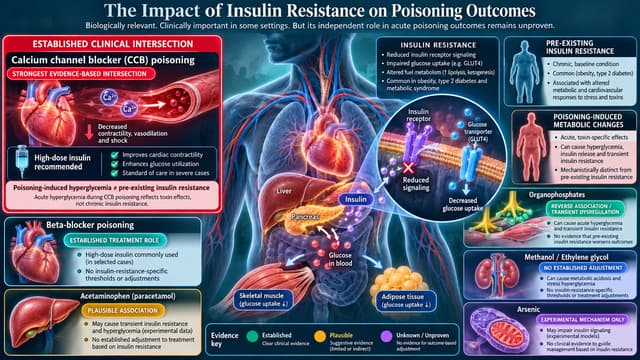
Evidence map · View original evidence-map illustration
Evidence map: separating established toxicologic mechanisms from associations and untested treatment assumptions.
A glucose concentration measured during an overdose cannot distinguish chronic insulin resistance from catecholamine-mediated stress, impaired pancreatic insulin release, dextrose administration, or critical illness. Hemoglobin A1c (HbA1c) can characterize prior glycemic control, but it is not a direct measurement of insulin sensitivity. Similarly, diabetes, obesity, and MASLD are clinically useful descriptors—not interchangeable laboratory diagnoses of insulin resistance. [1]
This distinction matters whenever investigators ask whether metabolic health before the exposure changed the outcome, or whether the exposure itself caused metabolic dysfunction. These are different causal questions and demand different study designs.
In severe CCB poisoning, blockade of pancreatic L-type calcium channels reduces insulin secretion, and impaired cardiac glucose utilization may accompany cardiovascular toxicity. Hyperglycemia can be a marker of serious poisoning, but it should not be interpreted automatically as evidence of pre-existing insulin resistance. [2] [3]
The 2025 American Heart Association (AHA) guidelines recommend high-dose insulin for hypotension in adults and children with life-threatening CCB poisoning (Class 1, Level of Evidence B-NR). Vasopressors are also recommended for hypotension. Treatment should be guided by perfusion and the evolving hemodynamic phenotype, rather than a single glucose result. [2]
For treatment details, see Calcium Channel Blocker Poisoning: High-Dose Insulin, Vasopressors, Calcium, and VA-ECMO.
There is no validated insulin-resistance-specific starting dose or fixed dose multiplier for high-dose insulin therapy. Higher doses may be required in severe poisonings, but the literature does not establish that chronic insulin resistance independently necessitates two or three times the usual regimen. Dose titration should follow hemodynamic response, myocardial function, glucose, potassium, and overall clinical course. [2] [4]
A frequently overlooked human experiment directly challenges an overly simple interpretation of insulin resistance. Von Lewinski and colleagues studied isolated atrial myocardium from 88 patients undergoing cardiac surgery, along with additional ventricular tissue. Insulin increased developed force to 117.8% ± 2.4% of baseline in tissue from patients with diabetes and 115.8% ± 1.9% in tissue from patients without diabetes; the investigators did not find a significant difference in the functional response between groups. [5]
This is important negative evidence against the assumption that diabetes necessarily blunts insulin's myocardial inotropic effect. It is not proof that insulin resistance is irrelevant during overdose: the experiments used isolated myocardium rather than poisoned patients in shock; diabetes is an imperfect proxy for insulin resistance; and the experimental conditions do not reproduce clinical high-dose insulin infusions.
A 2025 study by Cole and colleagues examined National Poison Data System (NPDS) reports from 2019–2021 in which high-dose insulin/glucose was documented as recommended or performed. Among 1,856 reports, 431 deaths (23%) were recorded. Older age, reported hyperglycemia, heart block, and use of mechanical ventilation or vasopressors were associated with death. [6]
These associations cannot establish whether hyperglycemia represented pre-existing insulin resistance, a direct effect of the toxicant, stress physiology, or treatment-related factors. The analysis is observational and includes patients selected for high-dose insulin consideration; 23% must not be interpreted as mortality caused by insulin treatment or as the outcome rate for all CCB and beta-blocker poisonings.
The study also reinforces the importance of shock physiology. Methylene blue, used by the investigators as a possible marker of refractory vasoplegia, was documented in 110 of 677 amlodipine exposures (16%) versus 7 of 325 verapamil/diltiazem exposures (2%). This is consistent with important vasodilatory shock in some amlodipine cases, but drug selection, poisoning severity, and practice differences limit causal interpretation. [6]
A patient with prominent myocardial depression and a patient with predominantly vasoplegic shock may not respond identically to the same intervention. That distinction is more immediately actionable than assuming an insulin dose adjustment from a diagnosis of diabetes. It does not justify routinely withholding recommended high-dose insulin in life-threatening CCB poisoning. [2] [6]
High-dose insulin also has an established role in life-threatening beta-blocker poisoning, but the AHA recommendation differs from that for CCB poisoning: insulin/euglycemia therapy is recommended for hypotension refractory to vasopressors (Class 1, Level of Evidence C-LD). [2]
Here, too, no validated rule requires more insulin solely because a patient has obesity, type 2 diabetes, or presumed chronic insulin resistance. Hemodynamic response should guide treatment, with careful surveillance for hypoglycemia, potassium shifts, and fluid burden. [2] [4]
Acetaminophen hepatotoxicity involves the reactive metabolite N-acetyl-p-benzoquinone imine (NAPQI), glutathione depletion, and downstream mitochondrial injury. MASLD and other metabolic conditions may alter susceptibility through CYP2E1 activity, mitochondrial function, and competing metabolic pathways. However, findings from experimental and clinical studies are inconsistent, and obesity, diabetes, MASLD, and measured insulin resistance should not be treated as equivalent risk factors. [7]
The 2023 US–Canada acetaminophen-poisoning consensus statement does not specify a separate acetylcysteine treatment threshold simply because a patient has insulin resistance. Decisions should continue to follow the ingestion pattern, acetaminophen concentration when applicable, hepatic tests, symptoms, and established treatment criteria. [8]
Neither a presumed reduction in the toxic dose nor an automatic intensification of N-acetylcysteine is justified by insulin resistance alone.
Some of the most relevant human evidence addresses the reverse hypothesis: acute organophosphorus (OP) insecticide poisoning may disturb subsequent glucose regulation.
In a prospective study from Sri Lanka and Bangladesh, Gifford and colleagues recruited 224 participants following pesticide self-poisoning (73 in Sri Lanka and 151 in Bangladesh). Around hospital discharge, OP-poisoned participants had higher fasting and two-hour glucose measurements than comparison groups exposed to other pesticides. The Sri Lankan component also found higher measures of insulin resistance and altered C-peptide responses. At follow-up 3–12 months later, the differences in glucose tolerance were no longer statistically significant in the 92 participants assessed. [9]
The study supports transient metabolic dysregulation following acute OP poisoning, not the claim that an individual who was insulin resistant before exposure will necessarily develop a more severe cholinergic crisis, acute respiratory distress syndrome, or multiorgan failure. Its relatively small follow-up cohort also cannot exclude longer-term effects.
Management remains based on the clinical cholinergic syndrome and established indications for atropine, oximes, airway support, and decontamination. See Organophosphate Poisoning: Recognition, Atropine, Oximes, and Emergency Management.
Laboratory research provides a mechanistic reason to investigate arsenic and metabolic health. Xue and colleagues found that inorganic arsenite exposure reduced insulin-stimulated AKT phosphorylation and glucose uptake in differentiated 3T3-L1 adipocytes. [10]
That result concerns toxicant exposure disrupting insulin signaling in an experimental system. It does not show that patients with pre-existing insulin resistance suffer more severe acute arsenic poisoning. Chronic environmental exposure, laboratory signaling experiments, and acute high-dose poisoning should not be conflated.
Methanol toxicity is driven principally by formate, while glycolate is a major contributor to the metabolic acidosis of ethylene glycol poisoning. There is no adequate clinical evidence that pre-existing insulin resistance independently slows elimination of either toxicant or makes bicarbonate therapy or dialysis less effective.
EXTRIP recommendations base extracorporeal-treatment decisions on toxicant-specific exposure measures, acid–base abnormalities, and severe clinical features—not a diagnosis of insulin resistance. [11] [12] A coexisting metabolic illness may still complicate care, but it should be evaluated on its own merits.
For toxicant-specific guidance, see Methanol Poisoning: Clinical Recognition, Triage, and Treatment.
The immediate implication is better clinical context, not automatic antidote escalation.
1. Document the relevant history. Note pre-existing diabetes (including type, when known), prior HbA1c, obesity, MASLD, kidney disease, cardiovascular disease, and glucose-lowering medications when available. Do not label all these conditions as proven insulin resistance.
2. Interpret glucose in context. Stress, toxicant effects, impaired insulin secretion, dextrose, liver dysfunction, and high-dose insulin therapy can all influence measured glucose.
3. Titrate high-dose insulin to physiology. In CCB and beta-blocker poisoning, follow current resuscitation guidance and the patient's response; do not apply an empiric insulin-resistance multiplier. Monitor glucose, potassium, perfusion, and fluid balance. [2]
4. Do not change antidote or dialysis thresholds without evidence. Insulin resistance alone is not an indication to alter acetylcysteine criteria, initiate extracorporeal treatment earlier for toxic alcohols, or increase atropine and oxime therapy in OP poisoning. [8] [11] [12]
5. Treat the poisoning, not the hypothesis. Starting metformin, antioxidants, anti-inflammatory agents, or other insulin-sensitizing therapies solely to reverse a presumed insulin-resistance effect during acute poisoning has no established clinical benefit.
Similarly, intravenous lipid emulsion and VA-ECMO should be considered according to specific toxicologic and hemodynamic indications—not the metabolic label alone. [2]
The central question is not whether insulin resistance has biologic effects; it does. It is whether measurable pre-exposure metabolic dysfunction independently predicts a different acute-poisoning outcome, after accounting for the identity and dose of the toxicant, initial severity, co-exposures, delayed presentation, and treatment selection.
A useful first study would link medical toxicology consultations for severe CCB poisoning to hospital records containing pre-event metabolic data. Analyses could separate diagnosed diabetes, historical HbA1c, obesity, and MASLD rather than combining them into an unvalidated “insulin resistance” variable. Outcomes might include time to sustained shock resolution, vasopressor-free days, and survival, with explicit accounting for cardiogenic versus vasoplegic shock and the influence of concurrent treatments.
Direct measures of insulin sensitivity are rarely available before an overdose, and measurements obtained during shock or high-dose insulin infusion are difficult to interpret. Prospective metabolic phenotyping after recovery could help, but it cannot retrospectively establish the patient's metabolic state immediately before the poisoning.
Insulin resistance is biologically relevant to cardiovascular and metabolic physiology, but its independent role in determining acute-poisoning outcomes remains unproven.
The most useful clinical intersection is severe CCB poisoning, where the toxicant itself can impair insulin secretion and energy metabolism and high-dose insulin is recommended treatment. Human myocardial experiments do not support assuming that diabetes necessarily diminishes insulin's inotropic effect. Large poison-center data identify prognostic associations but cannot separate pre-existing insulin resistance from poisoning-induced physiology. And prospective organophosphate research suggests that some toxic exposures can temporarily disrupt glucose regulation—the opposite direction of causation.
For clinicians, the actionable message is to document relevant comorbidities, interpret glucose carefully, monitor high-dose insulin safely, and continue treating each poisoning according to validated toxicology guidance rather than an untested insulin-resistance dosing formula.
© All copyright of this material is absolute to Medical toxicology
Dr. Omid Mehrpour (MD, FACMT) is a senior medical toxicologist and physician-scientist with over 15 years of clinical and academic experience in emergency medicine and toxicology. He founded Medical Toxicology LLC in Arizona and created several AI-powered tools designed to advance poisoning diagnosis, clinical decision-making, and public health education. Dr. Mehrpour has authored over 250 peer-reviewed publications and is ranked among the top 2% of scientists worldwide. He serves as an associate editor for several leading toxicology journals and holds multiple U.S. patents for AI-based diagnostic systems in toxicology. His work brings together cutting-edge research, digital innovation, and global health advocacy to transform the future of medical toxicology.
Keep reading
 Clinical Toxicology

Amirhosein Shabrang
 Clinical Toxicology
Amirhosein Shabrang
 Clinical Toxicology
Amirhosein Shabrang
 Clinical Toxicology
Amirhosein Shabrang